Related Experiment Video
Updated: Jul 14, 2026
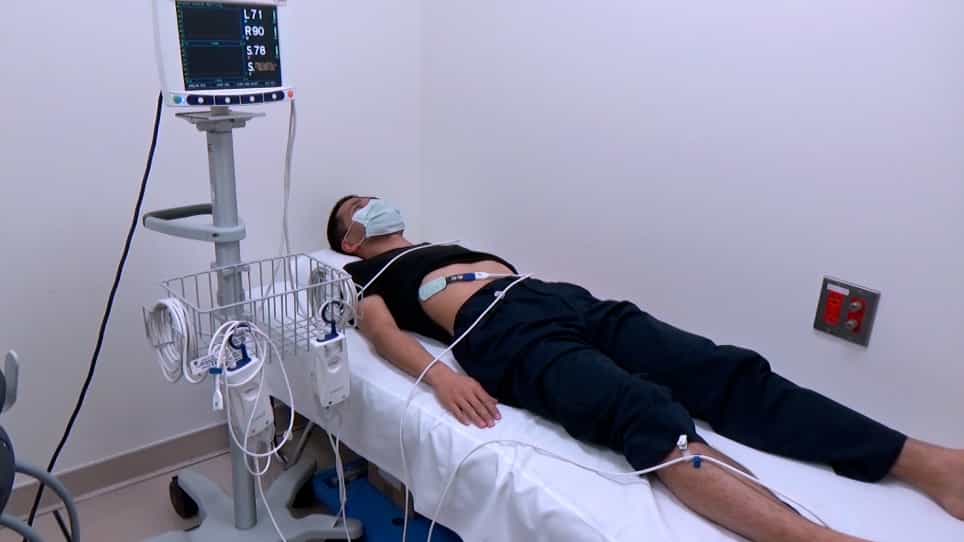

Measurement of Tissue Oxygenation Using Near-Infrared Spectroscopy in Patients Undergoing Hemodialysis
Published on: October 2, 2020
Changes in hemoglobin and albumin concentration during nocturnal home hemodialysis
John W M Agar1, Andreas Pierratos
1Department of Renal Medicine, Geelong Hospital, Barwon Health, Geelong, Victoria, Australia. johna@barwonhealth.org.au

The hemoglobin (Hb) and the serum albumin (S.Alb) concentration commonly rise during seated, conventional thrice-weekly 4 to 4.5 hr hemodialysis (CHD) as a result of rapid fluid removal from the intravascular compartment. Conversely, in long, slow, recumbent nocturnal home hemodialysis (NHHD), the intra-dialytic S.Alb concentration has been shown to fall. In normal human physiology, plasma volume expansion rapidly follows recumbency and is sustained until a resumption of an upright position re-induces plasma volume contraction. The plasma protein dilution of recumbency has been suggested as the mechanism behind this finding in NHHD. Our retrospective analysis of 585 consecutive measurements of predialysis and postdialysis S.Alb and Hb taken from 71 NHHD patients confirmed an intra-dialytic fall in S.Alb (0.99% in alternate night NHHD and 1.4% in 6 nights/week NHHD) compared with an 8.4% rise in a control group of 104 CHD patients (p<0.001). Although the NHHD intra-dialytic Hb rose (3.8% in alternate night NHHD and 2.6% in 6 nights/week NHHD), this rise was significantly greater (8%) in CHD patients (p<0.001), and as physiological data confirm that recumbent dilution for albumin is greater than that for Hb, this may provide the explanation. We conclude that NHHD provides a more physiological volume milieu with the normal physiological dilution mechanisms of recumbency still operating despite the slow, steady volume reduction that accompanied longer hour and more frequent dialysis. These mechanisms are subverted, however, in CHD by the more-aggressive plasma contraction needed to attain adequate control of the intravascular volume in the face of shorter hour, less-frequent dialysis.
The hemoglobin (Hb) and the serum albumin (S.Alb) concentration commonly rise during seated, conventional thrice-weekly 4 to 4.5 hr hemodialysis (CHD) as a result of rapid fluid removal from the intravascular compartment. Conversely, in long, slow, recumbent nocturnal home hemodialysis (NHHD), the intra-dialytic S.Alb concentration has been shown to fall. In normal human physiology, plasma volume expansion rapidly follows recumbency and is sustained until a resumption of an upright position re-induces plasma volume contraction. The plasma protein dilution of recumbency has been suggested as the mechanism behind this finding in NHHD. Our retrospective analysis of 585 consecutive measurements of predialysis and postdialysis S.Alb and Hb taken from 71 NHHD patients confirmed an intra-dialytic fall in S.Alb (0.99% in alternate night NHHD and 1.4% in 6 nights/week NHHD) compared with an 8.4% rise in a control group of 104 CHD patients (p<0.001). Although the NHHD intra-dialytic Hb rose (3.8% in alternate night NHHD and 2.6% in 6 nights/week NHHD), this rise was significantly greater (8%) in CHD patients (p<0.001), and as physiological data confirm that recumbent dilution for albumin is greater than that for Hb, this may provide the explanation. We conclude that NHHD provides a more physiological volume milieu with the normal physiological dilution mechanisms of recumbency still operating despite the slow, steady volume reduction that accompanied longer hour and more frequent dialysis. These mechanisms are subverted, however, in CHD by the more-aggressive plasma contraction needed to attain adequate control of the intravascular volume in the face of shorter hour, less-frequent dialysis.
Related Concept Videos
 01:24
Hemodialysis II: Procedure and Complications
 01:25
Hemodialysis III: Nursing Management
 01:25
Hemodialysis I: Introduction
 01:25
Peritoneal Dialysis III: Nursing Management
 01:25
Peritoneal Dialysis II: Peritoneal Dialysis Systems and Complications
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant