

Association of P-wave duration, dispersion, and terminal force in relation to P-wave axis among outpatients
Laxman Prajapat1, Vignendra Ariyarajah, Mary E Frisella
1Department of Medicine, Saint Vincent Hospital, Worcester, MA, USA.

Insights
P-wave duration (P-dur), P-wave dispersion (P-disp), and P-wave terminal force in lead V1 (PTFV1) show a significant tripartite association, especially within the normal P-wave axis range of 0 to +60 degrees. Evaluating these P-wave markers together offers optimal clinical assessment for cardiac impulse propagation.
Area of Science:
- Cardiology
- Electrocardiography
- Cardiac Electrophysiology
Background:
- P-wave duration (P-dur) and dispersion (P-disp) may reflect sinus cardiac impulse propagation abnormalities.
- The relationship between P-dur, P-disp, and P-wave terminal force in lead V1 (PTFV1) in relation to P-wave axis (P-axis) requires further study.
Purpose of the Study:
- To investigate the association between P-dur, P-disp, and PTFV1.
- To determine the significance of these P-wave characteristics in relation to the P-axis.
Main Methods:
- Analysis of 428 electrocardiograms (ECGs) from outpatients.
- Manual measurement of P-dur and P-disp to the nearest 10 ms.
- Assessment of PTFV1 positivity (> or = 40 mm2 terminal deflection) and P-axis (0 to +75 degrees).
Main Results:
- P-dur strongly associated with P-disp (P < 0.0001), though correlation was weak (r = 0.42).
- P-dur showed significance with P-axis within the normal range (0 to +60 degrees, P < 0.0001).
- PTFV1 (present in 47% of 380 ECGs) significantly associated with P-dur (P < 0.0001), P-disp (P < 0.0001), and P-axis (P = 0.002).
Conclusions:
- P-dur, P-disp, and PTFV1 exhibit a significant tripartite association.
- This association is particularly evident within the normal P-axis range (0 to +60 degrees).
- Clinical assessment benefits from evaluating these P-wave markers collectively in relation to the normal P-axis.
Background:
While P-wave duration (P-dur) and dispersion (P-disp) could both reflect fractionated and inhomogeneous propagation of sinus cardiac impulses, and may therefore be associated with each other, a clear relationship has not been extensively studied. We studied these markers as well as the significance of P-wave terminal force in lead V1 (PTFV1) in relation to the P-wave axis (P-axis).
Methods:
We appraised our previously studied sample of 500 consecutively numbered, otherwise unselected, electrocardiograms (ECGs) of outpatients from the University of Massachusetts, Worcester, Massachusetts, for the foregoing P-wave characteristics. P-disp, defined as the difference of the duration between the widest and narrowest P wave, and the greatest P-dur after a 12-lead ECG search, was measured manually to the nearest 10 ms. PTFV1 was considered positive when > or = 40 mm2 terminal deflection was present on biphasic P waves on lead V1. Normal P-axis was considered 0 degrees to +75 degrees by manually constructing the mean frontal plane electrical P-axis from standard limb leads.
Results:
After excluding those with atrial arrhythmias, paced rhythms, errors in lead placement, P waves with low amplitude or overall technically poor tracing, 428 ECGs formed our final sample. P-dur was strongly associated with P-disp (P < 0.0001), but the correlation remained weak (r = 0.42). Overall, P-dur was not significantly associated with P-axis but when divided into tertiles and quintiles, the significance was evident within the range of the normal P-axis, particularly 0 degrees to +60 degrees (P < 0.0001). In a subanalysis of 380 ECGs that had appreciable biphasic P waves on lead V1, PTFV1 was noted on 178 (47%) ECGs and was significantly associated with P-dur (P < 0.0001), P-disp (P < 0.0001), and P-axis (P = 002). When considering P-axis in tertiles and quintiles, P-dur was greater in patients with a positive PTFV1 and significant within the normal range of the P-axis, especially from 0 degrees to +60 degrees .
Conclusion:
P-dur, P-disp, and PTFV1 appear to share a significant tripartite association in relation to the normal P-axis, particularly when P-axis ranges 0 degrees to +60 degrees . Therefore, for optimal clinical assessment, these markers should be evaluated in relation to the normal P-axis.

Related Concept Videos
 01:29
Dysrhythmias III: Characteristics of Dysrhythmias
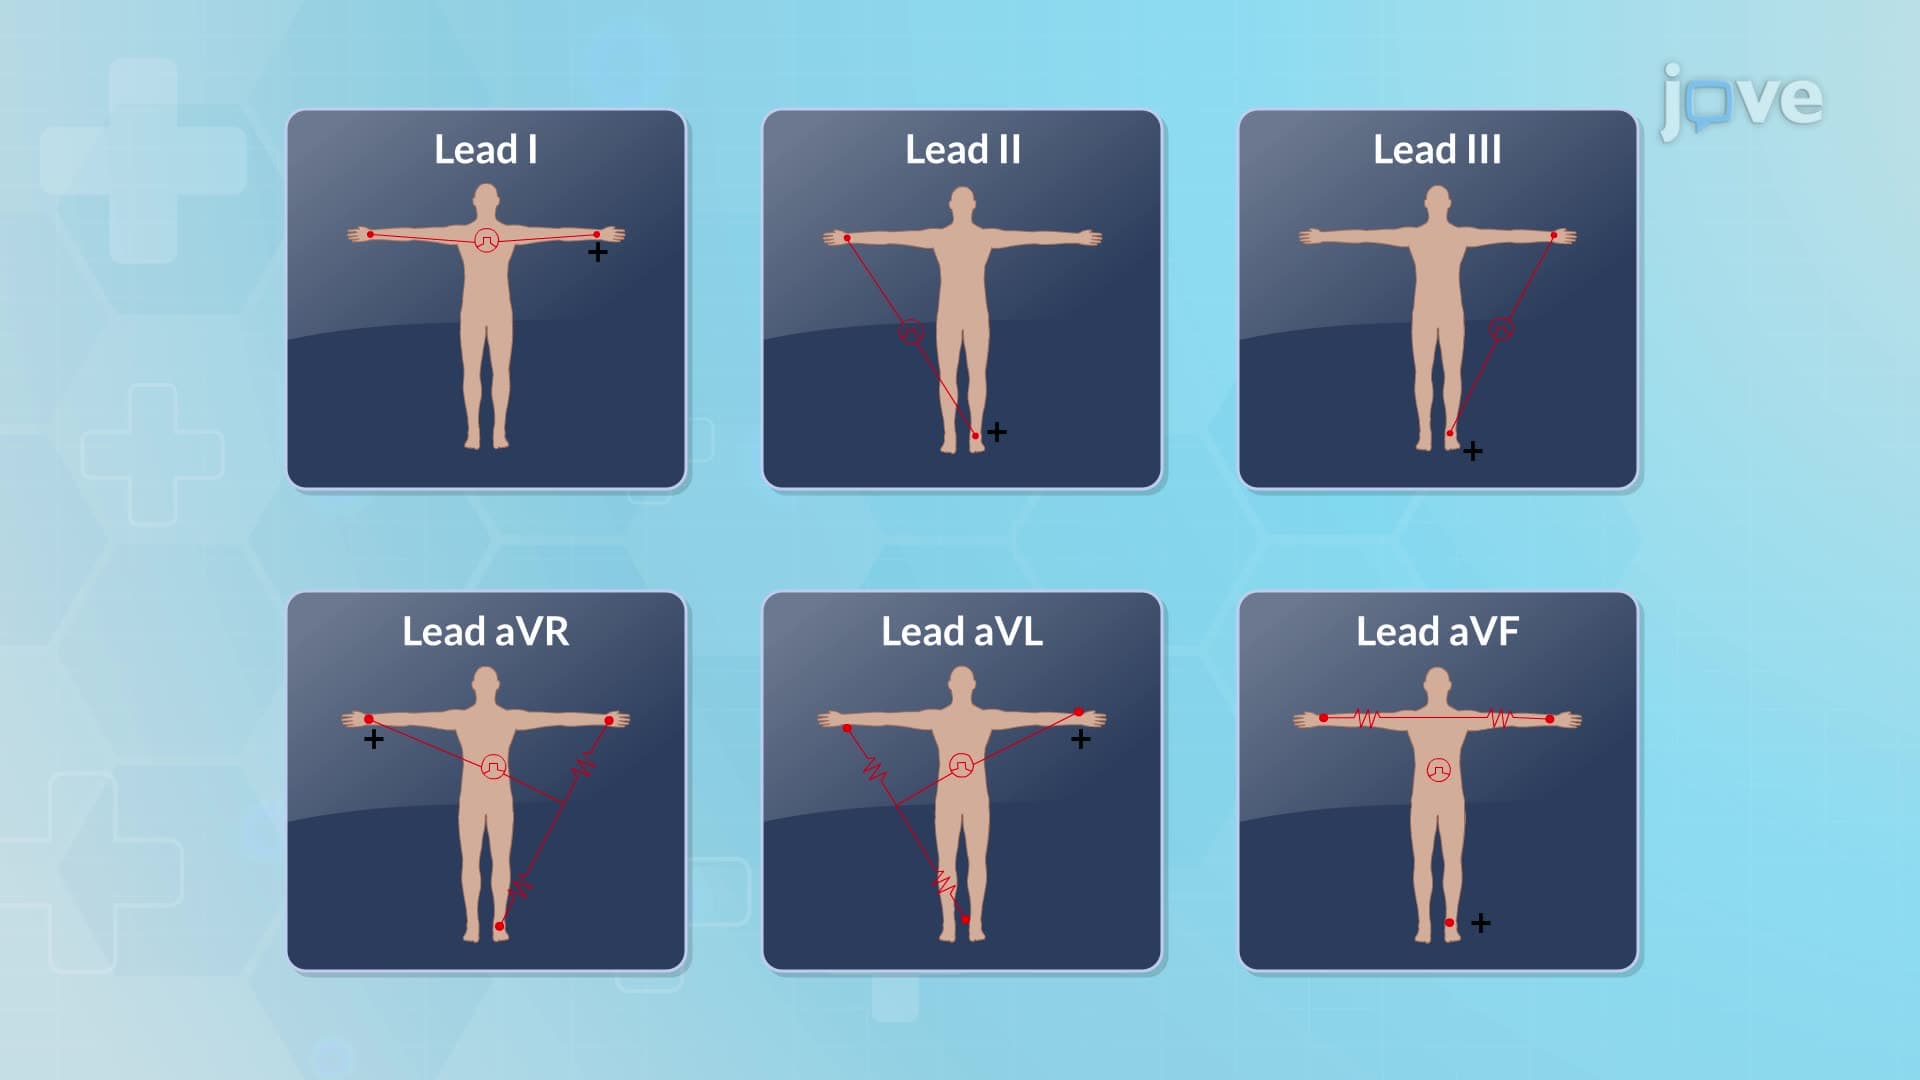 01:28
Electrocardiogram Fundamentals
An electrocardiogram (ECG) is a diagnostic tool for identifying cardiac conditions such as arrhythmias, conduction abnormalities, and myocardial ischemia.
Definition
An electrocardiogram (ECG) visualizes the heart's electrical activity by tracing the electrical movement associated with each heartbeat on a graph or monitor. As the heart beats, an electrical wave passes through it, correlating with the cardiac cycle events.
Parts of an ECG
An ECG utilizes electrodes on the skin to...
 01:25
Correlation between ECG and Cardiac Cycle
A cardiac action potential originates in the SA node and spreads throughout the atria and the AV node in approximately 0.03 seconds. This results in the P wave in an ECG and triggers atrial contraction. The action potential is then briefly slowed at the AV node, allowing the atria to contract and fill the ventricles with blood before...
 01:16
Pulse
The pulse serves as a clinical indicator...
 01:29
Electrocardiogram
Three major waveforms are present in a typical ECG recording: the P wave, the QRS complex, and the T...
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias