Laparoscopic and robotic complex upper-tract reconstruction in children with a duplex collecting system
Related Experiment Video
Updated: Aug 8, 2026
Robot-Assisted Kidney Transplantation
Published on: July 19, 2021
Alexander Kutikov1, Michael Nguyen, Thomas Guzzo
1Children's Hospital of Philadelphia, University of Pennsylvania, Philadelphia, Pennsylvania 19107, USA.

Insights
Laparoscopic surgery is a viable option for correcting complex duplex collecting system issues in children, offering a parenchyma-preserving approach. This minimally invasive technique effectively resolves symptoms and reconstructs the renal system.
Area of Science:
- Pediatric Urology
- Minimally Invasive Surgery
- Congenital Abnormalities
Background:
- Duplicated collecting systems are congenital anomalies that can lead to urinary tract infections, incontinence, and pain.
- Surgical correction is often considered for symptomatic or complex cases.
- Parenchyma-preserving approaches are desirable in pediatric reconstructive surgery.
Purpose of the Study:
- To evaluate the feasibility and outcomes of laparoscopic reconstruction for duplex collecting systems in children.
- To assess the effectiveness of a parenchyma-preserving laparoscopic approach for complex renal moiety reconstruction.
Main Methods:
- Six pediatric patients (4 months to 10 years) with duplex collecting system pathology underwent transperitoneal laparoscopic reconstruction.
- Procedures included ureteroureterostomies and a complex flap reconstruction.
- Both conventional laparoscopy and the da Vinci Surgical System were utilized.
Main Results:
- All presenting symptoms, including urinary tract infections and incontinence, resolved postoperatively.
- Mean operative time was 3.1 hours.
- Anatomic integrity was confirmed postoperatively via imaging.
Conclusions:
- Laparoscopic reconstruction of duplex collecting systems in children is feasible, even for complex cases requiring parenchyma preservation.
- This approach should be considered and compared with traditional open surgical techniques.
Purpose:
We suggest that when surgical correction is considered to treat a duplicated collecting system with well-functioning moieties, a laparoscopic approach at the renal level is feasible even in cases requiring complex reconstruction.
Patients And Methods:
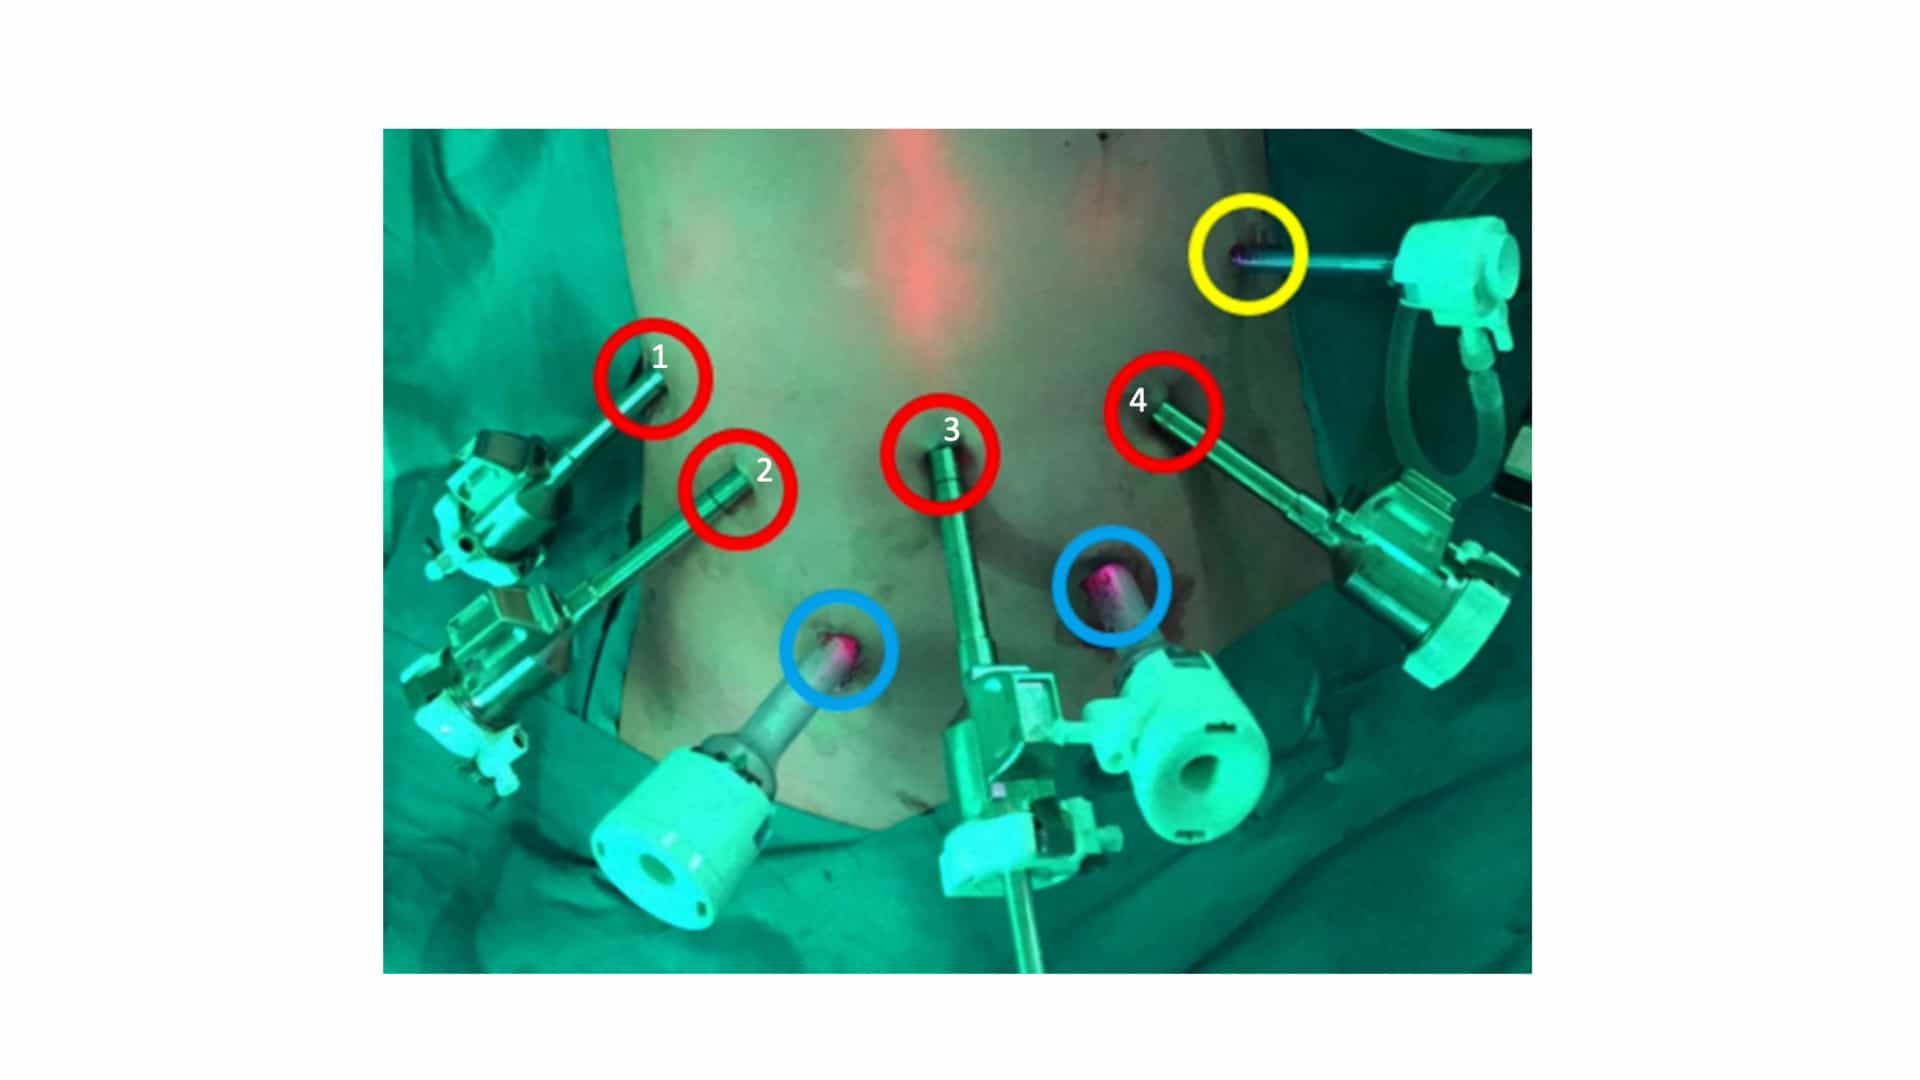
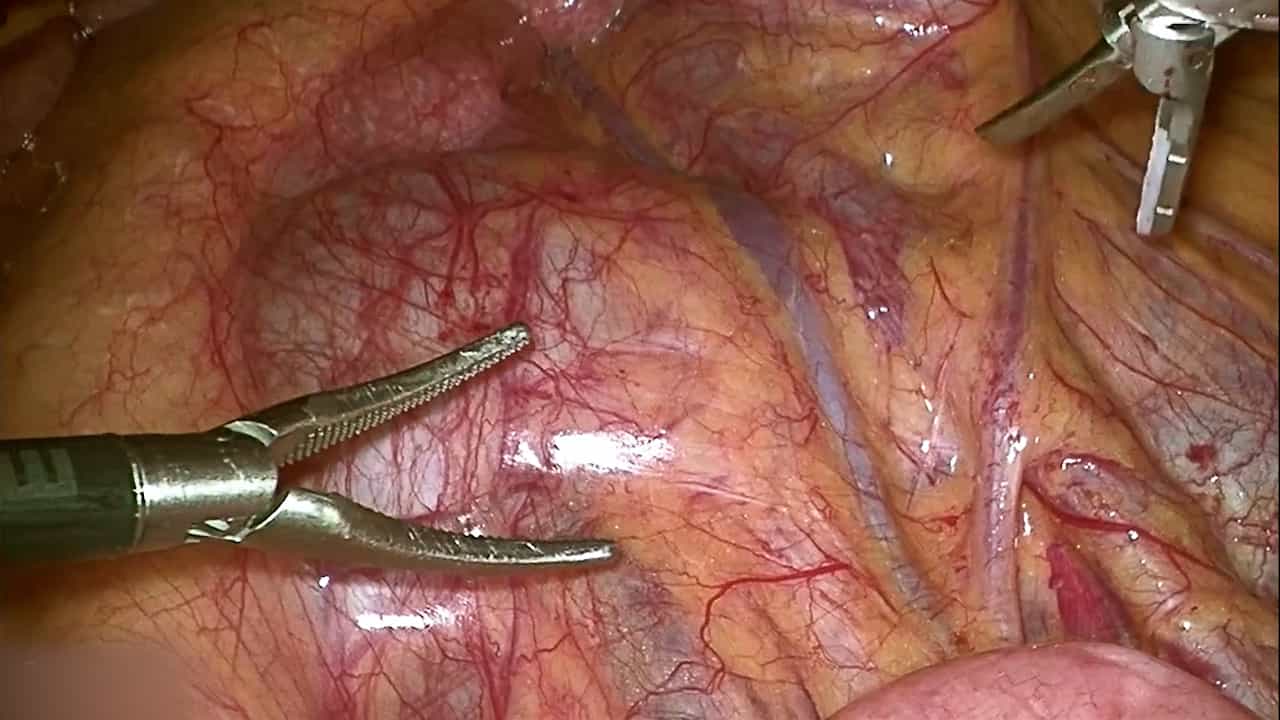
Six children between the ages of 4 months and 10 years (mean age 5.2 years) presented with urinary-tract infection, incontinence, or pain and underwent transperitoneal laparoscopic reconstruction for duplex collecting system pathology in renal moieties with preserved function. Five patients underwent laparoscopic upper pole-to-lower pole ureteroureterostomies, whereas one patient underwent a complex reconstruction of a long narrowing defect utilizing a Scardino-Prince vertical flap. Four patients underwent conventional laparoscopy, while the da Vinci Surgical System was used during the surgical procedures of the other two patients.
Results:
The mean operative time was 3.1 hours (range 2.6-4.9 hours) for the entire procedure, including cystoscopic evaluation. Stents were removed 6 weeks postoperatively. The patients were evaluated with retroperitoneal ultrasonography and either intravenous urography or diuretic radionuclide imaging to assess the anatomic integrity of the reconstruction. The presenting symptomatology resolved in all patients.
Conclusions:
We believe that complex laparoscopic upper-tract reconstruction in children who benefit from a parenchyma-preserving approach is possible and should be evaluated against open techniques.