Related Experiment Video
Updated: Jul 13, 2026


Modeling Encephalopathy of Prematurity Using Prenatal Hypoxia-ischemia with Intra-amniotic Lipopolysaccharide in Rats
Published on: November 20, 2015
Functional impairment of the brainstem in infants with bronchopulmonary dysplasia
Andrew R Wilkinson1, Dorothea M Brosi, Ze D Jiang
1Neonatal Unit, Department of Paediatrics, John Radcliffe Hospital, Headington, Oxford OX3 9DU, United Kingdom.

Insights
Infants with bronchopulmonary dysplasia show impaired brainstem function, indicated by delayed brainstem auditory evoked responses. This suggests poor myelination and synaptic function in the developing brain.
Area of Science:
- Neuroscience
- Neonatal Medicine
- Developmental Pediatrics
Background:
- Bronchopulmonary dysplasia (BPD) is a chronic lung disease affecting preterm infants.
- The impact of BPD on immature brain development, particularly brainstem function, requires further investigation.
Purpose of the Study:
- To assess the functional integrity of the brainstem in infants diagnosed with bronchopulmonary dysplasia.
- To identify specific abnormalities in brainstem auditory evoked responses (BAER) associated with BPD.
Main Methods:
- Studied 41 very preterm infants with BPD at 37-42 weeks postconceptional age.
- Utilized maximal length sequence technique to record and analyze brainstem auditory evoked responses.
- Compared findings with term and healthy very preterm control groups.
Main Results:
- Infants with BPD exhibited significantly increased wave V latency and I-V, III-V interpeak intervals in BAER compared to controls.
- Abnormalities worsened with increasing click rates, indicating impaired neural processing.
- Steeper latency-rate functions for wave V, I-V, and III-V intervals suggest delayed myelination and synaptic function.
Conclusions:
- Bronchopulmonary dysplasia is associated with impaired functional integrity of the brainstem.
- Findings suggest poor myelination and synaptic function in the brainstem of infants with BPD.
- Peripheral neural function appears relatively preserved in these infants.
Objectives:
To gain new insights into the influence of bronchopulmonary dysplasia on the immature brain and to detect abnormalities, we studied the functional integrity of the brainstem in infants with bronchopulmonary dysplasia.
Methods:
Forty-one very preterm infants with bronchopulmonary dysplasia were studied at postconceptional ages of 37 to 42 weeks. Brainstem auditory evoked responses were recorded and analyzed by using the maximal length sequence technique.
Results:
Compared with term control subjects, wave V latency in the maximal length sequence brainstem auditory evoked response of the infants with bronchopulmonary dysplasia increased significantly at all 91 to 910 clicks per second rates. Similarly, I-V and particularly III-V interpeak intervals increased significantly. The III-V/I-III interval ratio also increased significantly at all click rates. All of these abnormalities became more significant as the click rate was increased. Compared with healthy, very preterm control subjects, all of these maximal length sequence brainstem auditory evoked response variables increased significantly at all click rates, although the differences between the 2 groups were slightly smaller than those between the infants with bronchopulmonary dysplasia and the term control subjects. The wave I and III latencies and I-III interval in the infants with bronchopulmonary dysplasia did not show any abnormalities. The slopes of the wave V latency-rate function and I-V and particularly III-V interval-rate functions for the infants with bronchopulmonary dysplasia were significantly steeper than those for both term and healthy, very preterm control subjects. The slope of the III-V/I-III interval ratio-rate function for the infants with bronchopulmonary dysplasia was also significantly steeper than those for the 2 control groups.
Conclusions:
The results suggest poor myelination and synaptic function of the brainstem in infants with bronchopulmonary dysplasia, resulting in impaired functional integrity. In comparison, peripheral neural function was relatively intact.

Related Concept Videos
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:23
Acute Respiratory Failure-IV
 01:17
Pulmonary Cycle: Exhalation
 01:05
Breathing
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:19
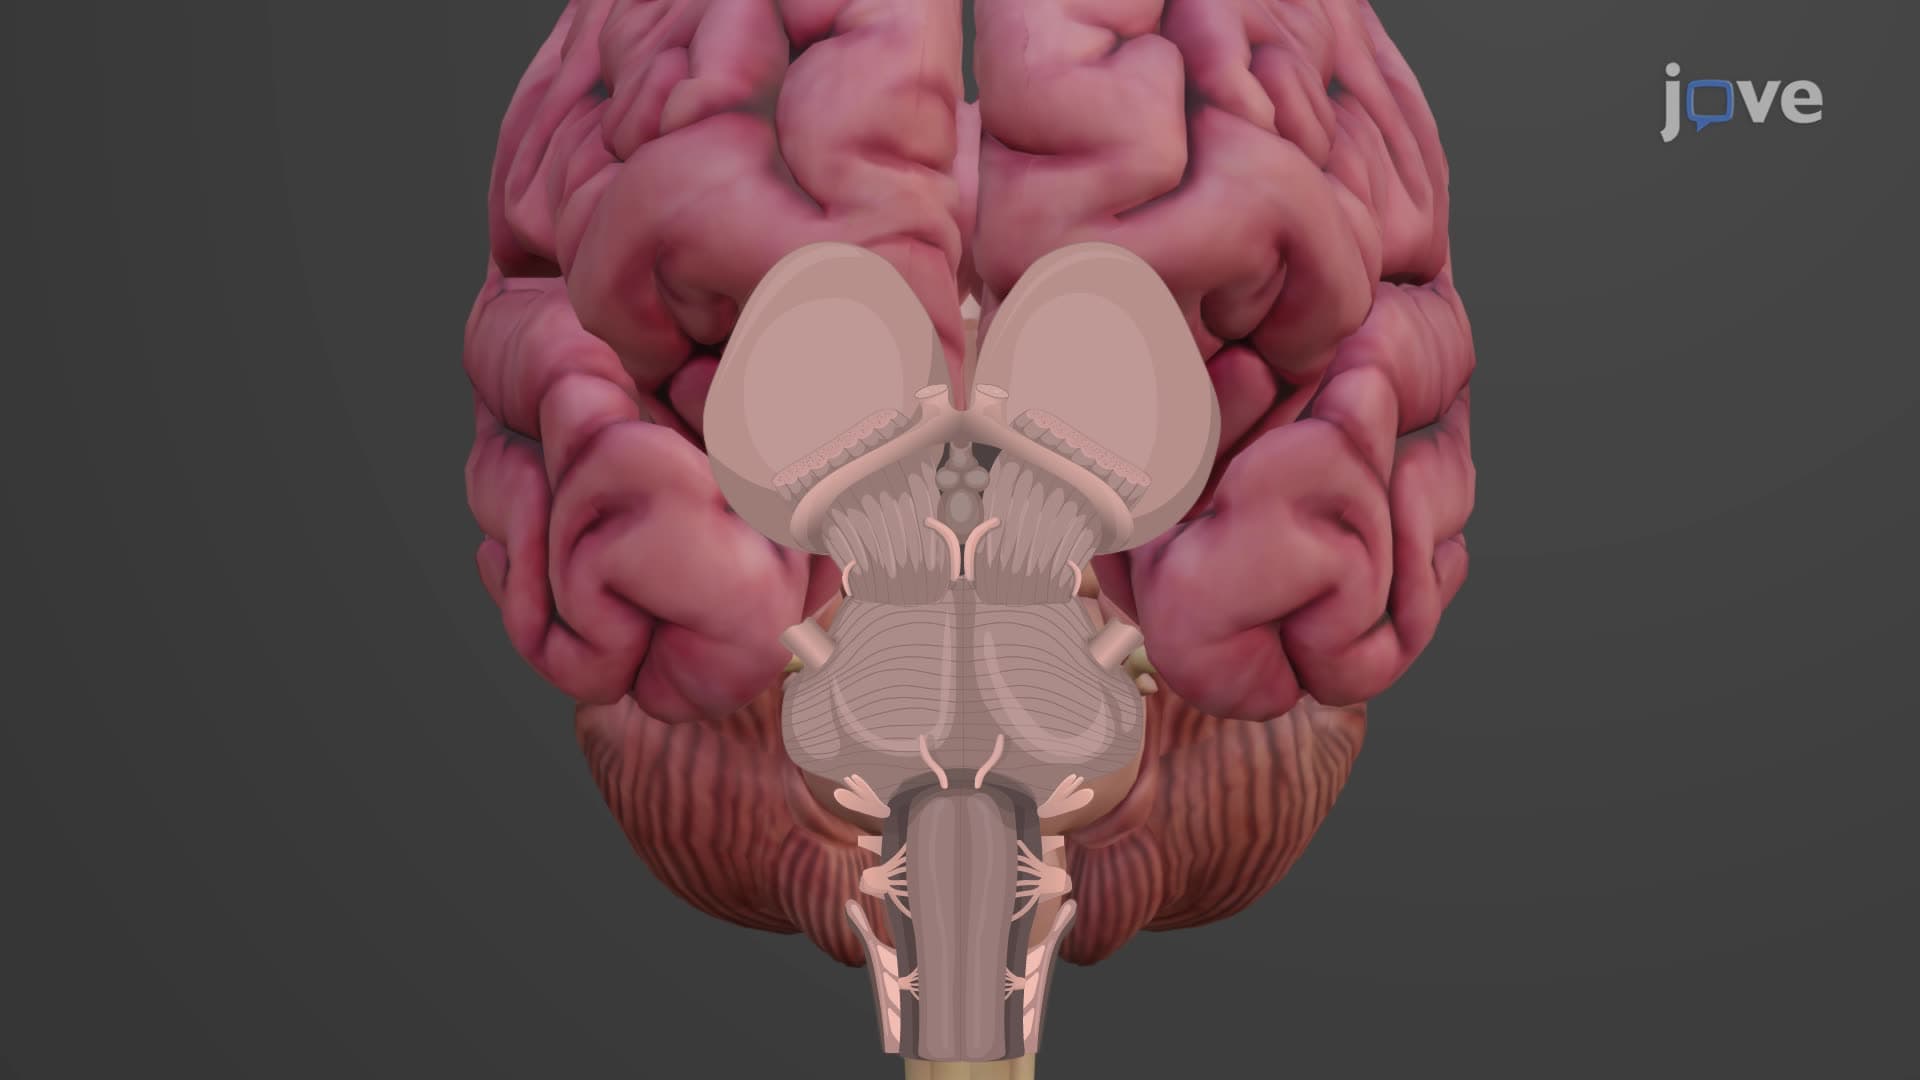
Brainstem
The Midbrain
The midbrain is located beneath the diencephalon and connects the cerebrum with the lower parts of the brain. The cerebral peduncles are prominent midbrain structures that house the...