Related Experiment Video
Updated: Jul 13, 2026

Targeted Knockdown of Genes in the Choroid Plexus
Published on: June 16, 2023
Targeted deletion of A2A adenosine receptors attenuates the protective effects of myocardial postconditioning
R Ray Morrison1, Xing Lin Tan, Catherine Ledent
1Div. of Critical Care Medicine, St. Jude Children's Research Hospital, 332 N. Lauderdale St., MS 734, Memphis, TN 38105, USA. ray.morrison@stjude.org

Abstract:
Endogenous adenosine is an important ligand trigger for the cardioprotective effects of postconditioning (POC), yet it is unclear which adenosine receptor subtype is primarily responsible. To evaluate the role of A(2A) adenosine receptors in POC-induced protection, global ischemia-reperfusion was performed with and without POC in isolated wild-type (WT) and A(2A) adenosine receptor knockout (A(2A)KO) mouse hearts. Injury was measured in terms of postischemic functional recovery and release of cardiac troponin I (cTnI). Activation of protective signaling with POC was assessed by Akt and extracellular signal-regulated kinase (ERK) 1/2 phosphorylation. In WT hearts, POC improved recovery of postischemic developed pressure in early (81.6 +/- 6.4% of preischemic baseline vs. 37.5 +/- 5.6% for non-POC WT at 1 min) and late (62.2 +/- 4.2% of baseline vs. 45.5 +/- 5.3% for non-POC WT at 30 min) reperfusion, reduced cTnI release by 37%, and doubled the phosphorylation of both Akt and ERK1/2. These beneficial effects of POC were blocked by treatment with the selective A(2A) adenosine receptor antagonist ZM-241385 during reperfusion. Postischemic functional recovery, cTnI release, and phosphorylation of Akt and ERK1/2 were not different between non-POC WT and A(2A)KO hearts. In A(2A)KO hearts, POC did not improve functional recovery, reduce cTnI release, nor increase phosphorylation of Akt or ERK1/2. Thus the protective effects of POC are attenuated by both selective A(2A) receptor antagonism and targeted deletion of the gene encoding A(2A) adenosine receptors. These observations support the conclusion that endogenous activation of A(2A) adenosine receptors is an essential trigger leading to the protective effects of POC in isolated murine hearts.
Insights
Endogenous adenosine A(2A) receptors are essential for the cardioprotective effects of postconditioning (POC). Blocking these receptors or deleting the A(2A) receptor gene prevents POC-induced heart protection.
Area of Science:
- Cardiovascular Physiology
- Molecular Cardiology
- Pharmacology
Background:
- Endogenous adenosine mediates cardioprotection via postconditioning (POC).
- The specific adenosine receptor subtype responsible for POC-induced protection remains unclear.
- A(2A) adenosine receptors are implicated in various protective signaling pathways.
Purpose of the Study:
- To investigate the critical role of A(2A) adenosine receptors in mediating the cardioprotective effects of POC.
- To determine if A(2A) receptor antagonism or genetic deletion abrogates POC-induced myocardial protection.
Main Methods:
- Global ischemia-reperfusion in isolated wild-type (WT) and A(2A) adenosine receptor knockout (A(2A)KO) mouse hearts.
- Assessment of postischemic functional recovery and cardiac troponin I (cTnI) release.
- Evaluation of Akt and extracellular signal-regulated kinase (ERK) 1/2 phosphorylation as markers of protective signaling.
Main Results:
- POC significantly improved functional recovery and reduced cTnI release in WT hearts.
- These protective effects were abolished by A(2A) receptor antagonist ZM-241385 and in A(2A)KO hearts.
- POC failed to enhance Akt and ERK1/2 phosphorylation in A(2A)KO hearts or with A(2A) receptor blockade.
Conclusions:
- Endogenous activation of A(2A) adenosine receptors is a crucial trigger for the cardioprotective effects of POC.
- A(2A) adenosine receptors are essential for mediating postconditioning-induced myocardial protection in murine hearts.

Related Concept Videos
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:31
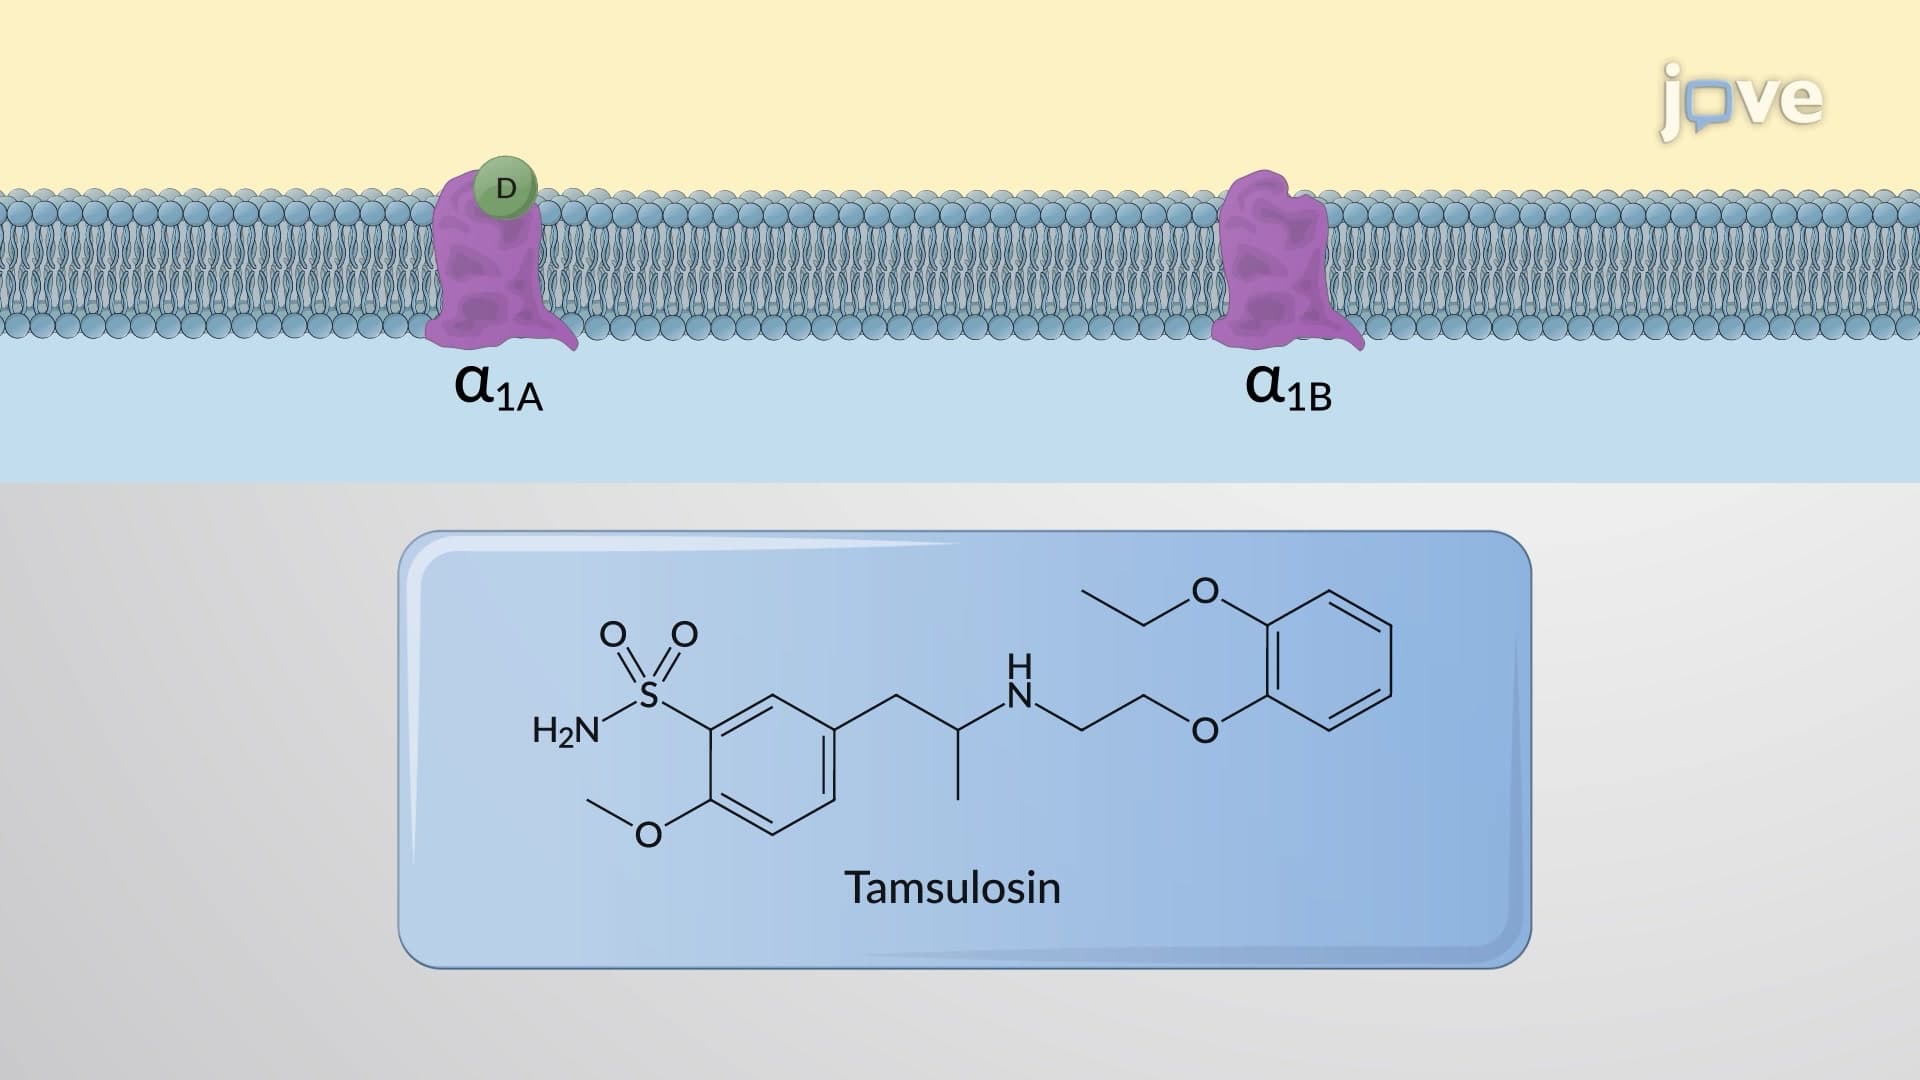
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...