Related Experiment Video
Updated: Jul 13, 2026
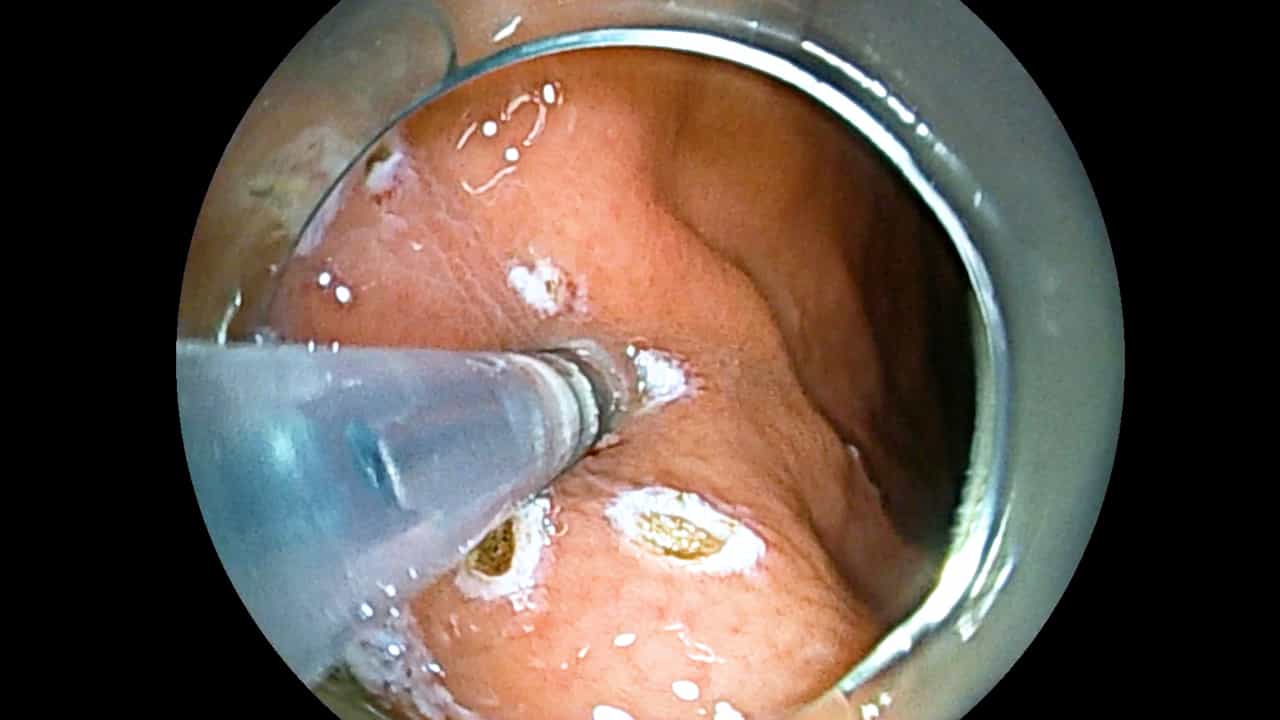

Evaluation of the Effectiveness of Longitudinal Incision for Endoscopic Submucosal Excavation of Gastric Subepithelial Lesions
Published on: April 28, 2026
Mortality in perforated peptic ulcer patients after selective management of stratified poor risk cases
M Mizanur Rahman1, M Saiful Islam, Sabrina Flora
1Department of Surgery, National Institute of Cancer and Research, Mohakhali, Dhaka, Bangladesh. mmrahmansurgeon@yahoo.com

Insights
Minimal surgical intervention, such as percutaneous peritoneal drainage, offers a promising treatment for perforated peptic ulcer disease in critically ill, poor-risk patients, significantly reducing mortality rates.
Area of Science:
- Surgical Gastroenterology
- Critical Care Medicine
- Gastrointestinal Surgery
Background:
- Perforated peptic ulcer disease (PPUD) is associated with high morbidity and mortality.
- Optimal management strategies for high-risk PPUD patients remain under investigation.
- Current stratification methods identify patients with increased surgical risk.
Purpose of the Study:
- To evaluate the effectiveness of minimal surgical intervention for high-risk patients with perforated peptic ulcer disease.
- To compare mortality rates between conventional surgery and minimal intervention in poor-risk PPUD patients.
Main Methods:
- Retrospective review of two patient series (Group A: 1980s, Group B: 1990s).
- Group A: Conventional operative management (n=522).
- Group B: Minimal surgical intervention (percutaneous peritoneal drainage) for selected poor-risk patients (n=84) alongside conventional management for others (n=626). Poor-risk criteria included age, delayed presentation, peritoneal contamination, and comorbidities.
Main Results:
- Conventional surgery in Group A had an 8.97% mortality rate.
- Conventional surgery in Group B had a 4.15% mortality rate.
- Minimal surgical intervention in selected poor-risk patients (n=84) resulted in a 3.5% mortality rate.
Conclusions:
- Percutaneous peritoneal drainage is a viable minimal surgical approach for high-risk PPUD patients.
- This approach significantly lowers mortality in critically ill, poor-risk individuals with perforated peptic ulcer disease.
Introduction:
Perforated peptic ulcer disease continues to inflict high morbidity and mortality. Although patients can be stratified according to their surgical risk, optimal management has yet to be described. In this study we demonstrate a treatment option that improves the mortality among critically ill, poor risk patients with perforated peptic ulcer disease.
Methods:
In our study, two series were retrospectively reviewed: group A patients (n = 522) were treated in a single surgical unit at the Dhaka Medical College Hospital, Dhaka, Bangladesh during the 1980s. Among them, 124 patients were stratified as poor risk based on age, delayed presentation, peritoneal contamination, and coexisting medical problems. These criteria were the basis for selecting a group of poor risk patients (n = 84) for minimal surgical intervention (percutaneous peritoneal drainage) out of a larger group of patients, group B (n = 785) treated at Khulna Medical College Hospital during the 1990s.
Results:
In group A, 479 patients underwent conventional operative management with an operative mortality of 8.97%. Among the 43 deaths, 24 patients were >60 years of age (55.8%), 12 patients had delayed presentation (27.9%), and 7 patients were in shock or had multiple coexisting medical problems (16.2%). In group B, 626 underwent conventional operative management, with 26 deaths at a mortality rate of 4.15%. Altogether, 84 patients were stratified as poor risk and were managed with minimal surgical intervention (percutaneous peritoneal drainage) followed by conservative treatment. Three of these patients died with an operative mortality of 3.5%.
Conclusions:
Minimal surgical intervention (percutaneous peritoneal drainage) can significantly lower the mortality rate among a selected group of critically ill, poor risk patients with perforated peptic ulcer disease.
Related Concept Videos
 01:27
Peptic Ulcer
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications
 01:16
Treating Helicobacter pylori in Peptic Ulcers: Antimicrobial Therapy