Related Experiment Video
Updated: Jul 11, 2026
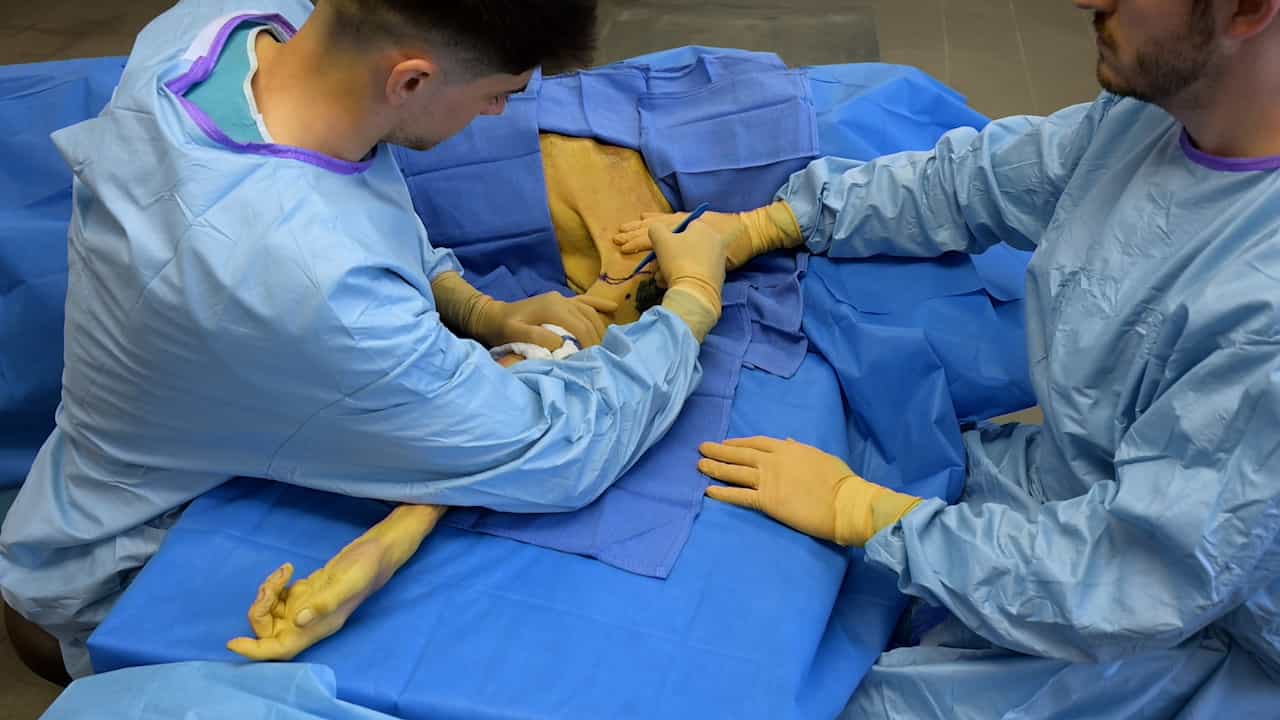
Vascularized Composite Upper Limb Allograft Harvesting for Proximal Arm Allotransplantation
Published on: June 13, 2025
Transfer of the accessory nerve to the suprascapular nerve in brachial plexus reconstruction
Jayme Augusto Bertelli1, Marcos Flávio Ghizoni
1Department of Orthopedic Surgery, Governador Celso Ramos Hospital, Florianópolis, SC, Brazil. bertelli@matrix.com.br

Purpose:
Transfer of the accessory nerve to the suprascapular nerve is a common procedure, performed to reestablish shoulder motion in patients with brachial plexus palsy. We propose dissecting both nerves via a distal oblique supraclavicular incision, which can be prolonged up to the scapular notch. The results of the transfer to the suprascapular nerve are compared with those of the combined repair of the suprascapular and axillary nerves.
Methods:
Thirty men between the ages of 18 and 37 years with brachial plexus trauma had reparative surgery within 3 to 10 months of their injuries. In partial injuries with a normal triceps, a triceps motor branch transfer to the axillary nerve was performed. The suprascapular and accessory nerves were dissected via an oblique incision, extending from the point at which the plexus crosses the clavicle to the anterior border of the trapezius muscle. In 10 patients with fractures or dislocations of the clavicle, the trapezius muscle was partially elevated to expose the suprascapular nerve at the suprascapular notch.
Results:
In all cases, transfer of the accessory to the suprascapular nerve was performed without the need for nerve grafts. A double lesion of the suprascapular nerve was identified in 1 patient with clavicular dislocation. In those with total palsy, the average improvement in range of abduction was 45 degrees , but none of the patients with total palsy recovered any active external rotation. Patients with upper-type injury recovered an average of 105 degrees of abduction and external rotation. If only patients with C5-C6 injuries were considered, the range of abduction and external rotation increased to 122 degrees and 118 degrees , respectively.
Conclusions:
Use of the accessory nerve for transfer to the suprascapular nerve ensured adequate return of shoulder function, especially when combined with a triceps motor branch transfer to the axillary nerve. The supraclavicular exposure proposed here for the suprascapular and accessory nerves is advantageous and can be extended easily to explore the suprascapular nerve at the scapular notch.

Related Concept Videos
 01:22
Spinal Nerves: Plexus I
The Cervical Plexus
The cervical plexus, formed by the anterior rami of the first four...
 01:31
Muscles that Move the Arm
The pectoralis major has two origins. Its clavicular head originates on the medial half of the clavicle. In contrast, the sternocostal head originates on the costal cartilages of ribs 1-6, the sternum, and the aponeurosis of the external oblique of the...
 01:12
Arteries of the Upper Limbs
 01:23
Muscles of the Shoulder
Anterior Thoracic Muscles
The anterior thoracic muscles include the serratus anterior, subclavius, and...
 01:21
Spinal Nerves: Plexus II
The Lumbar Plexus
The lumbar plexus is situated within the lumbar region of the back and is primarily formed by the first four lumbar spinal nerves (L1 to L4). This plexus extends its branches into several nerves, including the...
 01:10
The Arch of Aorta
Encircling the heart, the coronary arteries form a ring-like structure before...