Related Experiment Video
Updated: Jul 11, 2026
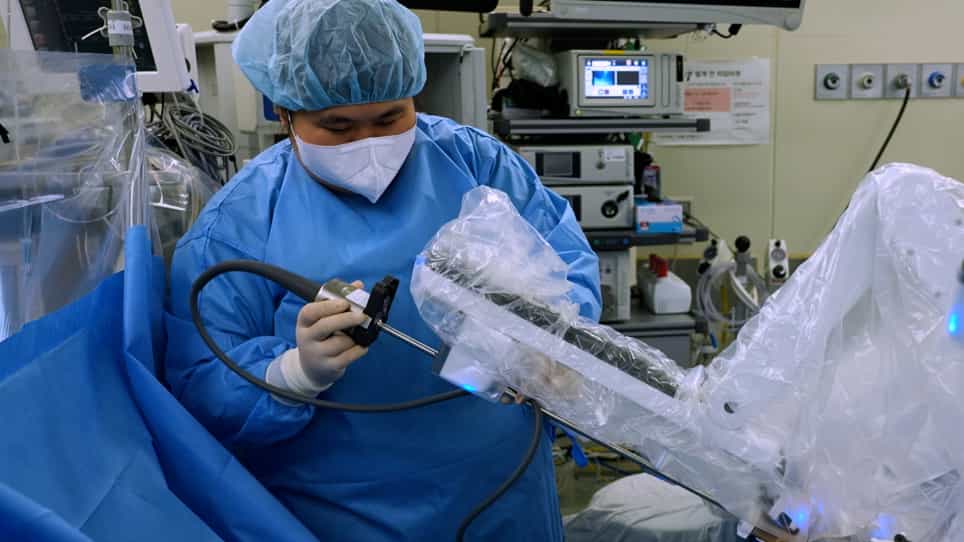
Robot-Assisted Kidney Transplantation
Published on: July 19, 2021
Epidemiology and outcomes of multiple antibiotic-resistant bacterial infection in renal transplantation
L Linares1, C Cervera, F Cofán
1Infectious Diseases Service, Hospital Clinic, IDIBAPS, University of Barcelona, Barcelona, Spain.

Background:
Mutiresistant bacterial infections are an emerging problem in the nosocomial setting. Our objectives were to describe the incidence, outcome, and risk factors for acquisition of multiresistant bacteria among renal transplant recipients.
Methods:
We prospectively followed patients undergoing kidney transplantation over a 3-year period. We collected demographic features, underlying chronic diseases, and main transplant characteristics and complications. Multiple antibiotic resistance was defined for the most important bacteria: Enteric gram-negative bacilli resistant to betalactamics, cephalosporins, and quinolones; Staphylococcus aureus resistant to methicillin, cotrimoxazole, and clindamcin; Enterococcus spp resistant to ampicillin and quinolones; nonfermentator bacilli resistant to all antibiotics except aminoglycosides and collistin.
Results:
Overall, 416 patients included 65 double transplants (62 kidney-pancreas and three kidney-liver) of mean age 48.5 years, and 57% men. Infection with multiresistant bacteria was observed in 58 patients (14%). Most frequent multiresistant bacteria were: Escherichia coli (n = 33), Klebsiella spp (n = 15), Citrobacter spp (n = 8), Enterobacter spp (n = 5), Morganella morganii (n = 2), Pseudomonas aeruginosa (n = 16), Acinetobacter baumanii (n = 2), Enterococcus spp (n = 9) and methicillin-resistant S. aureus (MRSA, n = 2). Age greater than 50 years, hepatitis C virus infection, double kidney-pancreas transplantation, requirement for posttransplant hemodialysis, surgical reoperation, and requirement for nephrostomy were independent variables associated with multiresistant bacterial infection. Most used antibiotics for treatment were: carbapenems (65%), amikacin (12%), linezolid, piperacillin-tazobactam, vancomycin, collistin, and fosfomycin. Infection with multiresistant bacteria was associated with a worse prognosis (graft loss or death, 19% vs 8%, P = .009).
Conclusions:
The incidence of infection with multiresistant bacteria in our renal transplant cohort was high, being most frequently cephalosporin-resistant enteric gram-negative bacilli and multiresistant P aeruginosa. Methicillin-resistant S. aureus incidence was low. Infection with multiresistant bacteria conferred a worse prognosis.
Related Concept Videos
 01:26
Kidney Transplant II: Surgical Procedure
 01:16
Kidney Transplant III: Nursing Management
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:28
Kidney Transplant I: Introduction
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:25
Urinary Tract Infection II: Pathophysiology