Related Experiment Video
Updated: Jul 11, 2026


A Large Animal Model for Acute Kidney Injury by Temporary Bilateral Renal Artery Occlusion
Published on: February 2, 2021
Conservative outpatient renoprotective protocol in patients with low GFR undergoing contrast angiography: a case
Paul Komenda1, Nadia Zalunardo2, Shelley Burnett2
1Department of Medicine, Division of Nephrology, St. Paul's Hospital, Division of Nephrology, University of British Columbia, 1081 Burrard Street, Providence Wing RM 6010A, Vancouver, BC, V6Z 1Y8, Canada. paulkomenda@gmail.com.

Insights
A conservative outpatient protocol effectively prevented contrast-induced nephropathy in high-risk chronic kidney disease patients undergoing cardiac angiography. This approach warrants further investigation in randomized trials to confirm safety and efficacy.
Area of Science:
- Nephrology
- Cardiology
- Radiology
Background:
- Radiocontrast-induced nephropathy (CIN) prevention strategies for high-risk patients undergoing cardiac angiography remain debated.
- Patients with chronic kidney disease (CKD) and low estimated glomerular filtration rates (eGFRs) face increased risk of kidney function decline or dialysis post-contrast.
- This risk can lead to withholding or delaying life-saving procedures like angiography.
Purpose of the Study:
- To evaluate a standardized outpatient protocol for preventing CIN in patients with CKD undergoing angiography.
- To assess the safety and efficacy of this protocol in a case series.
Main Methods:
- A case series of 31 CKD patients undergoing cardiac or peripheral angiography, or angioplasty/stenting for renal artery stenosis (RAS).
- Patients followed an outpatient protocol: withholding diuretics, ACE inhibitors (ACEs)/angiotensin receptor blockers (ARBs) pre- and post-procedure, with calcium channel blockers administered peri-procedurally.
- Bloodwork was conducted at 2-3 and 7-10 days post-procedure.
Main Results:
- Mean baseline creatinine was 214 micromol/l, with a mean eGFR of 34 ml/min (range 12-59 ml/min).
- All patients had baseline eGFR < 60 ml/min, with stages ranging from 3 to 5 CKD.
- No patient required urgent hemodialysis post-angiography, and no change in kidney function progression rate was observed during 26 months of follow-up.
Conclusions:
- The described conservative, outpatient protocol appears effective for high-risk CKD patients undergoing cardiac angiography.
- This protocol merits further investigation through randomized controlled trials to validate its findings.
Background:
The correct strategy to prevent radiocontrast-induced nephropathy (CIN) in high-risk patients going for cardiac angiography is widely debated in the literature. It is well known that chronic kidney disease (CKD) patients with lower estimated glomerular filtration rates (eGFRs) at baseline are at the greatest risk for a significant loss in kidney function, or even dialysis after a contrast load. For this reason potentially life-saving procedures such as angiography are sometimes withheld or delayed.
Methods:
We describe a case series of 31 well-characterized patients with CKD who underwent cardiac or peripheral vessel angiography, and patients with renal artery stenosis (RAS) who underwent angioplasty and stenting. All were treated with a standardized outpatient protocol of withholding their diuretics and angiotensin-converting enzyme (ACE) inhibitors (ACEs)/angiotensin receptor blockers (ARBs) the day prior to and 2 days after the procedure, restarting the diuretic the day after the procedure and the ACE inhibitor/ARB after 2 days. Calcium channel blockers were prescribed for the 2 days prior to and 2 days after the procedure. Patients had bloodwork on days 2-3 and days 7-10 post-procedure.
Results:
The patients had a mean baseline creatinine of 214 micromol/l (SD = 123), ranging from 87 to 535 micromol/l. This corresponded to a mean baseline eGFR of 34 ml/min (SD = 15.8), ranging from a minimum of 12-59 ml/min. The mean age was 64 +/- 13.8 years; 48% were male and 11 (35.5%) were diabetic. All patients enrolled had a baseline eGFR of less than 60 ml/min as calculated by the Modification of Diet in Renal Disease (MDRD) formula. Based on pre-procedure CKD stage, 21 (68%) were stage 3 (eGFR 30-60 ml/min), 5 (16%) were stage 4 (eGFR 15-30 ml/min), and 6 (19%) were stage 5 (eGFR < 15 ml/min). No patient required urgent hemodialysis following their angiography. All patients have had a longitudinal follow up of 26 months, and none developed any change in the rate of progression from prior to procedure.
Conclusions:
This case series provides data in support of a conservative, outpatient-based approach for high-risk CKD patients going for cardiac angiography. This protocol warrants further study in randomized control trials.

Related Concept Videos
 01:19
Imaging Studies VII: Vascular Imaging
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:06
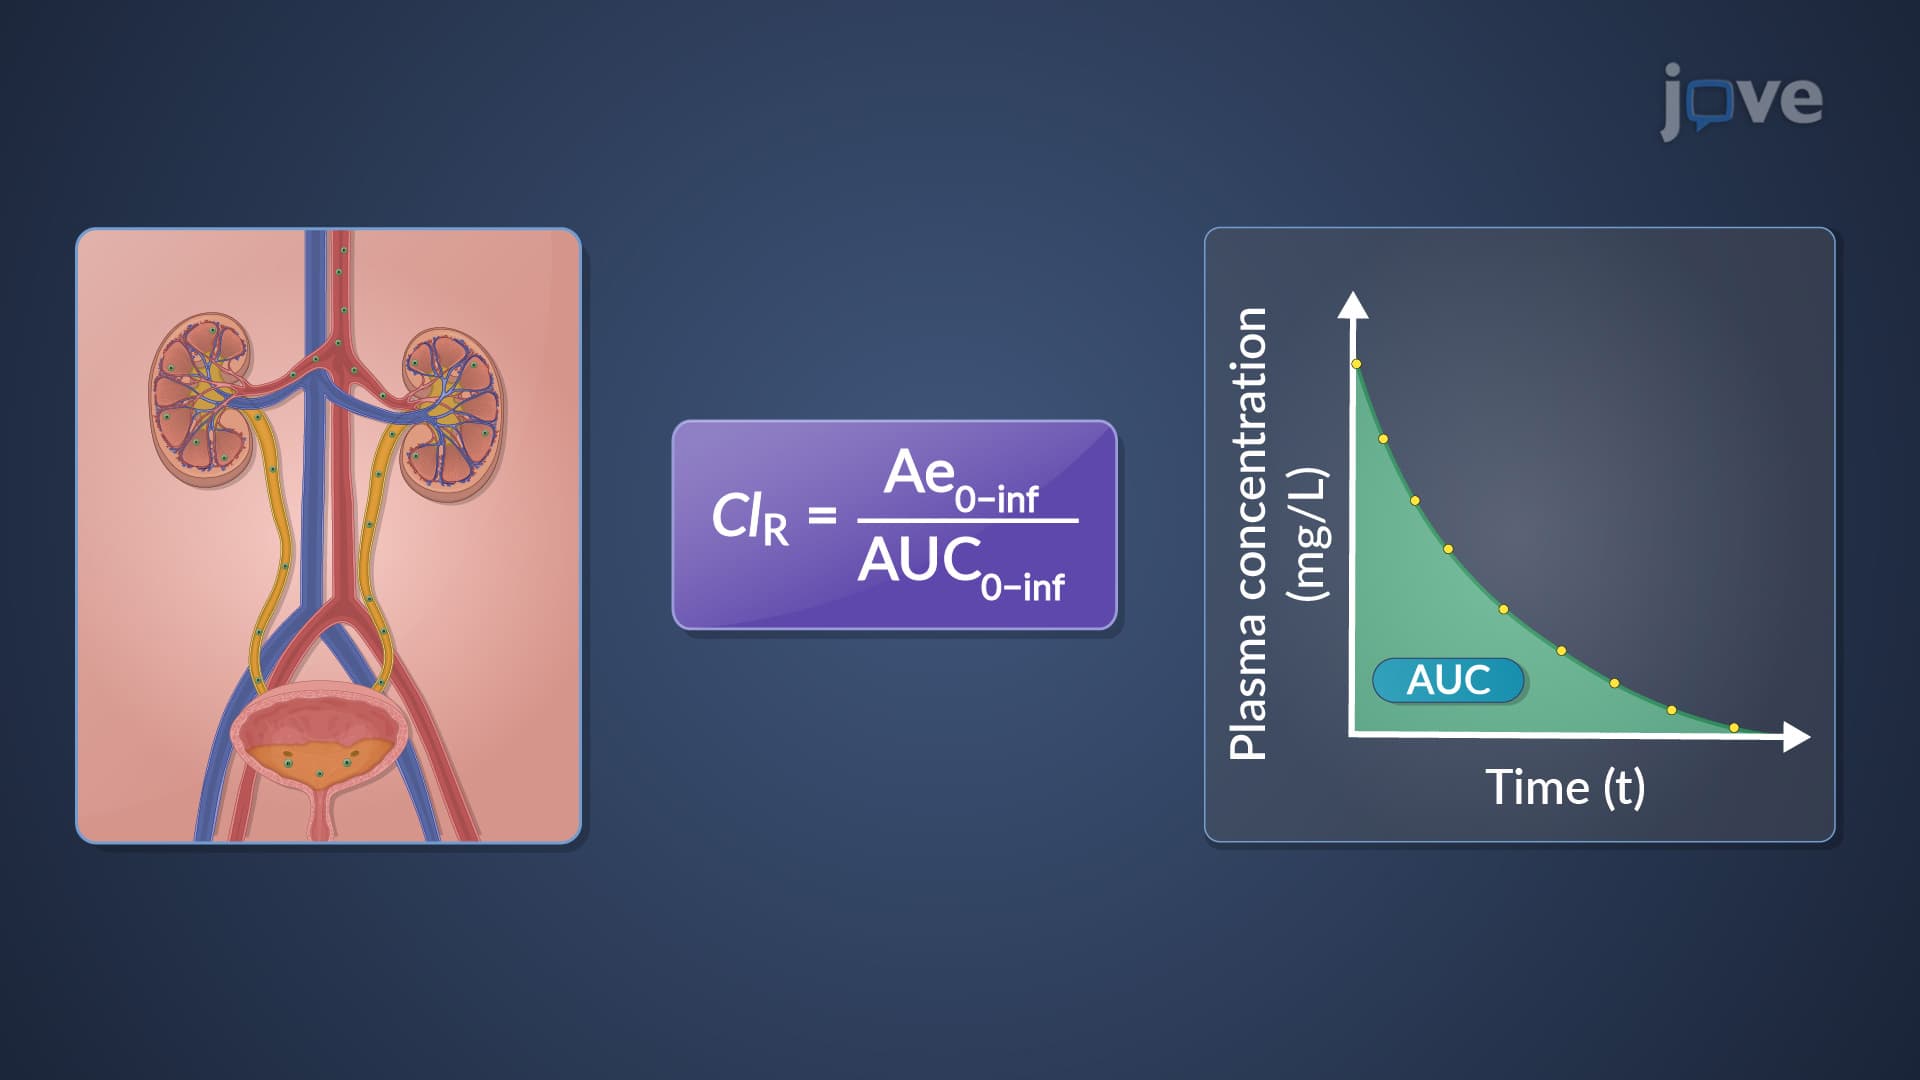
Renal Drug Clearance: Overview
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:28
Cardiac Catheterization I: Pre-Procedure Overview