Related Experiment Video
Updated: Jul 11, 2026

Robotic Duodenum-preserving Total Pancreatic Head Resection for Intraductal Papillary Mucinous Neoplasms
Published on: April 17, 2026
Intraductal papillary mucinous neoplasms: predictors of malignant and invasive pathology
C Max Schmidt1, Patrick B White, Joshua A Waters
1Department of Surgery, Indiana University School of Medicine, Indianapolis, IN 46202, USA. maxschmi@iupui.edu

Objective:
Determine whether size and other preoperative parameters predict malignant or invasive intraductal papillary mucinous neoplasia (IPMN).
Summary Background Data:
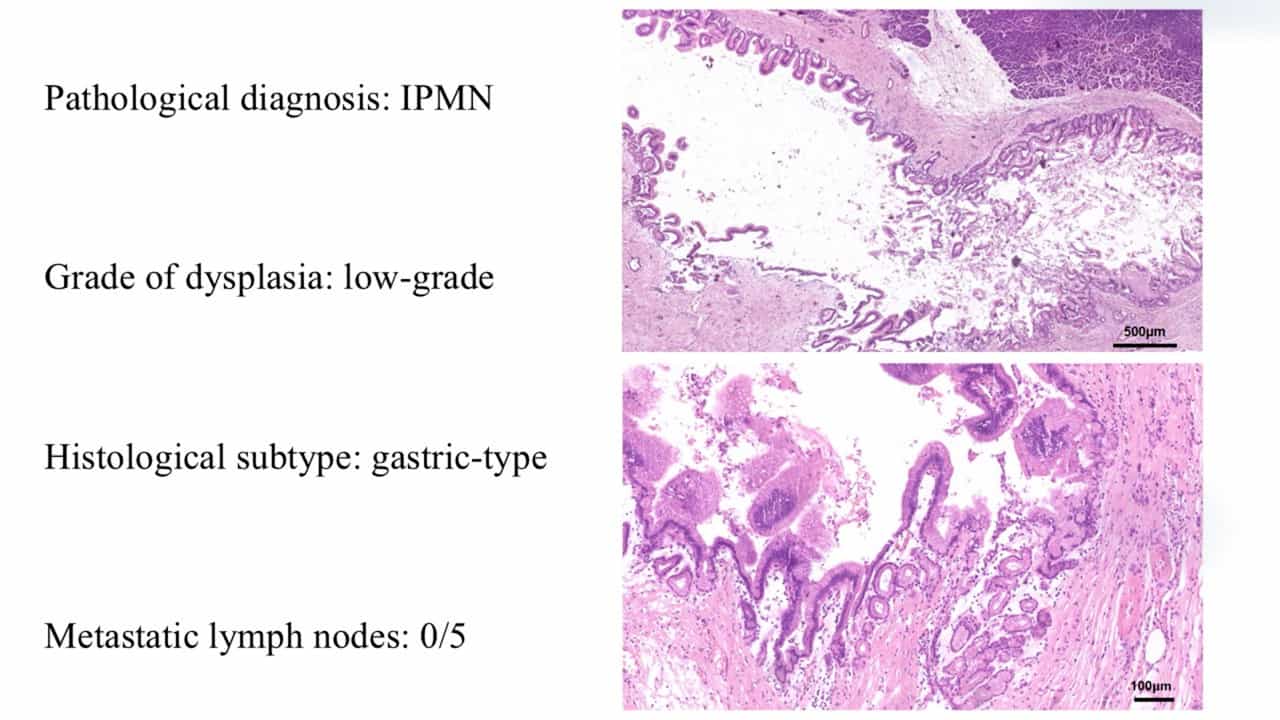
From 1991 to 2006, 150 patients underwent 156 operations for IPMN.
Methods:
Prospectively collected, retrospective review of a single academic institution's experience. All preoperative parameters including a detailed radiologic-based classification of IPMN type, location, distribution, size, number, cytology, and mural nodularity were correlated with IPMN pathology.
Results:
Malignant IPMN was present in 32% of cases, whereas 19% of cases were invasive. IPMN type and main pancreatic duct diameter were significant predictors of malignant IPMN (P<0.001). Side-branch lesion number was negatively associated with invasive IPMN (P=0.03). Side-branch size, location, and distribution did not predict IPMN pathology. The presence of mural nodules was associated with malignant and invasive IPMN (P<0.001; P<0.02). Atypical cytopathology was significantly associated with malignant and invasive IPMN (P<0.001; P<0.001). Multivariate analysis demonstrated mural nodularity and atypical cytopathology were predictive of malignancy and/or invasion in branch-type IPMN.
Conclusions:
To lower the rate of invasive pathology, surgery should be recommended for fit patients with main-duct IPMN and for branch-duct IPMN with mural nodularity or positive cytology irrespective of location, distribution, or size.