Related Experiment Video
Updated: May 7, 2026
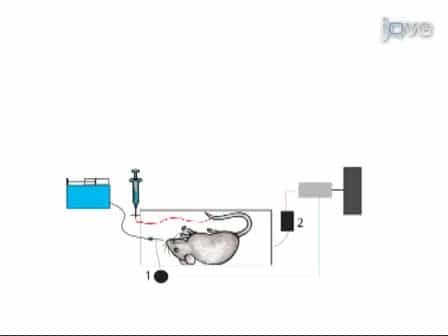

A Reversible, Non-invasive Method for Airway Resistance Measurements and Bronchoalveolar Lavage Fluid Sampling in Mice
Published on: April 14, 2010
Airway remodeling and lack of bronchodilator response in steroid-resistant asthma
Elena Goleva1, Pia J Hauk, Juri Boguniewicz
1Department of Pediatrics, National Jewish Medical and Research Center, Denver, CO 802060, USA.

Background:
Steroid-resistant (SR) asthma is characterized by airway inflammation that fails to resolve despite treatment with corticosteroids, raising concerns that resistance to steroid therapy in asthma could lead to airway remodeling.
Objective:
We sought to determine whether SR asthma is accompanied by decreased airflow reversibility and could lead to airway remodeling.
Methods:
Spirometric results were evaluated for 40 asthmatic patients defined as having SR or steroid-sensitive (SS) asthma on the basis of a 1-week course of oral prednisone. Twenty-three asthmatic patients underwent bronchoscopy with collection of bronchoalveolar lavage (BAL) fluid to analyze markers of airway remodeling in BAL fluid and cells.
Results:
Prednisone significantly improved FEV(1) percent predicted in SS asthma (62.0% +/- 10.9% [mean +/- SD] to 79.4% +/- 11.3%, P < .001) but not in SR asthma (66.9% +/- 10.0% to 65.9% +/- 12.1%). The bronchodilator response was significantly greater in the SS than in the SR group (Delta FEV(1) percent predicted, 33.5% +/- 22.5% vs 15.2% +/- 7.9%; P = .001), regardless of inhaled corticosteroid use. No difference in amounts of matrix metalloproteinase (MMP) 9, PMN elastase, or vascular endothelial growth factor was found in BAL fluid from both groups. Tissue inhibitor of metalloproteinases (TIMP) 1 levels were, however, significantly less in BAL fluid of patients with SR asthma compared with those in patients with SS asthma (921.9 +/- 313.4 vs 2267.0 +/- 456.8 pg/mL, P < .05), resulting in significantly higher MMP-9/TIMP-1 ratios in the BAL fluid of patients with SR asthma (0.24 +/- 0.04 vs 0.11 +/- 0.03, P < .01). Finally, dexamethasone treatment induced TIMP-1 mRNA in BAL fluid cells from patients with SS asthma (P < .01) but not in cells from patients with SR asthma.
Conclusion:
Bronchodilator reversibility is impaired in SR asthma and is associated with a shift in MMP-9/TIMP-1 ratio caused by inability of steroids to enhance TIMP-1 production, potentially promoting proteolytic activity in airways of patients with SR asthma and contributing to chronic airway remodeling.
Clinical Implications:
SR asthma might lead to irreversible airways disease.

Related Concept Videos
 01:17
Drugs Used in Lower Respiratory Disorders: Overview
Bronchodilators, the first step of respiration enhancement, come in various forms, each with its own mechanism...
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.
 01:25
Antiasthma Drugs: β2-Adrenoceptor Agonists
One class of bronchodilators includes β2-adrenoceptor agonists. These agents target the β2-adrenoceptors located on bronchial smooth muscle cells. By stimulating these receptors, β2-agonists induce...
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include:
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features