Related Experiment Video
Updated: Jul 10, 2026


Isolation, Characterization, And High Throughput Extracellular Flux Analysis of Mouse Primary Renal Tubular Epithelial Cells
Published on: June 20, 2018
A neglected case of renal tubular acidosis
Ali Derakhshan1, Mitra Basiratnia, Mohammad Hossein Fallahzadeh
1Shiraz University of Medical Sciences, Shiraz Nephro-Urology Research Center, Shiraz, Iran.

Insights
This case study highlights a child with distal renal tubular acidosis (dRTA) who experienced severe failure to thrive and rickets. The unique physical and x-ray findings, along with treatment response, offer valuable insights into managing this rare pediatric condition.
Area of Science:
- Pediatric Nephrology
- Endocrinology
- Clinical Case Reports
Background:
- Distal renal tubular acidosis (dRTA) is a condition affecting kidney function, potentially leading to growth impairment and bone disease.
- Failure to thrive (FTT) and rickets are known complications of dRTA, impacting a child's development.
- Early diagnosis and intervention are crucial for managing dRTA and its associated symptoms.
Observation:
- A 6-year-old child presented with severe failure to thrive (weighing only 7.8 kg) and profound rickets.
- The patient exhibited unique physical and radiographic findings not typically seen in standard dRTA cases.
- The case involved a detailed four-year follow-up assessing treatment efficacy.
Findings:
- The child showed a notable response to treatment for distal renal tubular acidosis.
- Despite commonality of FTT in dRTA, the specific clinical presentation and radiological signs were distinctive.
- Long-term monitoring revealed the impact of therapeutic interventions on growth and skeletal health.
Implications:
- This case underscores the importance of recognizing atypical presentations of dRTA in children.
- Understanding unique findings can improve diagnostic accuracy and treatment strategies for pediatric renal tubular acidosis.
- The study contributes to the literature on managing complex cases of dRTA with severe failure to thrive and rickets.
Abstract:
In this report, we present a case of a child with distal renal tubular acidosis, severe failure to thrive and profound rickets, who was only 7.8 Kg when presented at 6 years of age. His response to treatment and his follow-up for four years is discussed. Although failure to thrive is a common finding in renal tubular acidosis but the physical and x-ray findings in our case were unique.
Related Concept Videos
 01:29
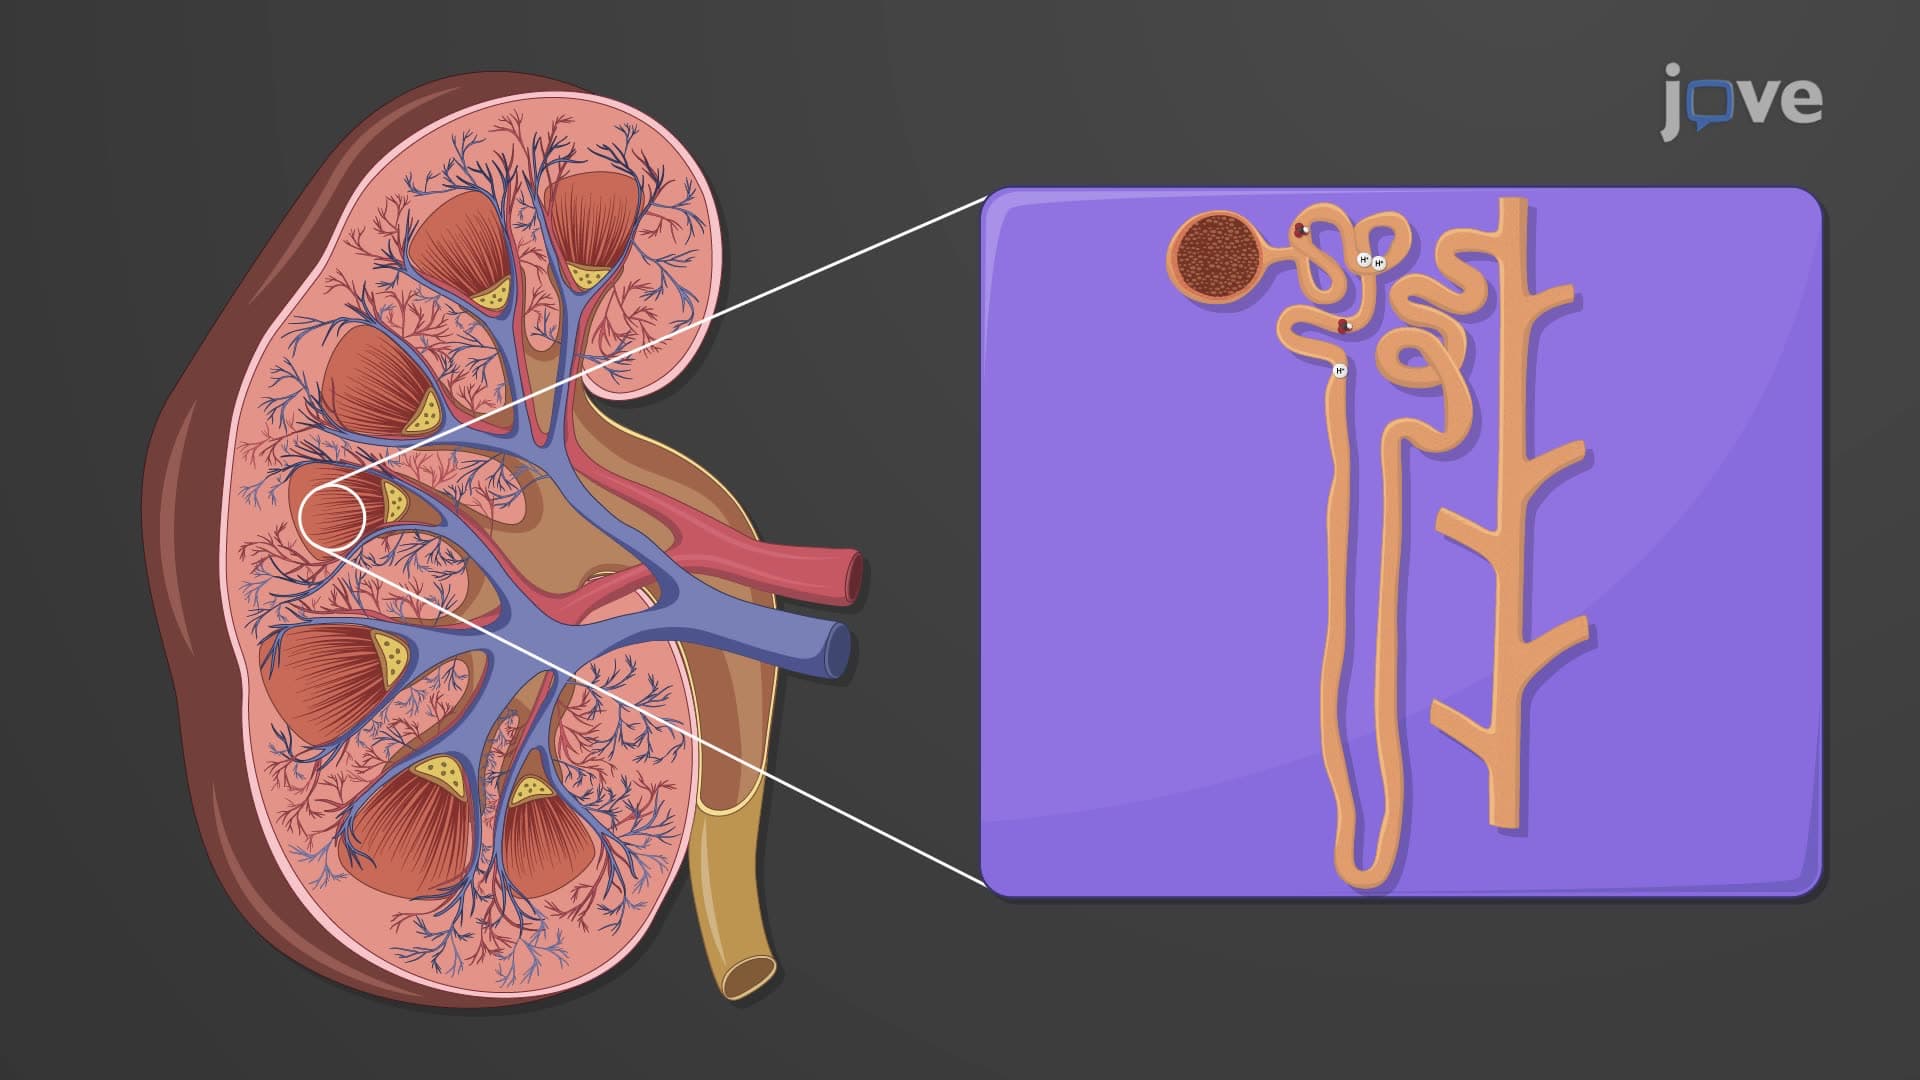
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:24
Renal Tubule and Collecting Duct
Proximal Convoluted Tubule (PCT):
The PCT is the initial segment of the renal tubule, extending from the Bowman's capsule that encloses the glomerulus. Its convoluted structure and microvilli-lined cells increase the surface area for reabsorption. The PCT reabsorbs glucose, amino acids, sodium, and water from the filtrate, ensuring essential...
 01:29
Acute Kidney Injury III: Clinical Manifestations
 01:22
Acute Kidney Injury I: Introduction
 01:29
Acute Kidney Injury II: Pathophysiology
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention