Related Experiment Video
Updated: Jul 10, 2026


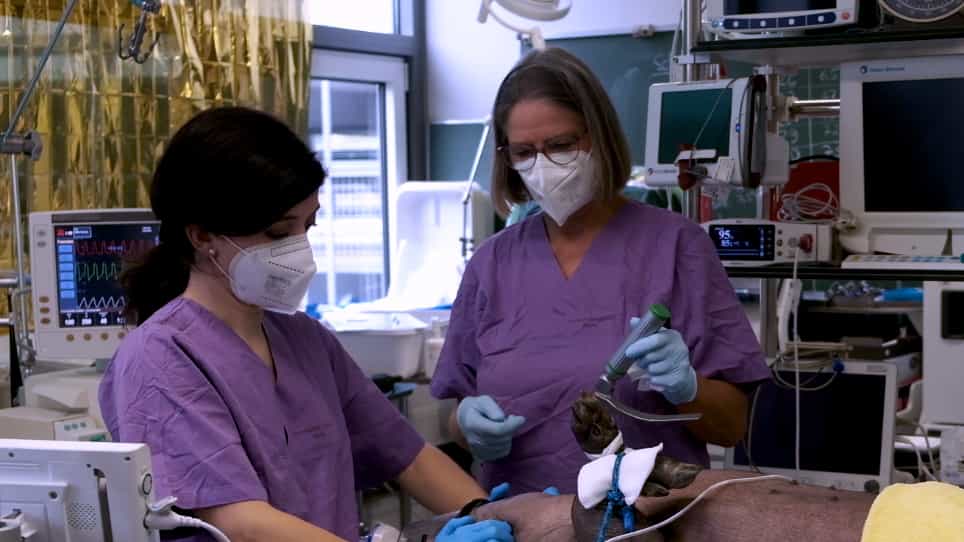
The Rigid Tube as an Alternative in Controlling the Problematic Airway
Published on: June 6, 2020
The unanticipated difficult intubation: rigid or flexible endoscope?
C Rudolph1, A Henn-Beilharz, R Gottschall
1Department of Anaesthesiology and Intensive Care Medicine, Leipzig University Hospital, Leipzig, Germany. rudc@medizin.uni-leipzig.de

Background:
Unanticipated difficult intubation occurs with a frequency between 1.5% and 8.5%. The aim of this study was to compare the use of flexible versus rigid endoscopy in such a patient population, with respect to the preparation time and feasibility of each device.
Methods:
During a four-year observational period, 116 patients with unanticipated difficult intubation were managed either with the flexible fiberscope (FFI group, n= 57) or the rigid Bonfils endoscope (RBI group, n= 59) on a randomized basis.
Results:
The time required for preparing and performing the intubation was significantly shorter in the RBI group: median (IQR) 160 s (118-209 s) as opposed to 229 s (162-326 s) in the FFI group (P=0.001). There were no significant differences with respect to endoscopic visibility or quality of the intubation manoeuvre (P>0.1 each). Causes of unanticipated difficult intubation were mainly as follows: restricted movement of the head and neck (39.7%), a Mallampati class > 2 (35.3%), a short neck (31%) or a thyromental distance < or = 5 cm (28.4%). Postoperative complications associated with the intubation maneuver included slight bleeding (FFI = 8.8% vs RBI = 8.5%; NS), technical problems (12.3 vs 10.2%, NS), hoarseness (15.8 vs 15.3%, P=0.946) and dysphagia (5.3 vs 16.9%, P=0.070).
Conclusion:
Both endoscopic techniques enable quick and safe intubation. The Bonfils method could be the method of choice in cases of already relaxed patients with unanticipated difficult conventional laryngoscopy, presuming that the anaesthetist is familiar with this technique. Because the clinical re-evaluation for possible predictors of difficult intubation revealed no unknown new factors, the preoperative examination for anatomical peculiarities and being aware are the best protection against unanticipated intubation problems.

Related Concept Videos
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:28
Endoscopic Procedures III: Video Capsule Endoscopy
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...