Related Experiment Video
Updated: Jul 10, 2026
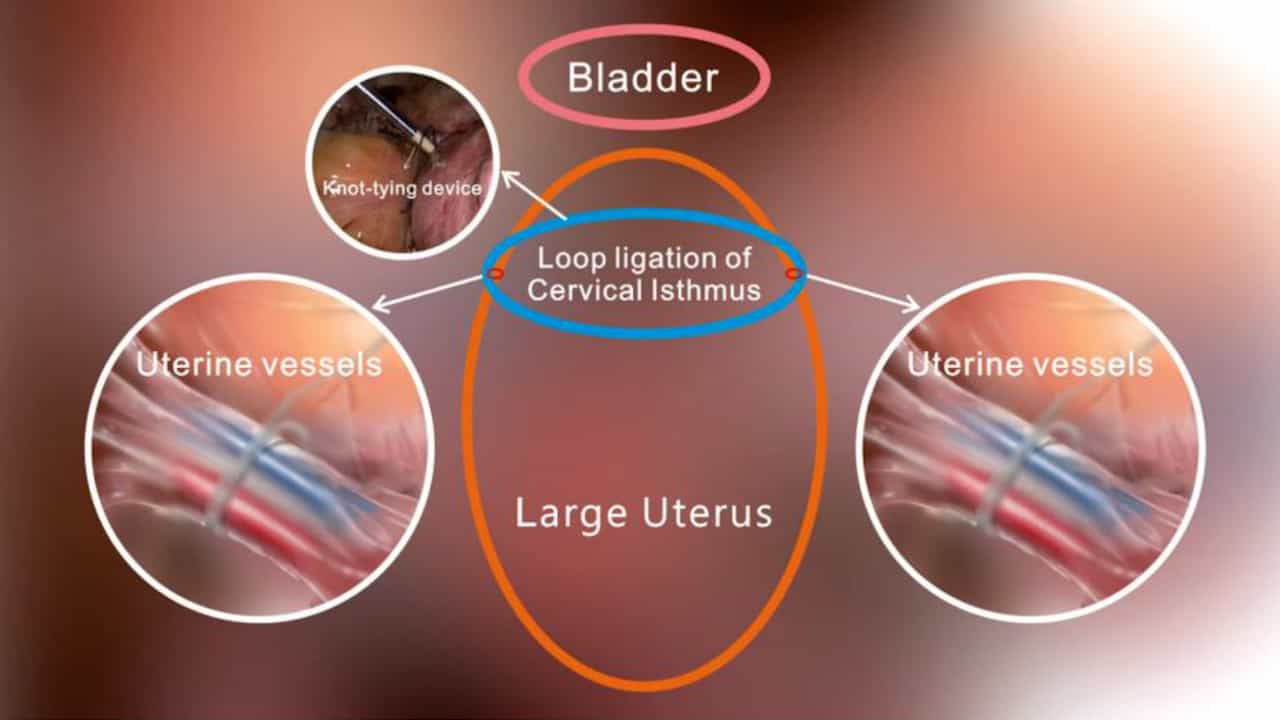

Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Cervical priming with misoprostol prior to transcervical procedures
C Fiala1, K Gemzell-Danielsson, O S Tang
1Gynmed Clinic, Vienna, Austria. christian.fiala@aol.at

Cervical priming with misoprostol has shown to facilitate transcervical procedures and to reduce side-effects. Cervical priming is recommended by several evidence-based guidelines prior to surgical abortion, dilatation and curettage, hysteroscopy and intrauterine device insertion. It is effective in pregnant as well as in non-pregnant women while the results in post-menopausal women are conflicting. Misoprostol is the best suited prostaglandin for a number of reasons: it has a short half-life, few side effects, it is stable at room temperature, it is relatively cheap and the dosage can easily be adjusted according to the clinical need. Various doses, routes, and time intervals between misoprostol application and the intervention have been evaluated. A single dose of 400 microg given sublingually or vaginally 3h before the intervention has given the best efficacy with the least side effects. Higher doses or longer intervals do not improve the effect on the cervix. Pain is a frequent side effect, but usually responds well to NSAIDs. Other side effects are rare.
Cervical priming with misoprostol has shown to facilitate transcervical procedures and to reduce side-effects. Cervical priming is recommended by several evidence-based guidelines prior to surgical abortion, dilatation and curettage, hysteroscopy and intrauterine device insertion. It is effective in pregnant as well as in non-pregnant women while the results in post-menopausal women are conflicting. Misoprostol is the best suited prostaglandin for a number of reasons: it has a short half-life, few side effects, it is stable at room temperature, it is relatively cheap and the dosage can easily be adjusted according to the clinical need. Various doses, routes, and time intervals between misoprostol application and the intervention have been evaluated. A single dose of 400 microg given sublingually or vaginally 3h before the intervention has given the best efficacy with the least side effects. Higher doses or longer intervals do not improve the effect on the cervix. Pain is a frequent side effect, but usually responds well to NSAIDs. Other side effects are rare.