

ECG changes following cardioversion and defibrillation
Florim Cuculi1, Richard Kobza, Paul Erne
1Department of Cardiology, Kantonsspital Luzern, Luzern, Switzerland.

Insights
External defibrillation and cardioversion can cause temporary QRS voltage loss in patients, particularly those with coronary artery disease. This reversible phenomenon may be linked to tissue edema or myocardial stunning.
Area of Science:
- Cardiology
- Electrophysiology
- Medical Devices
Background:
- Changes in QRS amplitude after defibrillation/cardioversion are undocumented in humans.
- Electrical cardioversion and defibrillation are common procedures for tachyarrhythmias.
Purpose of the Study:
- To investigate and report the phenomenon of QRS voltage amplitude changes following external defibrillation or cardioversion.
- To compare these changes in patients with and without coronary artery disease (CAD).
Main Methods:
- Prospective analysis of patients undergoing external cardioversion/defibrillation.
- Categorization into groups based on CAD/acute coronary syndrome (ACS) status and internal cardioverter defibrillator (ICD) use.
- Serial ECG recordings to measure QRS amplitude sums (Sigma) and compare with baseline values.
Main Results:
- Significant QRS amplitude reduction observed, particularly in patients with CAD/ACS (-35% precordial, -16% peripheral R amplitude).
- Reversible voltage loss noted, with changes appearing after 23 hours and resolving by 62 hours.
- Most pronounced attenuation in patients with ACS, CAD, and those requiring chest compressions.
Conclusions:
- A reversible loss of QRS voltage following external defibrillation/cardioversion is reported.
- Potential causes include tissue edema from electrical/traumatic injury or myocardial stunning.
- Further research with larger cohorts is needed to elucidate the exact pathophysiological mechanism.
Principles:
changes of the QRS amplitude following defibrillation or cardioversion have never been reported in humans.
Methods:
prospective analysis of patients externally cardioverted or defibrillated for ventricular and supraventricular tachyarrhythmias. Patients with coronary artery disease (CAD) and acute coronary syndrome (ACS) formed group A and patients without CAD but with external cardioversion/defibrillation formed group B. Patients in the control group (group C) experienced a shock by an Internal Cardioverter Defibrillator (ICD). All patients underwent the same study protocol: serial ECG's were recorded and sums (Sigma) of the QRS amplitude created separately for the precordial and peripheral leads. Sigma were then compared with baseline values and changes indicated as percentage (%).
Results:
We included a total of 45 patients in our study: 21 patients (47%) in group A, 11 patients (24%) in group B and 13 patients (29%) in group C. Median age was 66 years in group A, 55 in group B and 52 in group C. In group A mean change of the R amplitude was -35% in precordial and -16% in the peripheral leads. In group B mean change of the R amplitude was -16% in the precordial and -2% in the peripheral leads. The QRS amplitude changed -23% in the precordial leads in group A and -14% in group B. 13 patients with external defibrillation or cardioversion of group A + B and all patients of the control group (n = 13) showed no voltage changes. The most pronounced R and QRS attenuation was seen in patients with acute coronary syndrome, CAD and those in whom manual chest compressions had been necessary. Changes appeared after a mean period of 23 hours and returned to normal after a mean of 62 hours.
Conclusions:
we report the phenomenon of reversible voltage loss after external defibrillation or cardioversion. A possible explanation for this phenomenon might be tissue oedema in the chest area after electrical and traumatic injury. An alternative reason might be myocardial stunning. The exact pathophysiological mechanism leading to reversible voltage attenuation remains unclear and needs further exploration in studies with a larger sample of patients.
More Related Videos


Related Concept Videos
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:29
Electrocardiogram
Three major waveforms are present in a typical ECG recording: the P wave, the QRS complex, and the T...
 01:30
Cardiac Action Potential
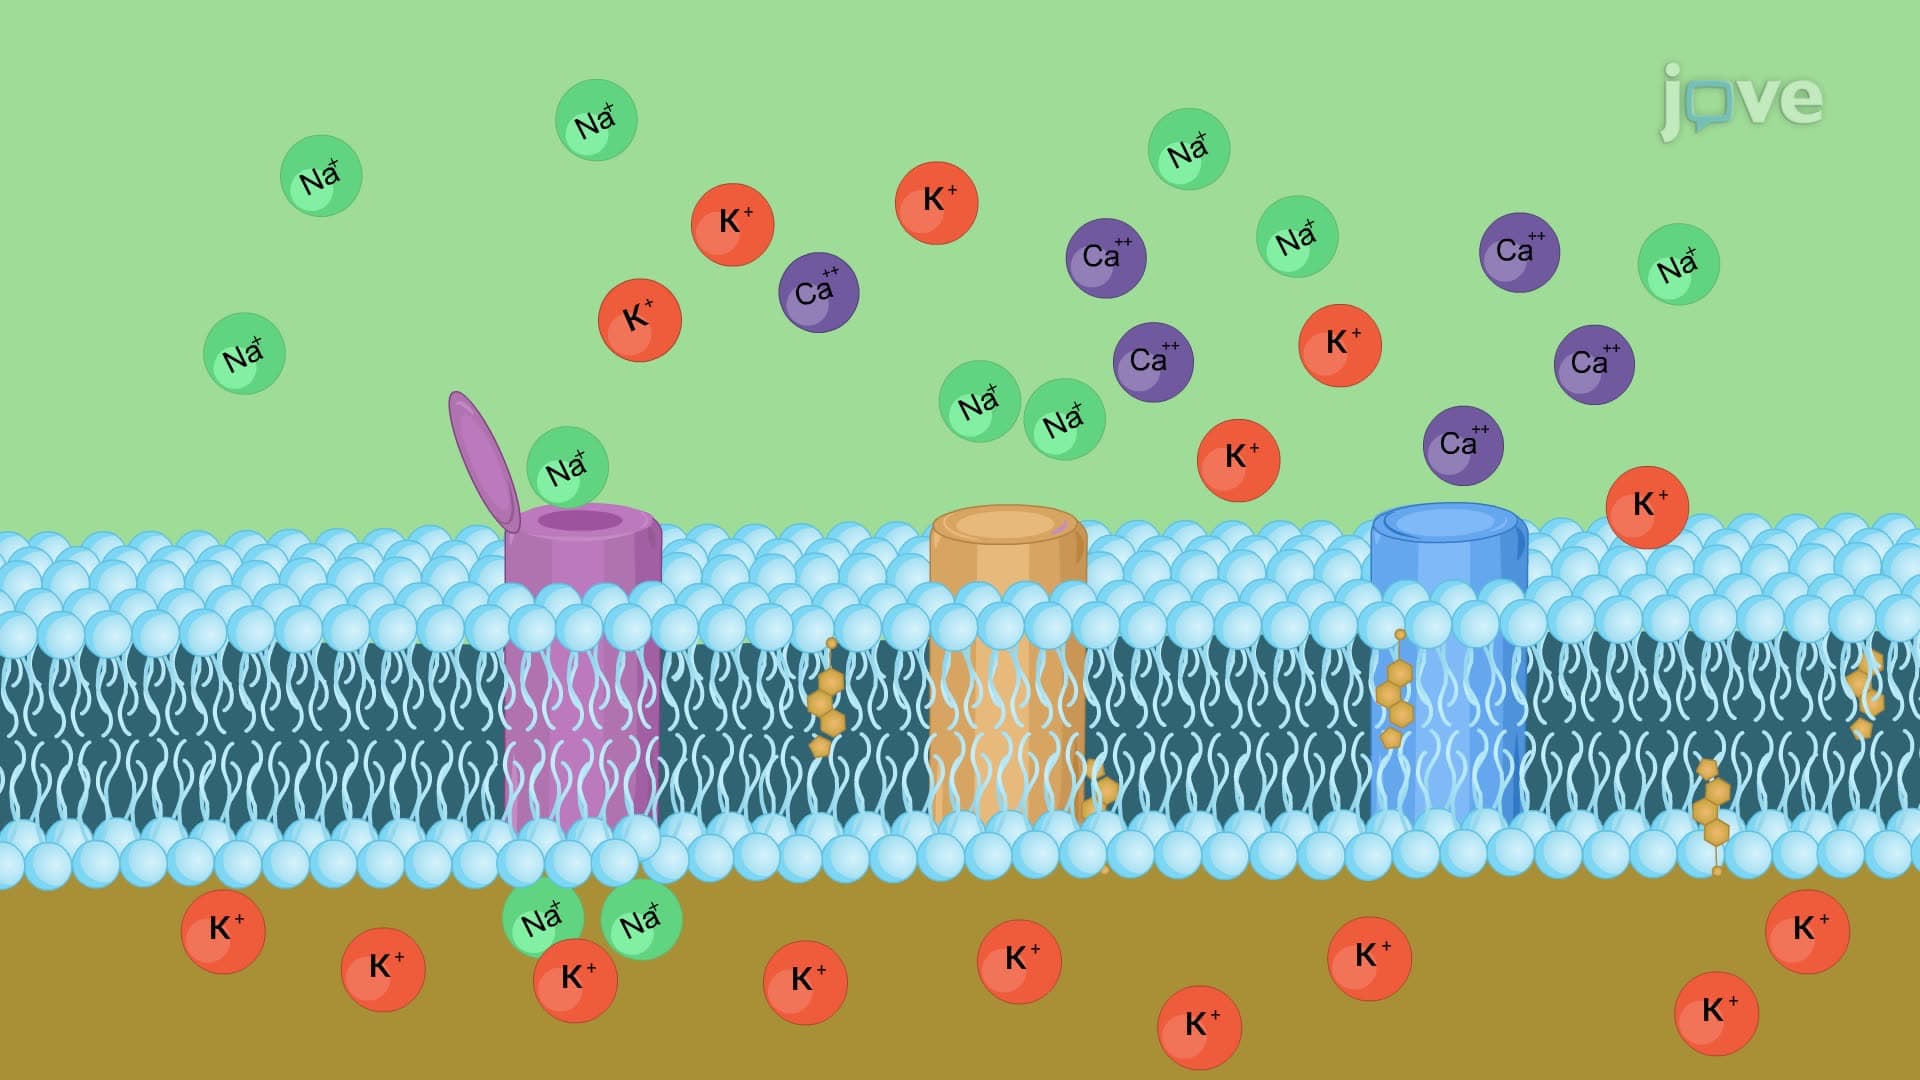
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials
 01:25
Correlation between ECG and Cardiac Cycle
A cardiac action potential originates in the SA node and spreads throughout the atria and the AV node in approximately 0.03 seconds. This results in the P wave in an ECG and triggers atrial contraction. The action potential is then briefly slowed at the AV node, allowing the atria to contract and fill the ventricles with blood before...
 01:29
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow heart...
 01:28
Electrocardiogram Fundamentals
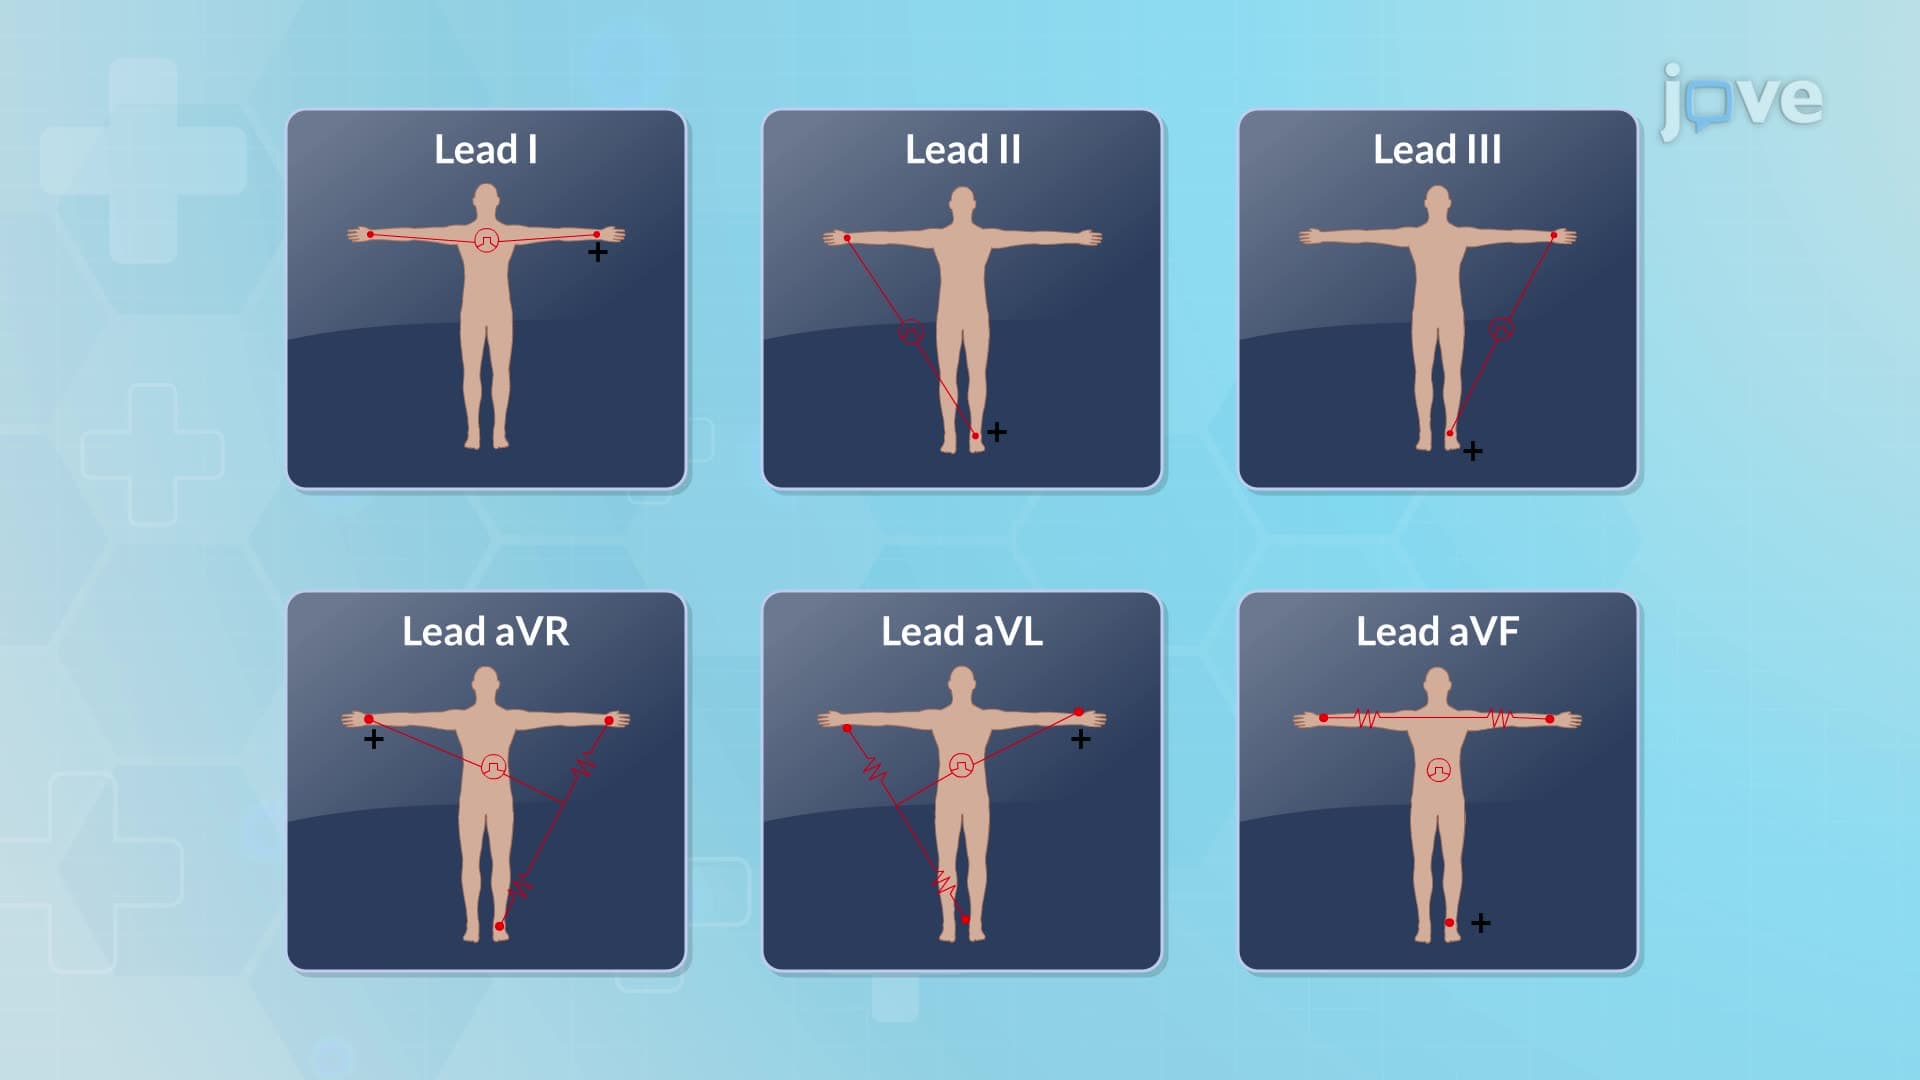
An electrocardiogram (ECG) is a diagnostic tool for identifying cardiac conditions such as arrhythmias, conduction abnormalities, and myocardial ischemia.
Definition
An electrocardiogram (ECG) visualizes the heart's electrical activity by tracing the electrical movement associated with each heartbeat on a graph or monitor. As the heart beats, an electrical wave passes through it, correlating with the cardiac cycle events.
Parts of an ECG
An ECG utilizes electrodes on the skin to...