Related Experiment Video
Updated: Jul 9, 2026


Auricular Point Acupressure Therapy: A Safe and Effective Treatment for Postsurgical Abortion Recovery
Published on: February 3, 2026
APC resistance during the normal menstrual cycle
Marianne van Rooijen1, Angela Silveira, Stella Thomassen
1Department of Woman and Child Health, Division of Obstetrics and Gynaecology, Karolinska University Hospital, S-171 76 Stockholm, Sweden. marianne.vanrooijen@karolinska.se

Abstract:
Increased serum levels of endogenous as well as exogenous estrogen are regarded to be responsible for acquired activated protein C (APC) resistance. It was the objective of this study to evaluate whether the physiological increase in serum estradiol concentration during the normal menstrual cycle affects the individual's sensitivity to APC. Seventy-two women with normal menstrual cycles were included in the study. Blood samples for analysis of estradiol (E2), progesterone (P4) and APC resistance were drawn at two time points of the menstrual cycle (day 3-5 and day 22-25). Two methods of measuring APC resistance were used: the activated partial thromboplastin time (aPTT)-based assay and the endogenous thrombin potential (ETP)-based APC resistance test. Independent of the method used, no changes in APC resistance were found, even though the E2 concentration increased significantly between the two menstrual phases. No correlations between E2 levels and APC resistance, P4 levels and APC resistance or changes in E2 concentrations and changes in APC resistance were detected. Ten women were carriers of the factor V(Leiden) mutation. Their baseline APC resistance was increased, but their response to elevated E2 during the menstrual cycle did not differ from that of non-carriers. In conclusion, our observations suggest that physiological differences in serum levels of estradiol and progesterone between the early follicular and the luteal phase in a normal menstrual cycle do not have any significant impact on the individual's sensitivity to APC.
Related Concept Videos
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:19
The Menstrual Cycle
The menstrual phase occurs from days 1 to 5 and involves the shedding of the stratum functionalis, as a uterine...
 01:19
Secretory Phase
Following ovulation, the corpus luteum, a temporary endocrine structure, produces progesterone and estrogens. These hormones stimulate the growth and coiling of endometrial...
 01:18
Menses Phase
When fertilization does not occur, the corpus luteum deteriorates, causing a significant drop in the levels of estrogen and progesterone in the body. This hormonal decrease triggers the release of prostaglandins, which cause the uterine...
 01:20
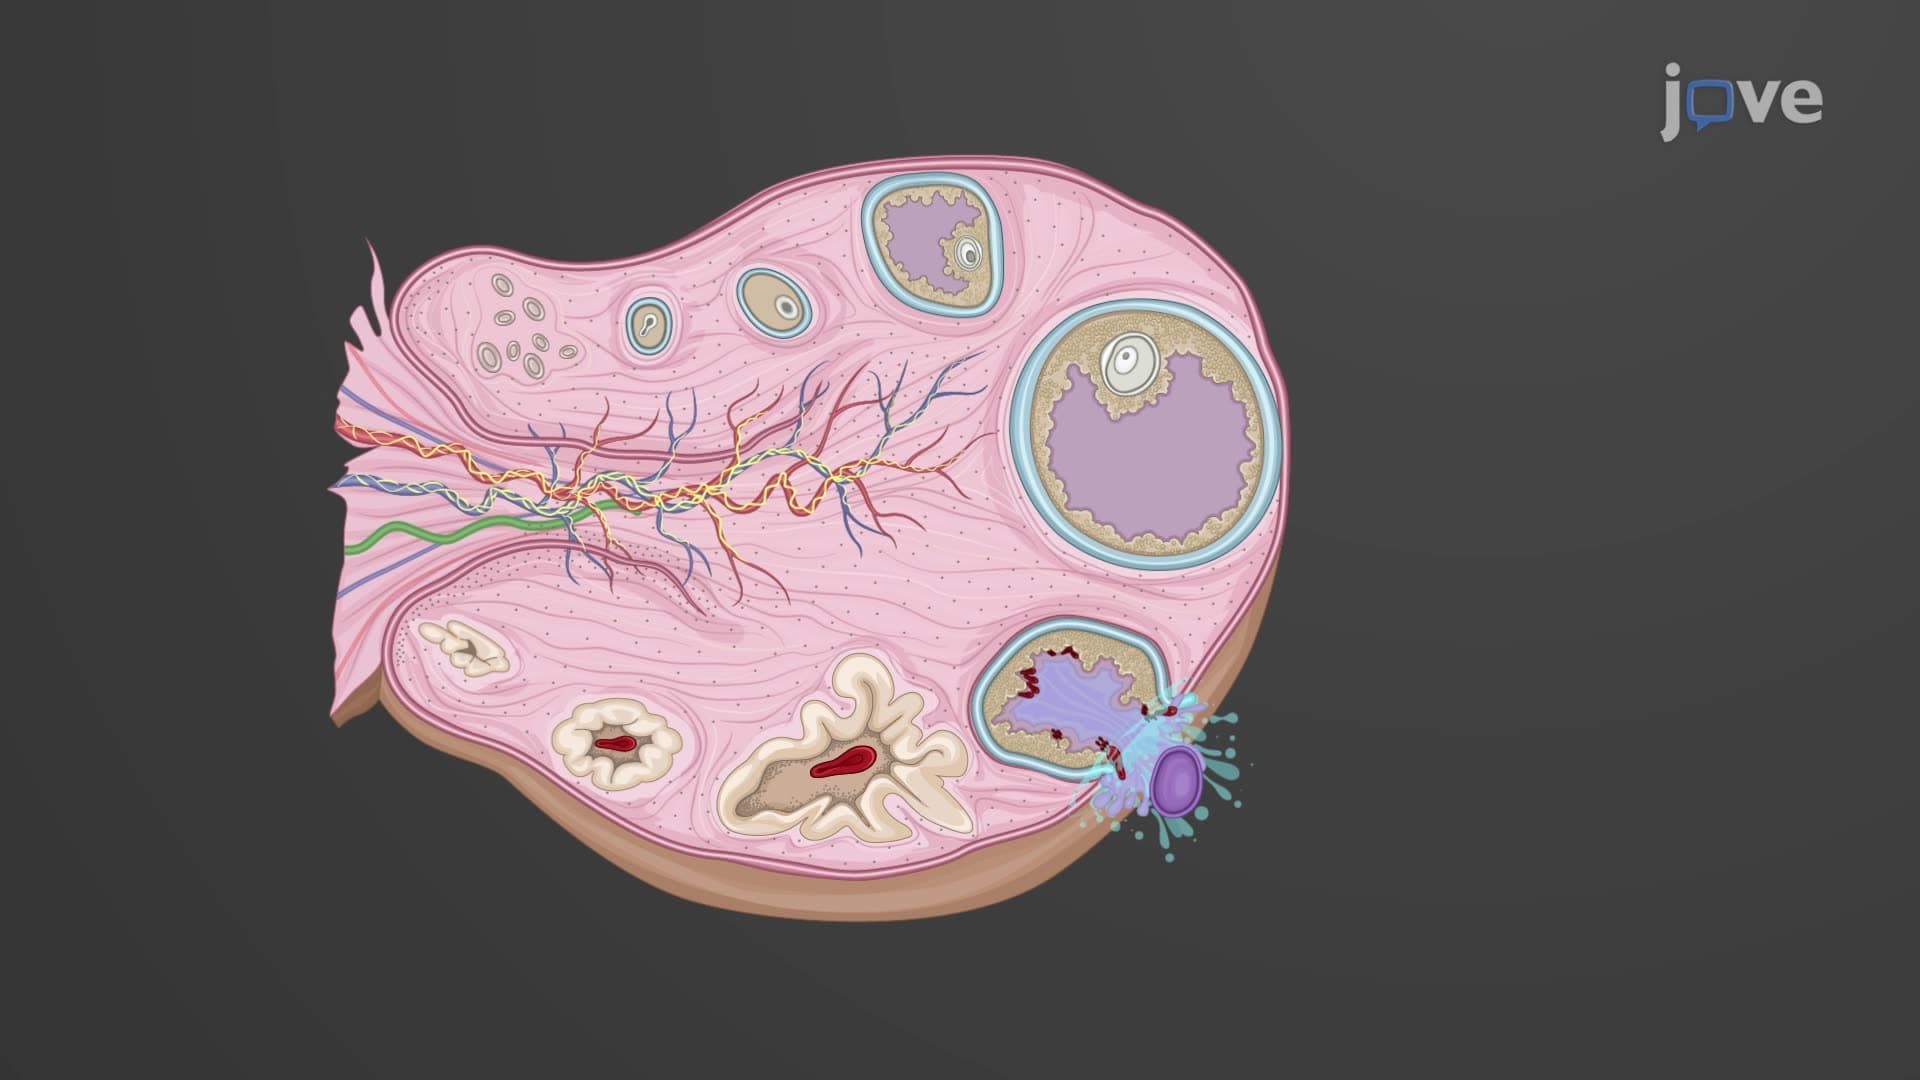
Proliferative Phase
Notably, the stratum basale, the basal layer of the endometrium, including the basal parts of the uterine glands, remains unaffected by menstruation. Stem cells in this layer undergo mitosis, regenerating the stratum functionalis and thickening the...
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...