Related Experiment Video
Updated: Jul 8, 2026

Electrocardiogram Recordings in Anesthetized Mice using Lead II
Published on: June 20, 2020
The effects of dexmedetomidine on cardiac electrophysiology in children
Gregory B Hammer1, David R Drover, Hong Cao
1Department of Anesthesiology, Lucile Packard Children's Hospital and Stanford University School of Medicine, Stanford, California, USA. ham@stanford.edu

Insights
Dexmedetomidine (DEX) depresses cardiac conduction in children, affecting heart rate and blood pressure. Its use during pediatric electrophysiology studies may pose risks for bradycardia and AV block.
Area of Science:
- Pediatric Cardiology
- Clinical Anesthesiology
- Pharmacology
Background:
- Dexmedetomidine (DEX) is an alpha2-adrenergic agonist approved for short-term adult sedation.
- DEX use in pediatric sedation and anesthesia is increasing, despite lack of FDA approval for this age group.
- Concerns exist regarding DEX's hemodynamic effects, with no data on its impact on pediatric cardiac conduction.
Purpose of the Study:
- To characterize the effects of dexmedetomidine on cardiac conduction in pediatric patients.
- To evaluate hemodynamic and electrophysiologic changes during DEX administration in children.
Main Methods:
- Twelve pediatric patients (5-17 years) undergoing electrophysiology study received DEX (1 microg/kg IV followed by 0.7 microg x kg(-1) x h(-1) infusion).
- Hemodynamic variables (heart rate, blood pressure) and cardiac electrophysiologic variables were measured before and during DEX administration.
Main Results:
- Dexmedetomidine administration led to a significant decrease in heart rate and a significant increase in arterial blood pressure.
- Sinus node function was significantly affected, indicated by increased sinus cycle length and sinus node recovery time.
- Atrioventricular nodal function was depressed, evidenced by prolonged Wenckeback cycle length and PR interval.
Conclusions:
- Dexmedetomidine significantly depresses sinus and atrioventricular nodal function in pediatric patients.
- The observed hemodynamic changes (bradycardia, hypertension) and conduction system effects suggest DEX may not be ideal for pediatric electrophysiology studies.
- Caution is advised when using DEX in pediatric patients at risk for bradycardia or atrioventricular nodal block.
Background:
Dexmedetomidine (DEX) is an alpha2-adrenergic agonist that is approved by the Food and Drug Administration for short-term (<24 h) sedation in adults. It is not approved for use in children. Nevertheless, the use of DEX for sedation and anesthesia in infants and children appears to be increasing. There are some concerns regarding the hemodynamic effects of the drug, including bradycardia, hypertension, and hypotension. No data regarding the effects of DEX on the cardiac conduction system are available. We therefore aimed to characterize the effects of DEX on cardiac conduction in pediatric patients.
Methods:
Twelve children between the ages of 5 and 17 yr undergoing electrophysiology study and ablation of supraventricular accessory pathways had hemodynamic and cardiac electrophysiologic variables measured before and during administration of DEX (1 microg/kg IV over 10 min followed by a 10-min continuous infusion of 0.7 microg x kg(-1) x h(-1)).
Results:
Heart rate decreased while arterial blood pressure increased significantly after DEX administration. Sinus node function was significantly affected, as evidenced by an increase in sinus cycle length and sinus node recovery time. Atrioventricular nodal function was also depressed, as evidenced by Wenckeback cycle length prolongation and prolongation of PR interval.
Conclusion:
DEX significantly depressed sinus and atrioventricular nodal function in pediatric patients. Heart rate decreased and arterial blood pressure increased during administration of DEX. The use of DEX may not be desirable during electrophysiology study and may be associated with adverse effects in patients at risk for bradycardia or atrioventricular nodal block.
Related Concept Videos
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...
 01:26
Heart Failure Drugs: Inotropic Agents
 01:20
Antiarrhythmic Drugs: Class IV Agents as Calcium Channel Blockers
Verapamil, a calcium channel blocker, inhibits calcium movement across myocardial cell membranes and vascular smooth muscle. This results in the dilation of coronary and...
 01:12
Antiarrhythmic Drugs: Class III Agents as Potassium Channel Blockers
 01:30
Cardiac Action Potential
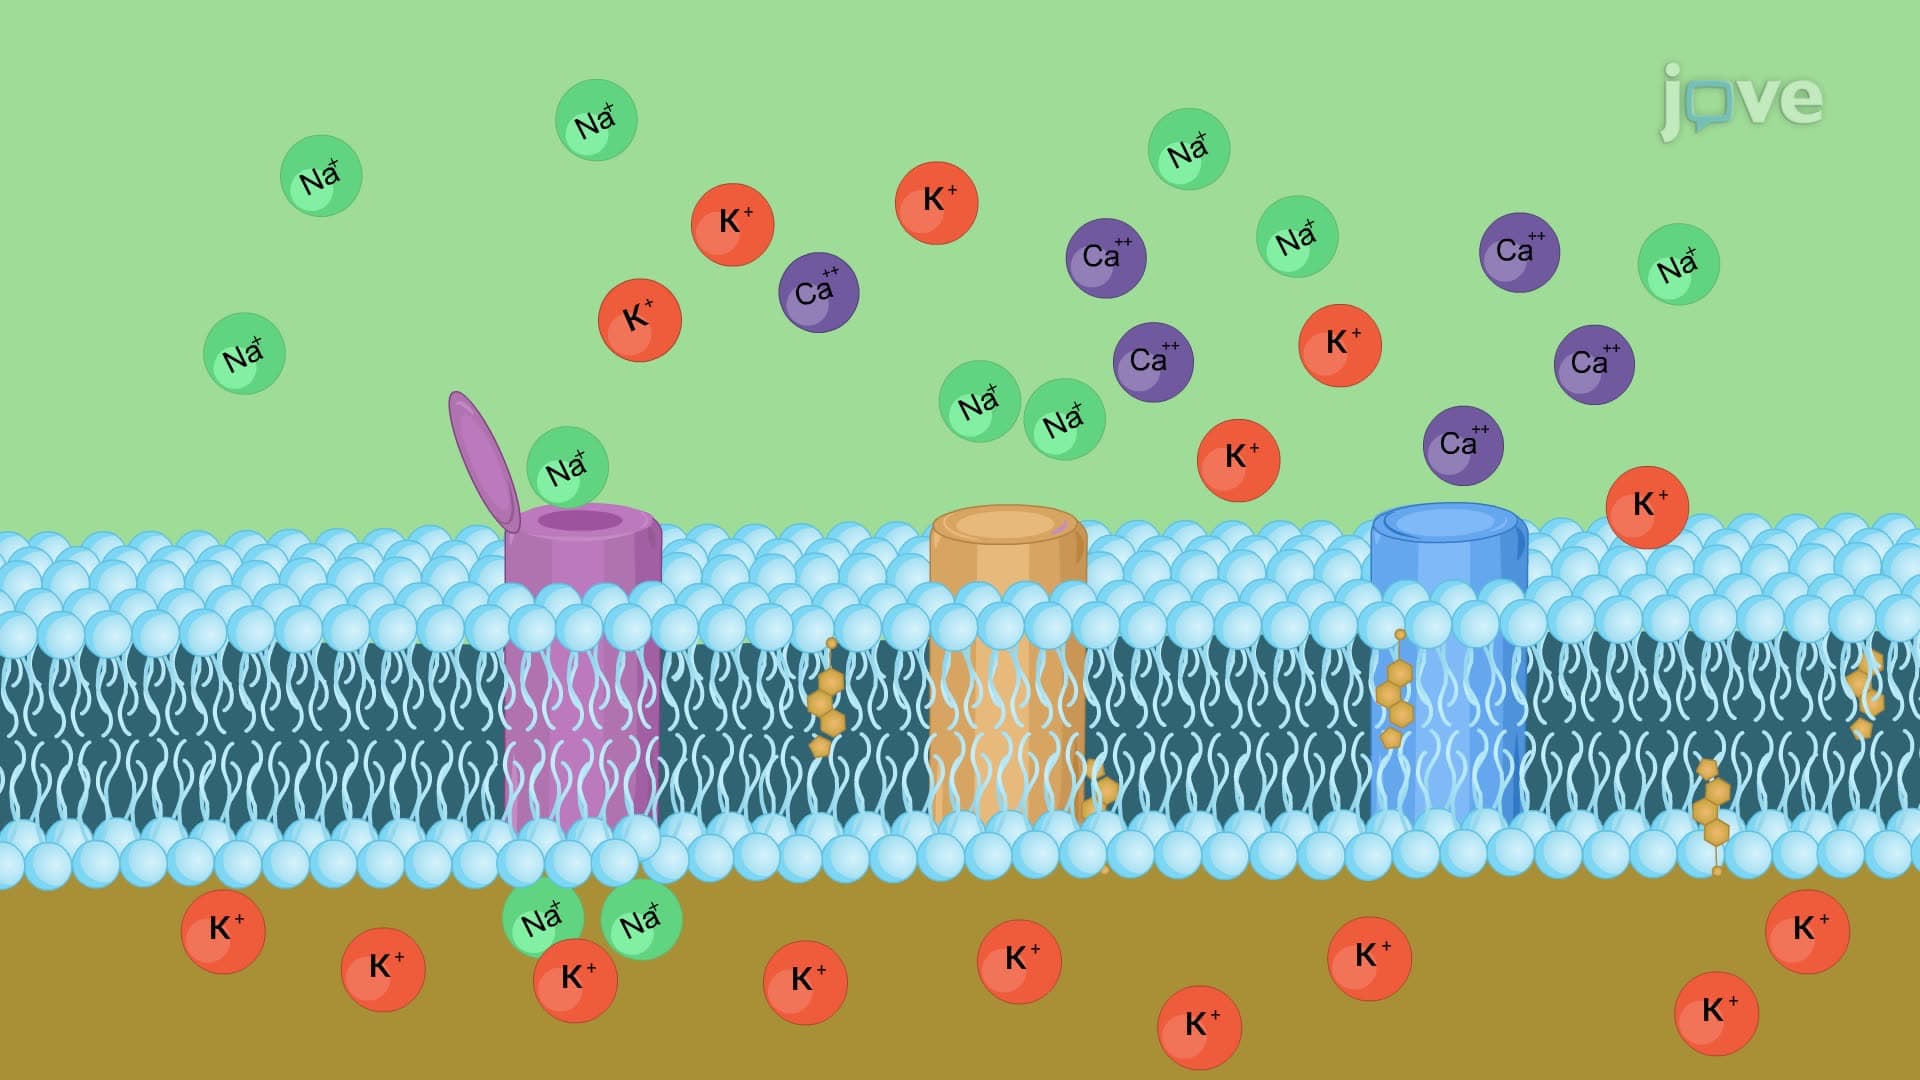
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials