Related Experiment Video
Updated: Jul 7, 2026
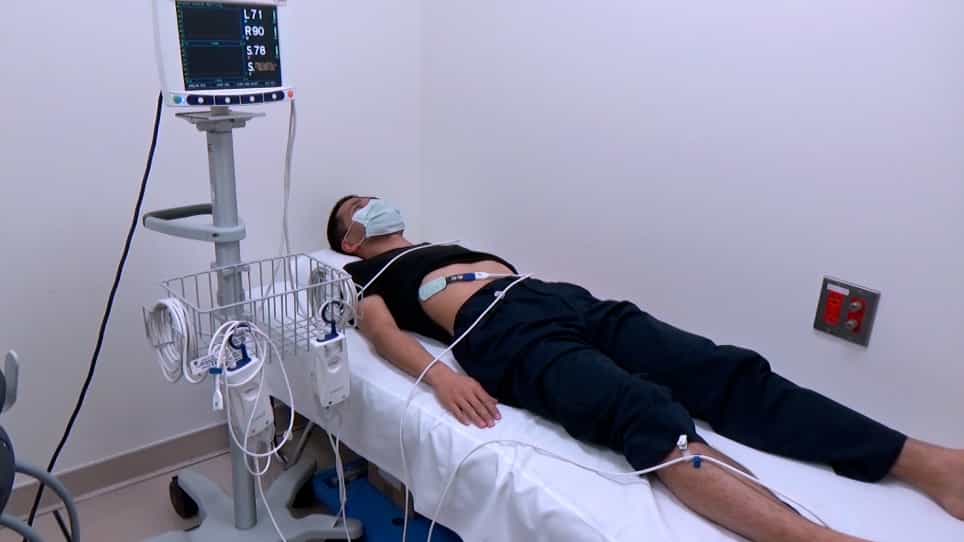
Measurement of Tissue Oxygenation Using Near-Infrared Spectroscopy in Patients Undergoing Hemodialysis
Published on: October 2, 2020
Oral intake during hemodialysis: is there an association with intradialytic hypotension?
Mark Benaroia1, Eduard A Iliescu
1Humber River Regional Hospital, Division of Nephrology, Toronto, Ontario, Canada. m.benaroia@utoronto.ca

Oral intake (OI) of food and fluid has been associated with hypotension during hemodialysis (HD). Trials evaluating this relationship are small. The objective of this study was to quantify OI and to examine its association with hypotension during HD. This is a cross-sectional retrospective chart review study of 3 consecutive HD runs (dialysate iCa=1.25 mmol/L) in 126 stable HD patients (n=378). For each run, the calculation for OI=total ultrafiltration-(net weight loss+IV fluids given). Hypotension was defined as a systolic blood pressure of <100 mmHg at any point during the run. The mean age of the patients was 60.9 years, 38.2% were female, 30.2% had diabetes mellitus, and the majority were Caucasian. The mean (SD) OI was 0.27 (0.352) L/run, range -1.061 to 1.901 L/run, with a normal distribution. In bivariate analysis, there was no correlation of OI with systolic blood pressure, diastolic blood pressure, or mean blood pressure (BP), and the mean OI did not differ among runs with hypotension (n=78) compared with uncomplicated runs (p=0.93). Oral intake was not predictive of hypotension in a multiple logistic regression model controlling for vintage, age, sex, BP medications, coronary disease, dialysis day and shift, diabetes mellitus, s-Ca, Na and ultrafiltration profiles, and dialysis temperature, even when the analysis was restricted to runs where the patients reached the prescribed dry weight within 0.1 kg. The results of this study suggest that the mean OI during dialysis is just over 0.25 kg, with some patients consuming several kilograms. The clinical significance of OI is uncertain. We did not find an association between OI and hypotension. It is likely that this association was confounded by failure to achieve the prescribed dry weight in a proportion of patients with a high OI, as well as interventions implemented in response to hypotension in previous runs. For example, patients with previous episodes of low BP are advised to limit OI, are prescribed profiles, and so on. There may be other deleterious effects of high OI including hypertension and cardiac disease. The generalizability of the results of this largely Caucasian study population is a recognized limitation. Further prospective and blinded studies are needed to examine the association between OI and hypotension, the long-term clinical consequences of OI, and to define thresholds for recommended OI during dialysis.
Oral intake (OI) of food and fluid has been associated with hypotension during hemodialysis (HD). Trials evaluating this relationship are small. The objective of this study was to quantify OI and to examine its association with hypotension during HD. This is a cross-sectional retrospective chart review study of 3 consecutive HD runs (dialysate iCa=1.25 mmol/L) in 126 stable HD patients (n=378). For each run, the calculation for OI=total ultrafiltration-(net weight loss+IV fluids given). Hypotension was defined as a systolic blood pressure of <100 mmHg at any point during the run. The mean age of the patients was 60.9 years, 38.2% were female, 30.2% had diabetes mellitus, and the majority were Caucasian. The mean (SD) OI was 0.27 (0.352) L/run, range -1.061 to 1.901 L/run, with a normal distribution. In bivariate analysis, there was no correlation of OI with systolic blood pressure, diastolic blood pressure, or mean blood pressure (BP), and the mean OI did not differ among runs with hypotension (n=78) compared with uncomplicated runs (p=0.93). Oral intake was not predictive of hypotension in a multiple logistic regression model controlling for vintage, age, sex, BP medications, coronary disease, dialysis day and shift, diabetes mellitus, s-Ca, Na and ultrafiltration profiles, and dialysis temperature, even when the analysis was restricted to runs where the patients reached the prescribed dry weight within 0.1 kg. The results of this study suggest that the mean OI during dialysis is just over 0.25 kg, with some patients consuming several kilograms. The clinical significance of OI is uncertain. We did not find an association between OI and hypotension. It is likely that this association was confounded by failure to achieve the prescribed dry weight in a proportion of patients with a high OI, as well as interventions implemented in response to hypotension in previous runs. For example, patients with previous episodes of low BP are advised to limit OI, are prescribed profiles, and so on. There may be other deleterious effects of high OI including hypertension and cardiac disease. The generalizability of the results of this largely Caucasian study population is a recognized limitation. Further prospective and blinded studies are needed to examine the association between OI and hypotension, the long-term clinical consequences of OI, and to define thresholds for recommended OI during dialysis.
Related Concept Videos
 01:25
Hemodialysis III: Nursing Management
 01:24
Hemodialysis II: Procedure and Complications
 01:20
Acute Kidney Injury V: Interprofessional Care
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:25
Hemodialysis I: Introduction
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant