Related Experiment Video
Updated: Jul 7, 2026


Tension-Free Weight-Bearing Model of Steroid-Induced Osteonecrosis of Femoral Head in Rats
Published on: September 27, 2024
Glucocorticoid-induced osteoporosis: a review on pathophysiology and treatment options
1Center for Rheumatology, Máxima Medical Center, Eindhoven, The Netherlands. r.denijs@mmc.nl

Abstract:
Glucocorticoids, often regarded as ancient drugs, are still frequently used in modern medicine because of their strong anti-inflammatory and immunosuppressive properties. Nowadays, the side effects of glucocorticoids are well-known and physicians often anticipate on these side effects. Bone loss is one of the most important side effects of glucocorticoid use, even in low doses. The main effect of glucocorticoids on bone is inhibition of osteoblast function, leading to a decrease in bone formation. Also nongenomic effects (mediated by glucocorticoid interactions with biological membranes, either through binding to membrane receptors or by physicochemical interactions) may have a role in the pathogenesis of glucocorticoid-induced osteoporosis. Several studies and reports show a decrease in bone mineral density and an increased risk of fractures during glucocorticoid use. Prior and current exposure to glucocorticoids increases the risk of fractures beyond that explained by values of bone mineral density. This discrepancy could be explained by osteocyte apoptosis leading to rapid weakening of bone architecture and increase in fractures risk. Bone loss starts promptly after initiation of glucocorticoids and is mainly taking place in the first six months of treatment. Bone loss is predominantly found in bone with a high trabecular content, like vertebrae. The risk of glucocorticoid-induced osteoporosis can be reduced by general measurements like prescribing glucocorticoids in a low dose and for a short period of time. Furthermore, pharmacological intervention for prevention of glucocorticoid-induced osteoporosis is needed depending on glucocorticoid dose, expected duration of glucocorticoid treatment, age and gender of the patient and sometimes bone mineral density at start of the glucocorticoid treatment. Bisphosphonates seem to be the first choice of pharmacological intervention for prevention and treatment of glucocorticoid-induced osteoporosis and are cost-effective in subgroups of patients (depending on age, gender, glucocorticoid dose and fracture history). There is no evidence that one specific bisphosphonate is superior to another bisphosphonate due to lacking of head-to-head studies on glucocorticoid-induced osteoporosis. A recent study showed that alendronate is superior to alfacalcidol in prevention of glucocorticoid-induced osteoporosis in patients starting glucocorticoids of 7.5 mg or more on a daily basis. Calcium and plain vitamin D3 supplementation are considered as important support for prevention and treatment of glucocorticoid-induced osteoporosis. Despite the increased knowledge on bone loss and fracture risk during glucocorticoid use and the possibilities of pharmacological intervention of it, studies made clear that the care given by physicians in prevention and treatment of glucocorticoid-induced osteoporosis needs to be optimized in future years. Further training of health care workers in pathophysiology, general measurements and pharmacological intervention for prevention and treatment of glucocorticoid-induced osteoporosis, is needed.
Related Concept Videos
 01:21
Drugs for Treatment of Crohn's Disease in IBD Using Glucocorticoids
 01:31
Osteoclasts in Bone Remodeling
 01:19
Cushing Syndrome II: Pathophysiology
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:40
Bone Remodeling
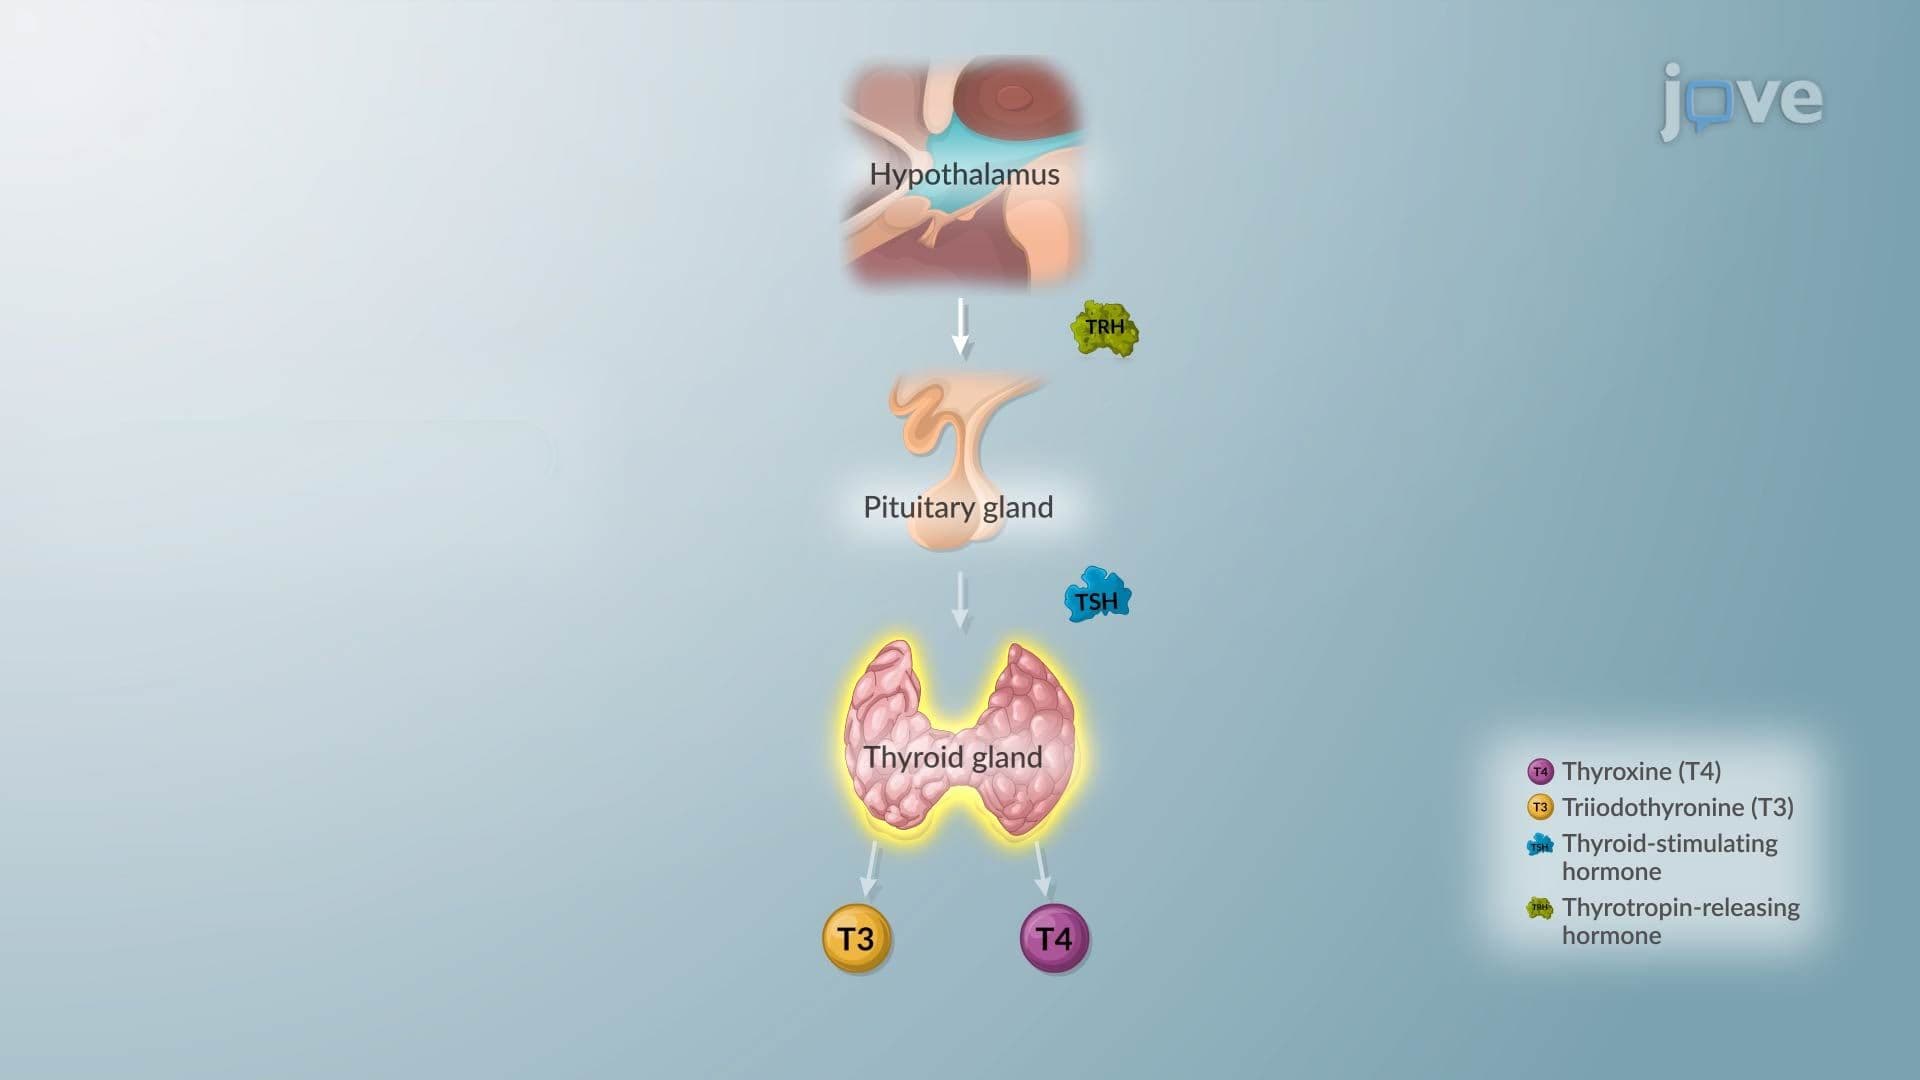 01:23
Hypothyroidism II: Pathophysiology