Related Experiment Video
Updated: Jul 7, 2026


Assessment of the Metabolic Effects of Isocaloric 2:1 Intermittent Fasting in Mice
Published on: November 27, 2019
Energy-restricted diets based on a distinct food selection affecting the glycemic index induce different weight loss
Itziar Abete1, Dolores Parra, J Alfredo Martinez
1Department of Physiology and Nutrition, University of Navarra, Irunlarrea s/n., 31008 Pamplona, Spain. iabetego@yahoo.es

Background & Aims:
Low glycemic index (GI) based diets could influence the accompanying physiological adaptations to energy restriction in the treatment of obesity. It was aimed to investigate the effects of two energy-restricted diets with different food distribution and GI values on weight loss and energy metabolism in the nutritional treatment of obesity.
Subjects And Methods:
Participants (n=32; BMI: 32.5+/-4.3 kg/m(2)) were randomly assigned to follow two energy-restricted diets with higher-GI or lower-GI for 8 weeks. The energy restriction was -30% in relation to energy expenditure. Anthropometry, energy expenditure and mitochondrial oxidation were assessed at baseline and at the endpoint of the intervention. Body weight was also measured one year after the treatment. The work was approved by the ethical committees of the University of Navarra (54/2006).
Results:
Volunteers consuming the lower-GI diet showed a significantly higher weight loss than their counterparts (-5.3+/-2.6% vs -7.5+/-2.9%; p=0.032), although the decrease in resting energy expenditure (REE) was similar between groups (p=0.783). Mitochondrial oxidation was significantly affected by the type of diet (p=0.001), being activated after the lower-GI treatment (p=0.022). Interestingly, one year after the nutritional intervention weight regain was only statistically significant in the higher-GI group (p=0.033).
Conclusions:
Lower-GI energy-restricted diets achieved through a specific differential food selection can improve the energy adaptations during obesity treatment, favouring weight loss and probably weight maintenance compared with higher-GI hypocaloric diets.

Related Concept Videos
 01:18
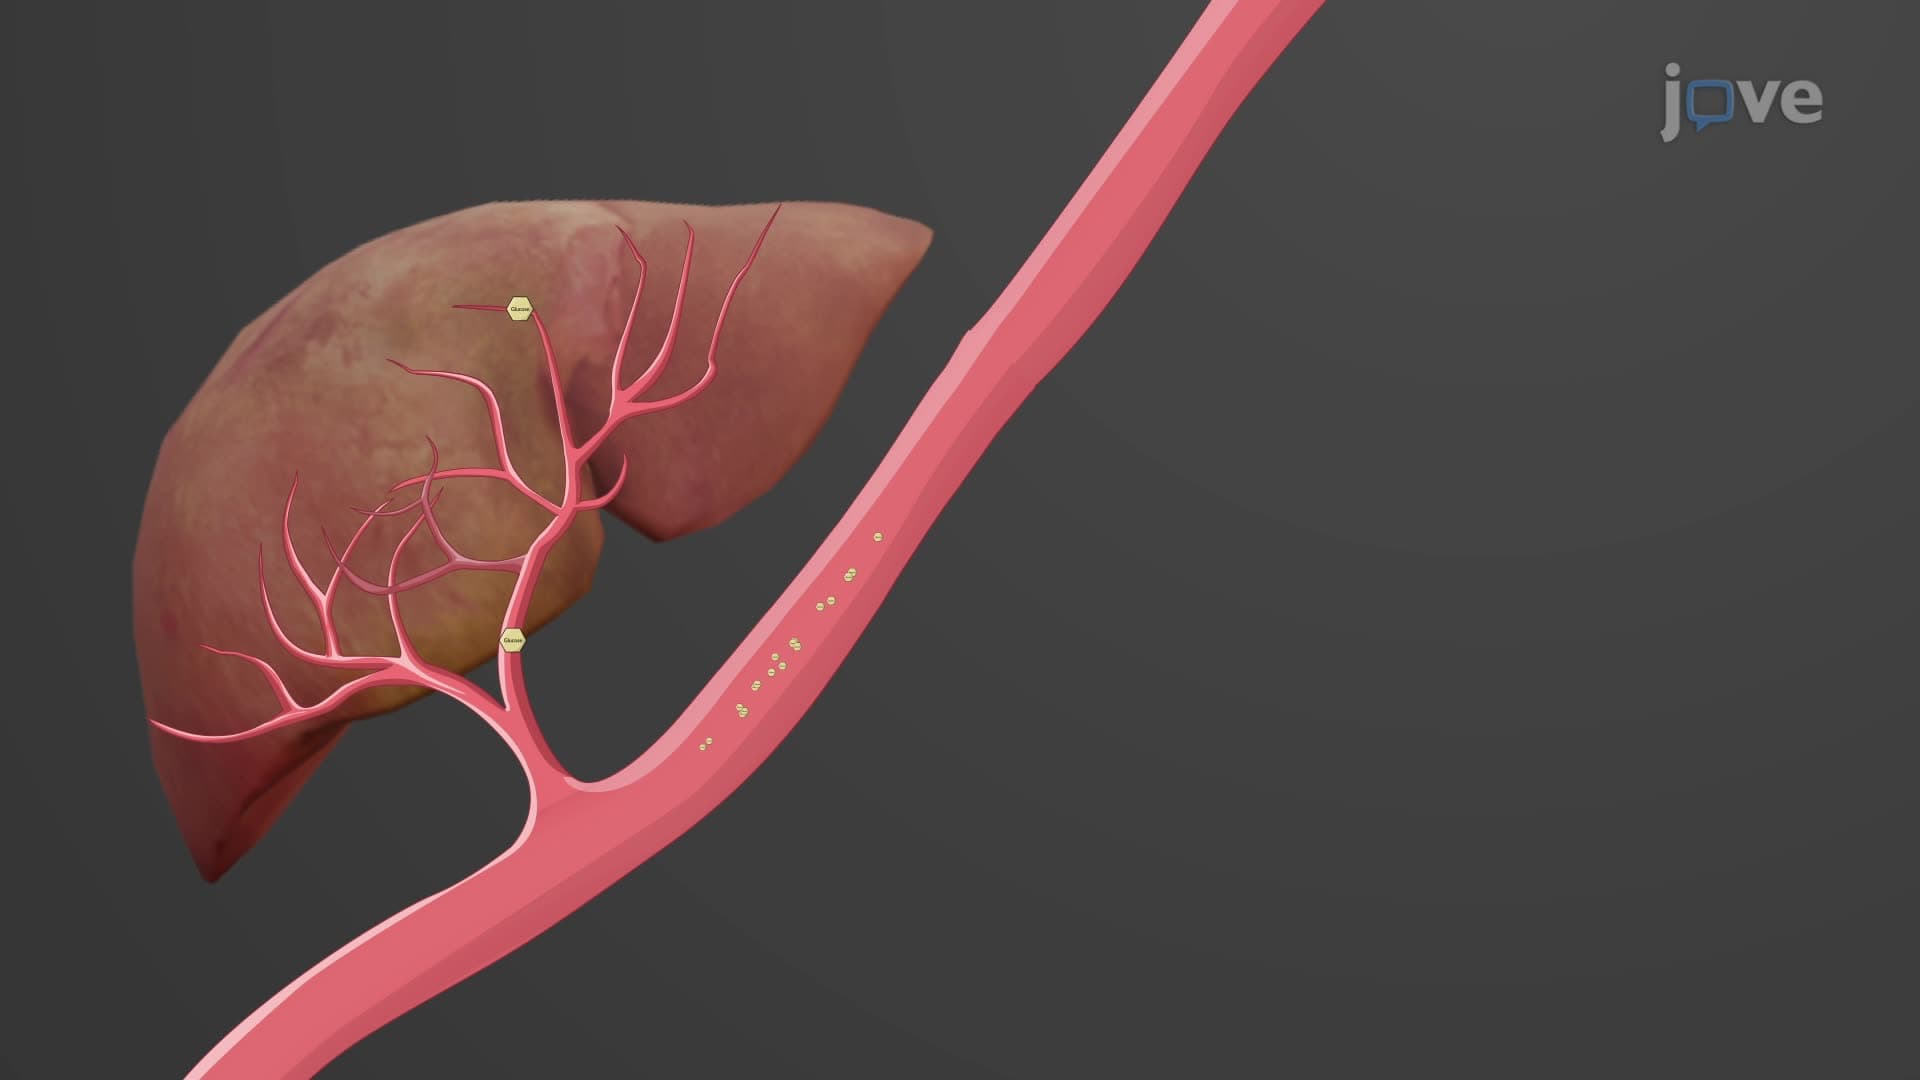
Metabolic States of the Body: The Postabsorptive State
Initially, glycogen stored in the liver is broken down to release glucose into the bloodstream, while glycogen in the muscles is broken down to supply glucose for energy directly within the muscle cells. As glycogen stores diminish,...
 01:24
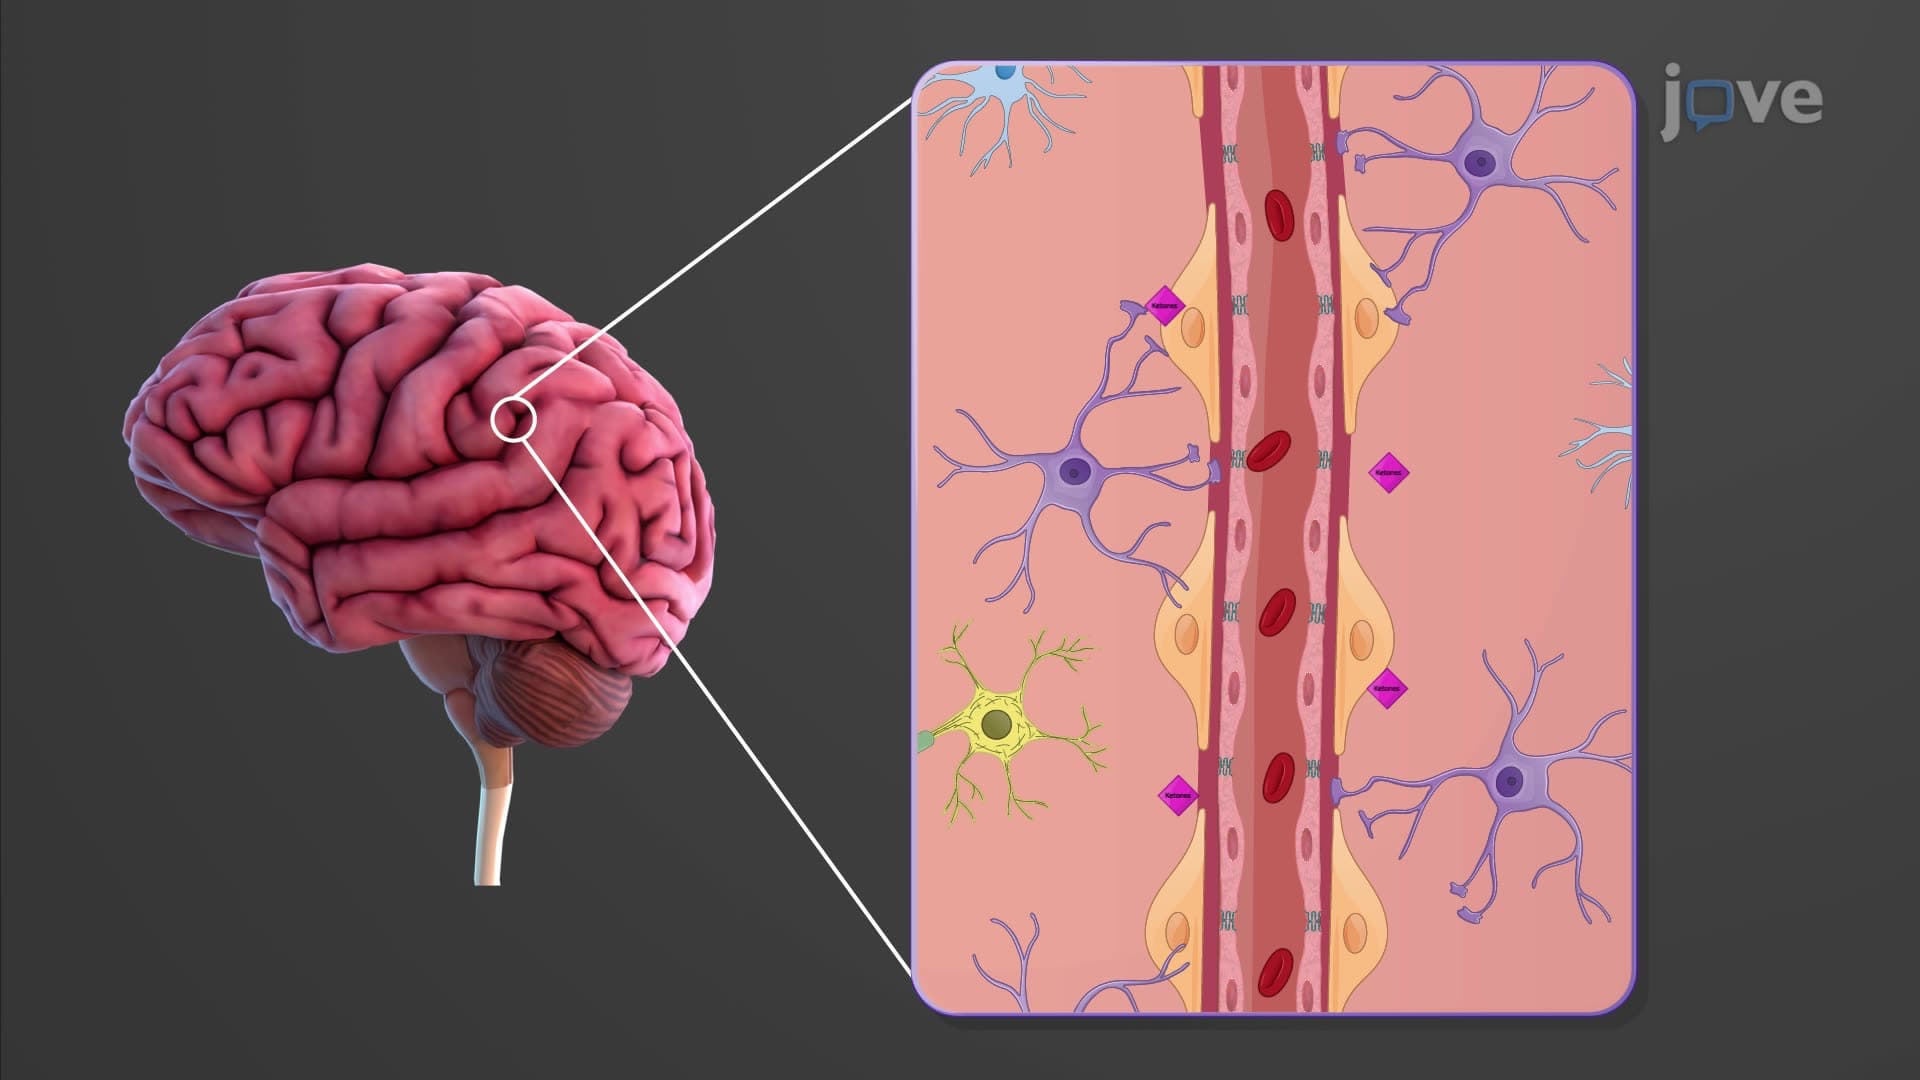
Metabolic States of the Body: Fasting and Starvation
 01:19
Oral Hypoglycemic Agents: α-Glucosidase Inhibitors
Acarbose and miglitol are typically...
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...
 01:15
Hypoglycemia and Glucagon