Microbial contamination in burn patients undergoing urgent intubation as part of their early airway management
Related Experiment Video
Updated: Jul 6, 2026

Preoxygenation Techniques for Tracheal Intubation in Critically Ill Adults Utilizing Oxygen Mask and Noninvasive Ventilation
Published on: December 5, 2025
Michael J Mosier1, Richard L Gamelli, Marcia M Halerz
1Department of Surgery, Loyola University Medical Center, Maywood, IL 60153, USA.

Abstract:
Inhalation injuries occur in approximately one third of all major burns and account for a significant number of deaths in burn patients each year. Previous studies have examined ventilator-associated pneumonia in patients with inhalation injury, but no study to date has evaluated the incidence of bacterial contamination of the airways on admission in patients with inhalation injuries. Because pulmonary complications have been found to cause or directly contribute to mortality in as high as 77% of patients, with combined inhalation injury and thermal injury, early detection of community-acquired pneumonia may significantly alter treatment outcomes. The authors conducted a retrospective review of all burn patients with early intubation and inhalation injury admitted between January 1, 2004 and December 31, 2006 who underwent bronchoscopy with bronchoalveolar lavage (BAL) within 24 hours of admission. Seventy-four consecutive patients fulfilled the inclusion criteria. Age, sex, percentage of total body surface area (%TBSA), presence of alcohol, site of intubation, grade of injury, and BAL results were examined. Analysis revealed a patient population that was 67.6% male, with a 42.0 +/- 17.1-year-old mean age, 27.0 +/- 24.7 %TBSA average burn, 1.6 +/- 1.2 inhalation grade, 17.8 +/- 24.4 ventilator days requirement, 27.3 +/- 31.4 days of length of stay, and 21.6% mortality. BAL results were grouped into four categories: 1) No growth, 2) Normal flora, 3) <100,000 colony-forming units (cfu), and 4) >100,000 cfu. By this criteria, 13 patients (17.6%) had no growth, 22 (29.7%) had normal flora, 27 (36.5%) had <100,000 cfu, and 12 (16.2%) had >100,000 cfu on the initial BAL. Therefore, 53% grew pathogenic organisms and 16% had >100,000 cfu on BAL with initial bronchoscopy. The predominant organisms were gram-positive cocci, with Streptococcus viridans found in 15 patients (20%), Staphylococcus aureus in eight (11%), and Streptococcus pneumonia in four (6%). Analysis of the patients with the highest bacterial loads revealed that they were 75% female and had a trend toward an increased ventilator requirement and longer length of stay. Patients with combined thermal and inhalation injury requiring urgent intubation have a high incidence of bacterial bronchial contamination. Inhalation injury creates a damaged tracheobronchial mucosa and early intubation provides a portal for bacterial contamination. Further studies with a larger patient population and randomization to treatment and nontreatment of the BAL culture results may show statistically significant differences in ventilator days, length of stay, and mortality.
Insights
Inhalation injuries often lead to bacterial contamination in burn patients
Area of Science:
- Medical Research
- Pulmonary Medicine
- Trauma Surgery
Background:
- Inhalation injuries are a significant cause of mortality in burn patients, often leading to pulmonary complications.
- Previous research has focused on ventilator-associated pneumonia, but the incidence of initial airway bacterial contamination in inhalation injury patients remains underexplored.
Purpose of the Study:
- To evaluate the incidence of bacterial contamination in the airways of patients with inhalation injuries upon admission.
- To determine the impact of early bacterial contamination on patient outcomes.
Main Methods:
- Retrospective review of burn patients with inhalation injury requiring early intubation.
- Bronchoscopy with bronchoalveolar lavage (BAL) performed within 24 hours of admission.
- Analysis of patient demographics, burn severity, injury grade, and BAL results (colony-forming units).
Main Results:
- 53% of patients showed pathogenic organisms in their initial BAL, with 16% having over 100,000 colony-forming units (cfu).
- Predominant organisms included Streptococcus viridans, Staphylococcus aureus, and Streptococcus pneumoniae.
- Higher bacterial loads were associated with female patients, increased ventilator days, and longer hospital stays.
Conclusions:
- Patients with combined thermal and inhalation injuries requiring urgent intubation have a high incidence of bacterial bronchial contamination.
- Inhalation injury damages the tracheobronchial mucosa, creating an entry point for bacterial contamination.
- Further research with larger populations and treatment randomization is needed to clarify the impact on patient outcomes.

Related Concept Videos
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
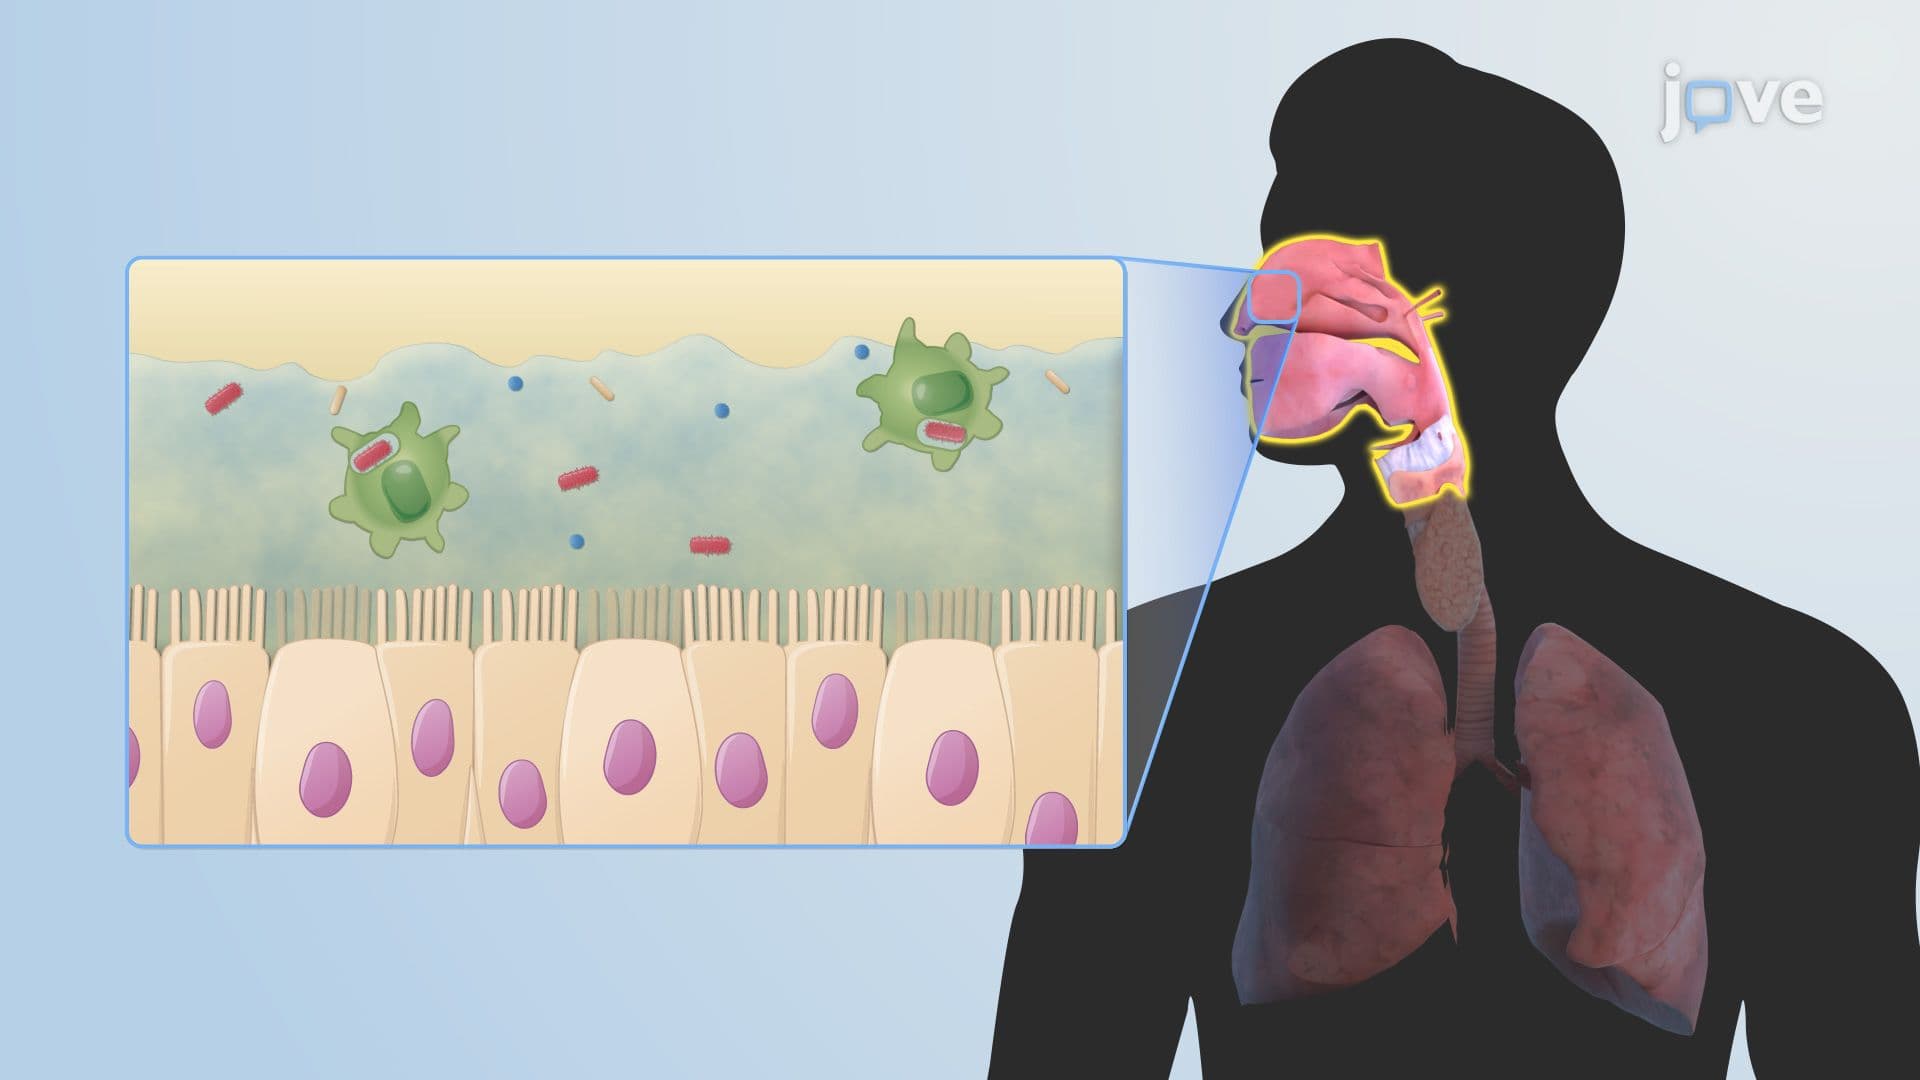 01:29
Microbiota of the Respiratory Tract
 01:16
Tracheostomy Care I: Pre-procedural Steps
Required Equipment
The equipment necessary for tracheostomy care includes: