Related Experiment Video
Updated: Jul 6, 2026

A Thrombotic Stroke Model Based On Transient Cerebral Hypoxia-ischemia
Published on: August 18, 2015
Cognitive outcomes after carotid revascularization: the role of cerebral emboli and hypoperfusion
Zoher Ghogawala1, Michael Westerveld, Sepideh Amin-Hanjani
1Wallace Clinical Trials Center, Greenwich Hospital, Greenwich, Connecticut 06830, USA. zoher.ghogawala@yale.edu

Insights
Cognitive function changes after carotid artery stenting (CAS) and carotid endarterectomy (CEA) need further study. Future trials comparing CAS and CEA should include cognitive assessments to understand impacts on brain health.
Area of Science:
- Neurology
- Vascular Surgery
- Cognitive Science
Background:
- Carotid artery stenting (CAS) and carotid endarterectomy (CEA) are common procedures for carotid stenosis.
- Current trials primarily focus on stroke, myocardial infarction, and mortality, with limited data on cognitive outcomes.
- Emerging evidence suggests potential cognitive decline following CEA.
Purpose of the Study:
- To review the current understanding of cognitive outcomes after carotid revascularization.
- To identify factors influencing cognitive data interpretation in CAS vs. CEA studies.
- To highlight the importance of including cognitive endpoints in future comparative trials.
Main Methods:
- Review of existing literature on cognitive effects of CAS and CEA.
- Analysis of factors contributing to variability in cognitive outcome data.
- Discussion of potential mechanisms affecting cognitive function, including emboli and cerebral hemodynamics.
Main Results:
- Cognitive outcomes after carotid revascularization remain unclear.
- Procedural emboli and changes in cerebral hemodynamics are implicated in cognitive effects.
- CAS may involve a higher burden of microemboli compared to CEA, despite distal protection devices.
- CEA involves temporary vessel occlusion, which may also impact cognitive function.
Conclusions:
- Cognitive outcome assessments are crucial for future randomized trials comparing CAS and CEA.
- Understanding the mechanisms of cognitive impairment is key to potentially mitigating injury.
- Standardized neuropsychological testing and quantification of microemboli are needed for robust comparisons.
Objective:
Carotid artery stenting (CAS) and carotid endarterectomy (CEA) are currently being compared in ongoing randomized, controlled trials using postprocedural 30-day stroke rate, myocardial infarction, and mortality as primary endpoints. Recent data suggest that cognitive function may decline after CEA. Understanding the mechanisms that affect cognitive outcomes after carotid revascularization will be important in the design of future comparative studies of CAS and CEA incorporating cognitive outcome as an endpoint.
Summary Of Review:
The effects of carotid revascularization procedures on cognitive outcome are unclear. Several factors contribute to the difficulty in interpreting cognitive data, including patient heterogeneity, variability of surgical techniques, and the differences in neuropsychological testing methodology. Mechanisms underlying cognitive effects during CEA have emerged, including the potential detrimental effect of procedural emboli and the beneficial effect of improved cerebral hemodynamics. The emergence of CAS as an alternative to CEA for treating carotid stenosis again raises questions about cognitive outcomes. Despite the use of distal protection devices, CAS is associated with a higher burden of microemboli. CAS does not, however, require the extent of temporary vessel occlusion associated with CEA. Quantifying microemboli and changes in cerebral hemodynamics along with standardization of neuropsychological testing may lead to meaningful comparisons of cognitive data for patients undergoing carotid revascularization procedures.
Conclusion:
As use of CAS increases, it is important for randomized, controlled trials comparing CAS with CEA to include cognitive outcomes assessments. Furthermore, understanding the key mechanisms resulting in cognitive impairment during carotid revascularization procedures might limit injury.

Related Concept Videos
 01:15
Ischemic Stroke ll: Pathophysiology
 01:15
Ischemic Stroke l: Introduction
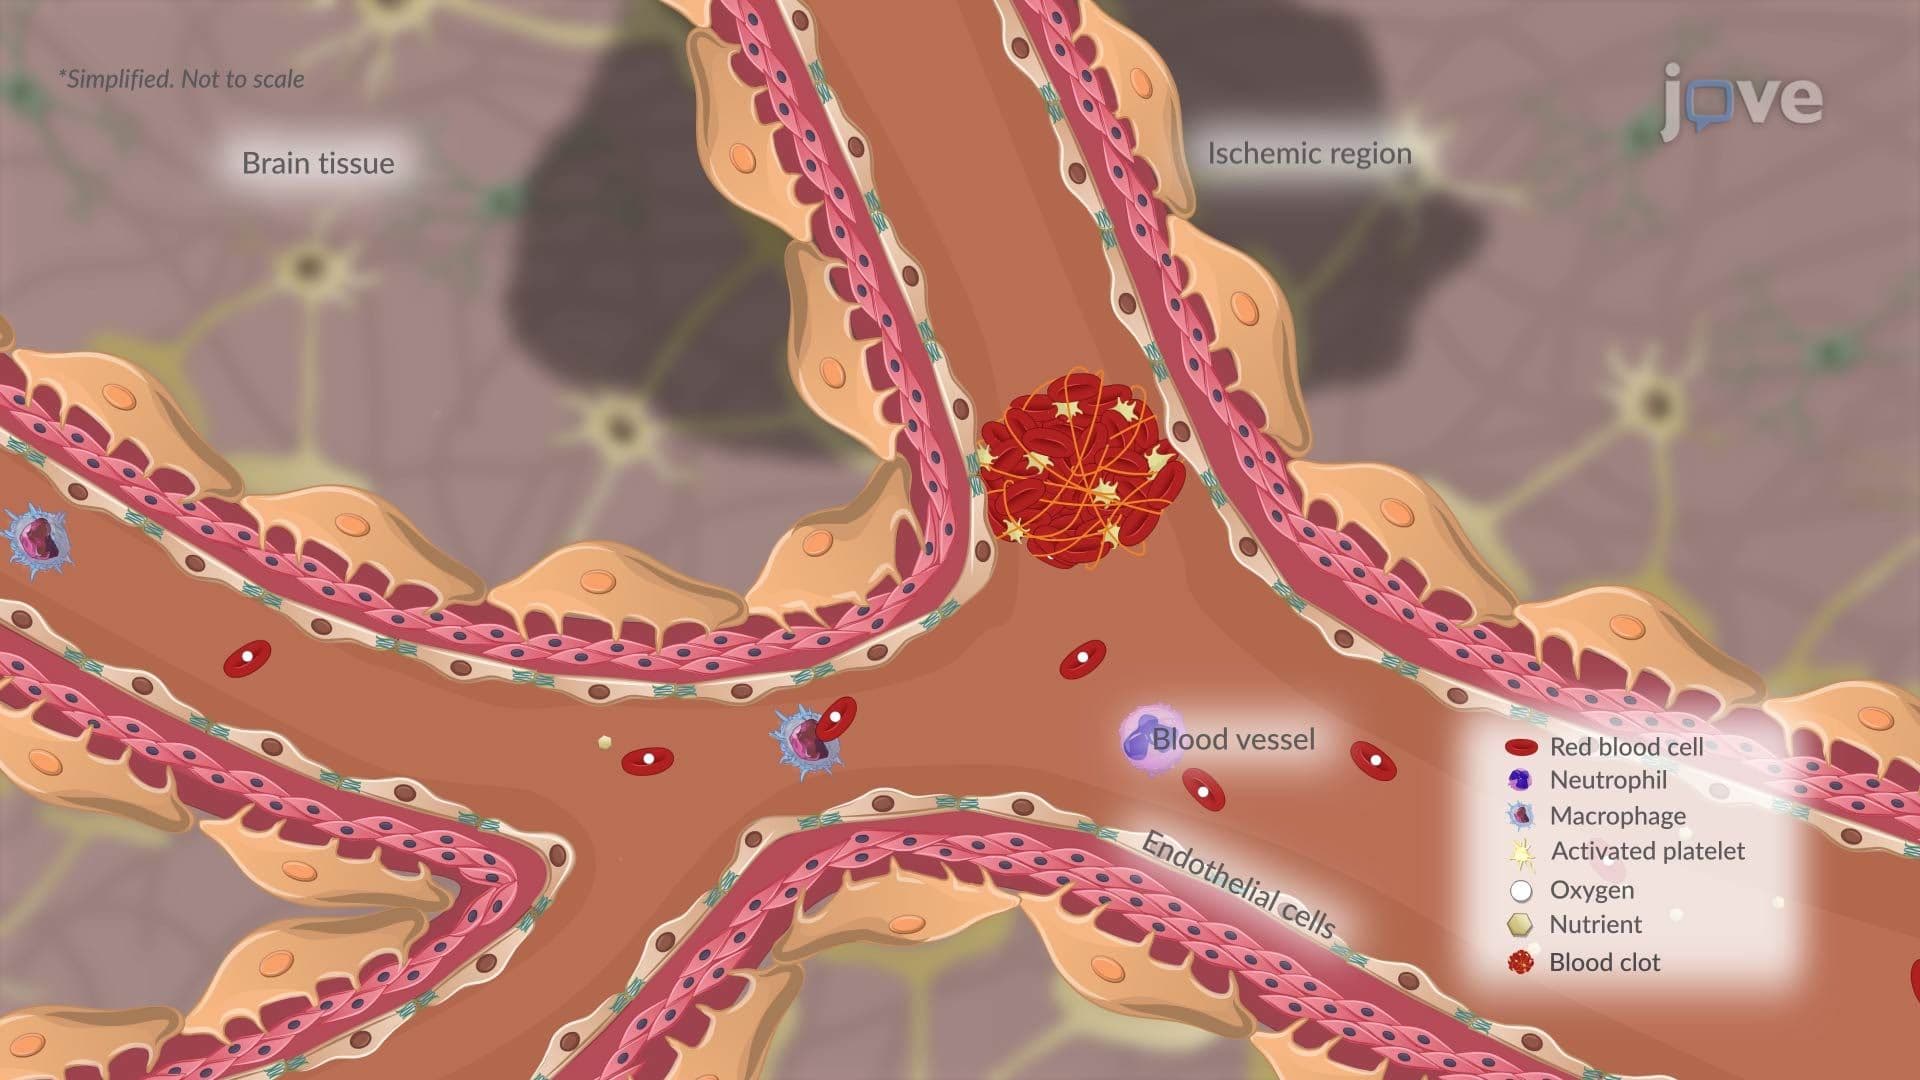 01:26
Transient Ischemic Attack l: Introduction