Related Experiment Video
Updated: Jul 6, 2026

Continuous Manual Exchange Transfusion for Patients with Sickle Cell Disease: An Efficient Method to Avoid Iron Overload
Published on: March 14, 2017
Switch of ESA therapy from darbepoetin-alpha to epoetin-beta in hemodialysis patients: a single-center experience
P Biggar1, M Ketteler, H Hennemann
1Klinikum Coburg, Coburg, Germany. patrick.biggar@kfh-dialysis.de

Aims:
No study has previously investigated a switch from darbepoetin-alpha to epoetin-beta in unselected dialysis patients. Our study determined the intravenous epoetin-beta dose necessary to maintain or to achieve hemoglobin targets after switching from darbepoetin-alpha.
Methods:
In our dialysis center, all eligible dialysis patients (n = 90) were switched from darbepoetin-alpha i.v. to epoetin-beta i.v. in 2005. The epoetin-beta dose was calculated according to the recommended European equimolar conversion factor (1 : 200 microg darbepoetin-alpha corresponds to 200 IU epoetin-beta. The intraindividual evaluation compared 12 weeks before with 16 weeks after the switch. The dose of the erythropoiesis-stimulating agents (ESA) and the hemoglobin levels were analyzed for the whole period and for the last 4 weeks of both treatment periods.
Results:
During treatment with darbepoetin-alpha, 71% of a total of 90 patients achieved a hemoglobin level > or = 11.0 g/dl. After switching to epoetin-beta, the mean hemoglobin level decreased significantly from 11.4 A+/- 1.0 g/dl to 11.1 A+/- 0.9 g/dl (p = 0.0016) and the percentage of patients with hemoglobin levels > or = 11.0 g/dl fell to 50% (p = 0.00138). Furthermore, the mean required ESA dose increased by 13% from 4,335 A+/- 3,217 IU/week darbepoetin-alpha to 4,885 A+/- 3,077 IU/week epoetin-beta (p = 0.0001). Comparing the last 4 weeks, the ESA dose increased by 17% from 4,583 A+/- 3,391 IU/week darbepoetin-alpha to 5,372 A+/- 3,672 IU/week epoetin-beta (p = 0.0003).
Conclusions:
After switching from darbepoetin-alpha i.v. to epoetin-beta i.v., the equimolar epoetin-beta dose was not sufficient to maintain hemoglobin levels with the same efficacy above 11.0 g/dl. Significantly less patients achieved hemoglobin target values as suggested by the EBPG guidelines.
Related Concept Videos
 01:24
Hemodialysis II: Procedure and Complications
 01:25
Hemodialysis I: Introduction
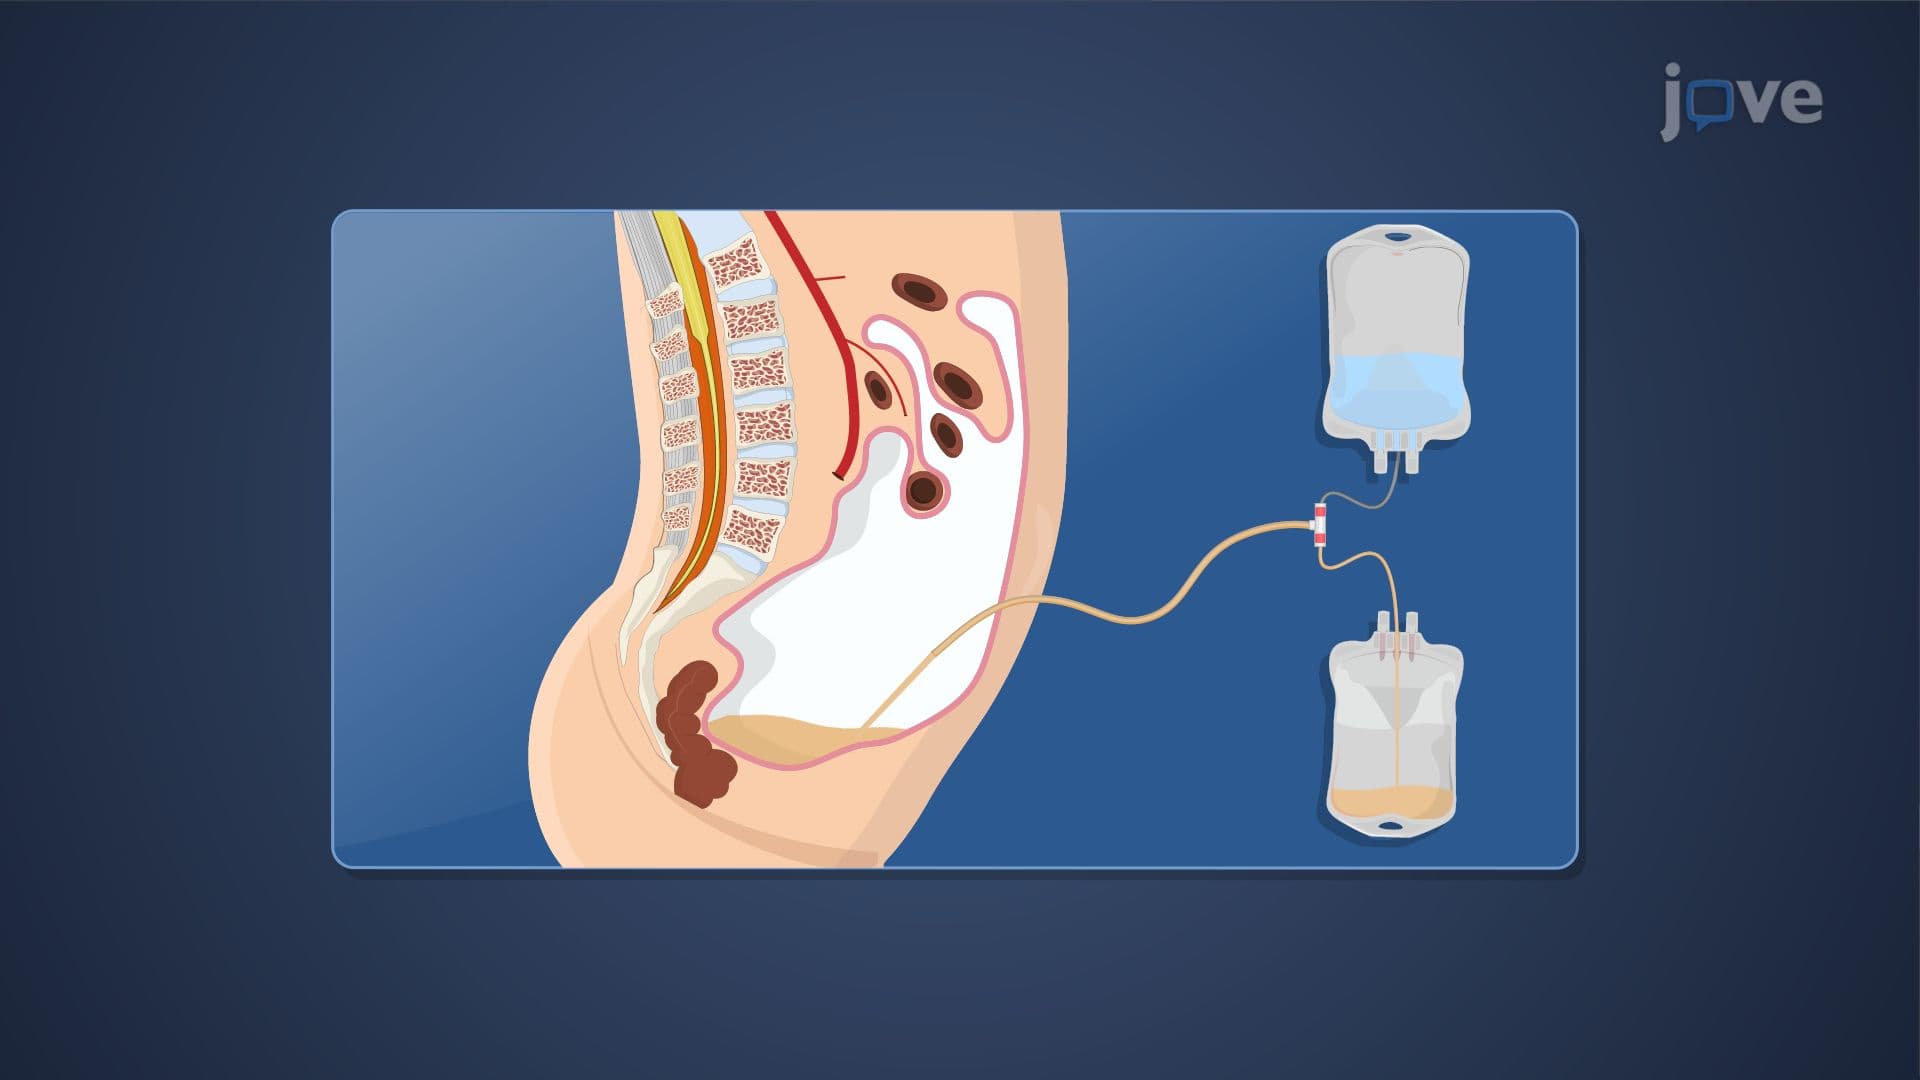 01:30
Extracorporeal Removal of Drugs: Peritoneal Dialysis and Hemodialysis
 01:25
Hemodialysis III: Nursing Management
 01:15
Dialysis
 01:27
Dialysis
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...