Related Experiment Video
Updated: Jul 6, 2026
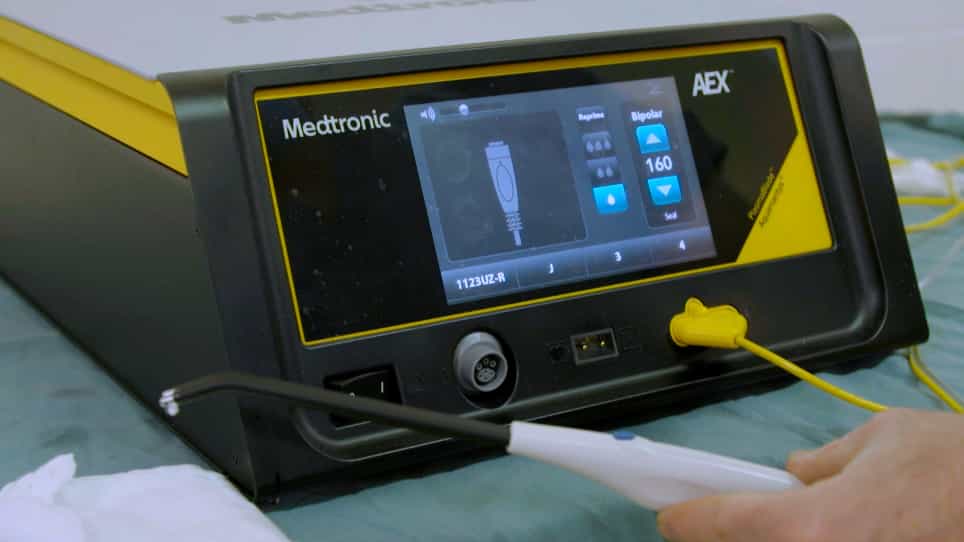

A Saline/Bipolar Radiofrequency Energy Device As an Adjunct for Hemostasis in Solid Organ Injury/Trauma
Published on: July 28, 2020
Nonoperative treatment of multiple intra-abdominal solid organ injury after blunt abdominal trauma
Hakan Yanar1, Cemalettin Ertekin, Korhan Taviloglu
1Istanbul University Istanbul Faculty of Medicine, Istanbul, Turkey.

Background:
A number of large series' have attempted to examine the management of blunt solid organ injuries; however, only a few studies regarding multiple injuries exist. The aim of this study is to analyze whether multiple solid organ injury affects nonoperative management (NOM) and to look for predictive factors of NOM.
Methods:
All patients admitted with a diagnosis of blunt solid organ injury between January 1, 1999 and January 1, 2005 were included in this prospective observational study. Of the 468 patients who had solid organ injury, 46 patients met the inclusion criteria of multiple solid organ injuries. Presentation, mechanism of injury, injury grade, Abbreviated Injury Scale score, management, and outcomes were analyzed. Independent predictive factors of NOM failure were identified. Patients managed nonoperatively were compared with patients who had had emergent laparotomy and patients for whom NOM failed.
Results:
Fifteen patients (33%) underwent emergency laparotomy because of hypovolemic shock that was unresponsive to aggressive resuscitation, and 31 (66%) were selected for NOM. Among the 31 patients, NOM was successful in 23 (75%). No specific organ injury combination was found to affect NOM failure. Admission lactate level [odds ratio(OR), 1.44; 95% confidence interval (CI), 1.05-1.98; p = 0.025], a drop in the hematocrit greater than 20% in the first hour after admission (OR, 1.13; 95% confidence interval CI, 1.04-1.24; p = 0.007), and solid viscus score (OR, 1.67; 95% CI, 1.03-2.80; p = 0.04) were significant independent risk factors in those patients for whom NOM failed. In logistic regression analysis, hypotension at admission (OR, 0.96; 95% CI, 0.92-0.99; p = 0.014) and transfusion in the first 6 hours after admission (OR, 1.03; 95% CI, 1.00-1.05; p = 0.015) were found to significantly affect the success rate of nonoperative management.
Conclusion:
Lactate levels at admission, solid viscus score, necessity of transfusion, crystalloid resuscitation, and a drop in the hematocrit in the first hour after admission are useful parameters for judging the failure of NOM. Although there is a higher failure rate of NOM in multiple solid organ injury, NOM can still be considered in these cases with extra caution.
More Related Videos
 07:48
Intraoperative Video Consultation Following Bile Duct Transection Facilitates Direct OR Transfer for Robotic Hepaticojejunostomy at Tertiary Center
Published on: January 9, 2026
 20:33
A Case Series of Successful Abdominal Closure Utilizing a Novel Technique Combining a Mechanical Closure System with a Biologic Xenograft that Accelerates Wound Healing
Published on: July 4, 2019
Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:26
Kidney Transplant II: Surgical Procedure
 01:26
Aneurysm III: Interprofessional Care
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations: