Related Experiment Video
Updated: Jul 5, 2026


Disruption of the Mouse Blood-Brain Barrier by Small Extracellular Vesicles from Hypoxic Human Placentas
Published on: January 26, 2024
[Hypoxemia during cesarean section due to massive pleural effusion in a patient with preeclampsia]
Rieko Kinoshita1, Yoshihisa Matsumoto, Keisuke Yamada
1Department of Anesthesiology and Intensive Care Medicine, Graduate School of Medical Science, Kanazawa University, Kanazawa 920-8641.

We report hypoxemia during cesarean section in a 33-year-old woman with preeclampsia. She developed generalized body weight increase, severe proteinuria and decrease of platelets at week 33 of gestation. Cesarean section was scheduled under general anesthesia. The patient did not complain of dyspnea preoperatively. After induction of general anesthesia, arterial oxygen saturation decreased from 99 to 88%. Massive left pleural effusion was detected and chest drainage was performed, and oxygenation was improved. Accumulation of pleural effusion tends to be over-looked because many parturients with pleural effusion do not complain of dyspnea. Physicians should pay attention to pleural effusion in parturients, especially those with risk factors such as preeclampsia, generalized body weight increase and administration of beta stimulant.
We report hypoxemia during cesarean section in a 33-year-old woman with preeclampsia. She developed generalized body weight increase, severe proteinuria and decrease of platelets at week 33 of gestation. Cesarean section was scheduled under general anesthesia. The patient did not complain of dyspnea preoperatively. After induction of general anesthesia, arterial oxygen saturation decreased from 99 to 88%. Massive left pleural effusion was detected and chest drainage was performed, and oxygenation was improved. Accumulation of pleural effusion tends to be over-looked because many parturients with pleural effusion do not complain of dyspnea. Physicians should pay attention to pleural effusion in parturients, especially those with risk factors such as preeclampsia, generalized body weight increase and administration of beta stimulant.
More Related Videos
 11:27
A Modified Sonographic Algorithm for Image Acquisition in Life-Threatening Emergencies in the Critically Ill Newborn
Published on: April 7, 2023
 07:36
Modeling Encephalopathy of Prematurity Using Prenatal Hypoxia-ischemia with Intra-amniotic Lipopolysaccharide in Rats
Published on: November 20, 2015
Related Concept Videos
 01:21
Acute Respiratory Failure-II
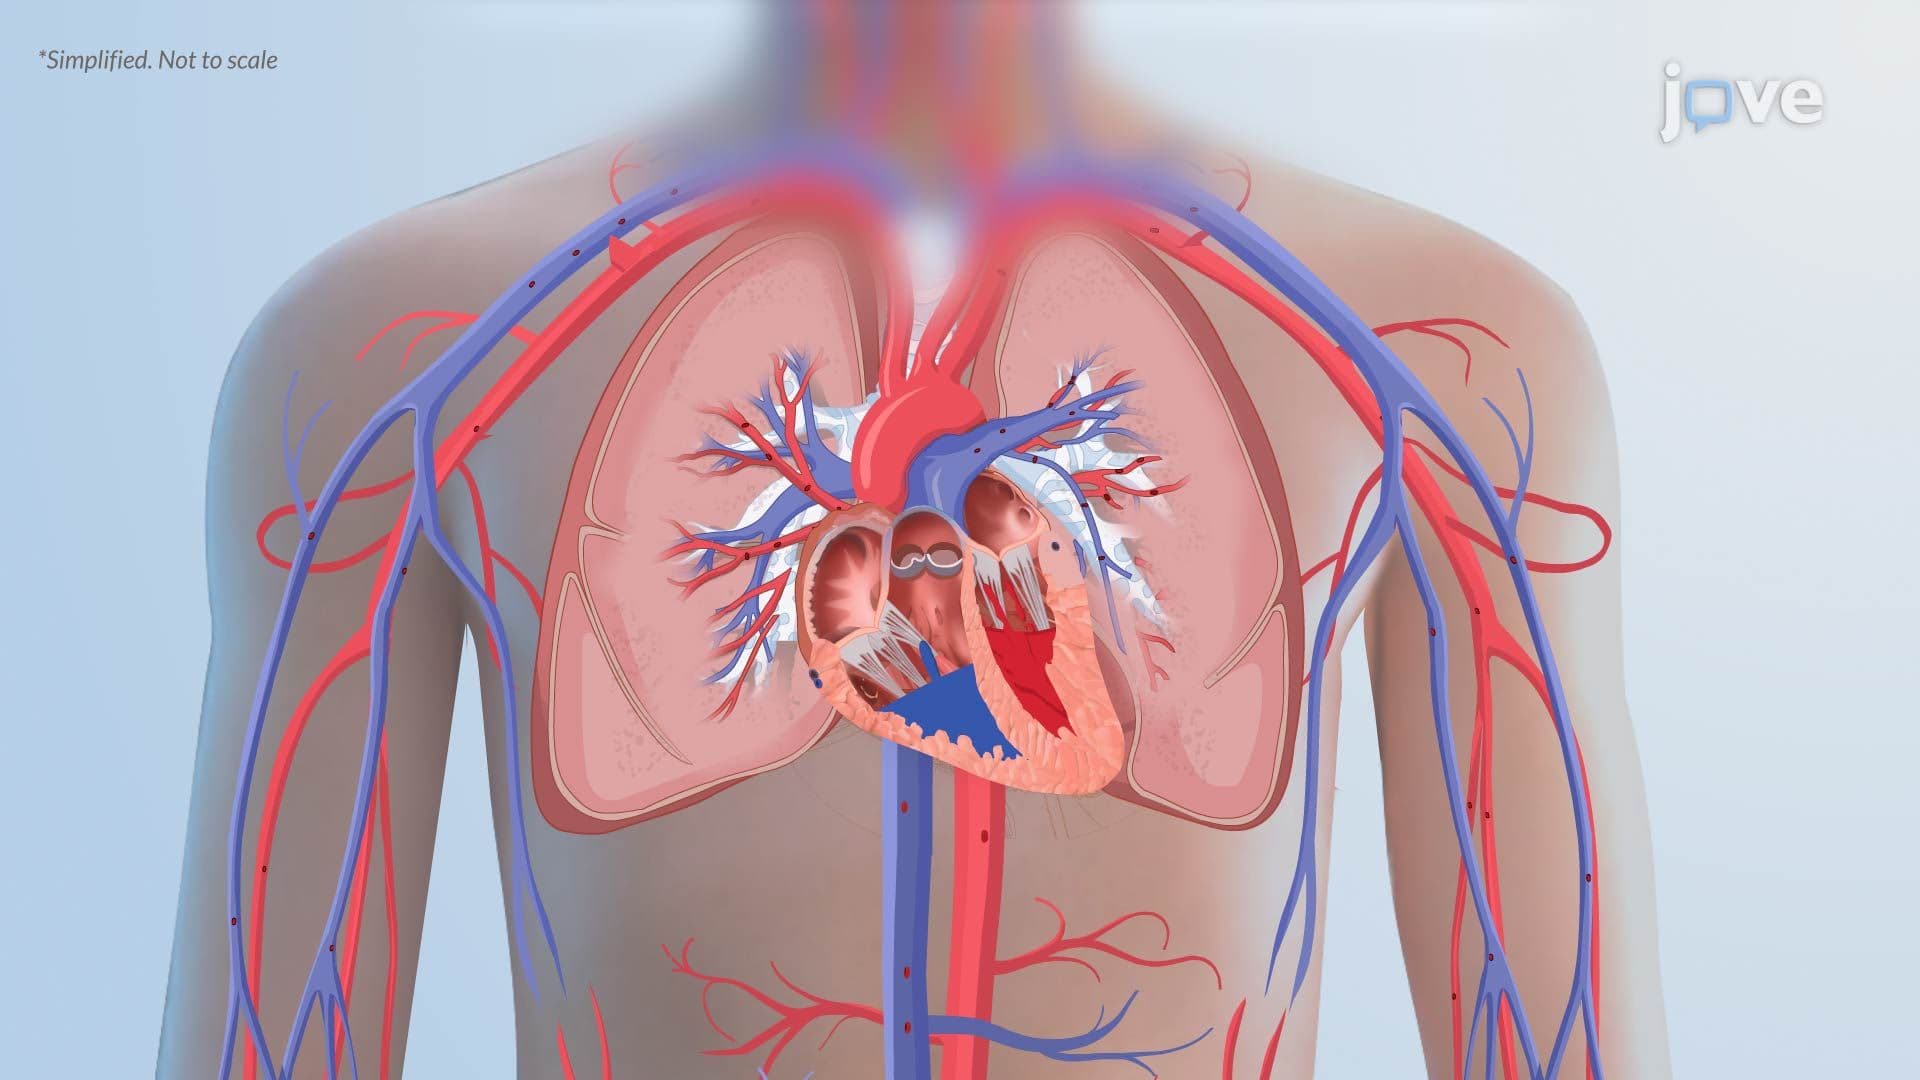
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:18
Pulmonary Edema II: Pathophysiology
 01:10
Atelectasis II: Pathophysiology
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:27
Pneumothorax-II
Clinical Manifestations: