Related Experiment Video
Updated: Jul 5, 2026

Transcorporal Artificial Urinary Sphincter Cuff Placement in a Case Requiring Revision for Urethral Atrophy
Published on: June 16, 2022
Stress urinary incontinence: relative importance of urethral support and urethral closure pressure
John O L DeLancey1, Elisa R Trowbridge, Janis M Miller
1Department of Obstetrics and Gynecology, Pelvic Floor Research Group, University of Michigan, Ann Arbor, Michigan, USA. DeLancey@umich.edu

Purpose:
Treatment strategies for stress incontinence are based on the concept that urethral mobility is the predominant causal factor with sphincter function a secondary contributor. To our knowledge the relative importance of these 2 factors has not been assessed in properly controlled studies.
Materials And Methods:
The Research on Stress Incontinence Etiology project is a case-control study that compared 103 women with stress incontinence and 108 asymptomatic controls in groups matched for age, race, parity and hysterectomy. Urethral closure pressure, urethral and pelvic organ support, levator ani muscle function and intravesical pressure were measured and analyzed using logistic regression and multivariable modeling.
Results:
Mean +/- SD maximal urethral closure pressure was 42% lower in cases (40.8 +/- 17.1 vs 70.2 +/- 22.4 cm H(2)O, d = 1.47). Lesser effect sizes were seen for support parameters, including resting urethral axis and urethrovaginal support (d = 0.41 and 0.50, respectively). Other pelvic floor parameters, including genital hiatus size and urethral axis during muscle contraction (d = 0.60 and 0.58, respectively), differed but levator strength and levator defect status did not. Maximum cough pressure, which is an assessment of stress on the continence mechanism, was also different (d = 0.43). After adjusting for body mass index the maximal urethral closure pressure alone correctly classified 50% of cases. Adding the best predictors for urethrovaginal support and cough strength to the model added 11% of predictive ability.
Conclusions:
The finding that maximal urethral closure pressure and not urethral support is the factor most strongly associated with stress incontinence implies that improving urethral function may have therapeutic promise.

Related Concept Videos
 01:19
Anatomy of the Genitourinary System II: Bladder and Urethra
 01:26
The Micturition Reflex
The process begins with bladder filling, where the bladder wall stretches as urine accumulates. This stretching activates the urine storage reflex, mediated by the sacral spinal segments and the pontine storage center. Efferent sympathetic impulses stimulate the detrusor muscle to relax and the internal urethral sphincter to contract, facilitating urine...
 01:23
Urinary Bladder
In males, the bladder is situated in front of the rectum, while in females, it is positioned anterior to the vagina and uterus. The bladder floor contains an inverted triangular area called the trigone, defined by the two ureteric...
 01:16
Urethra
The anatomy of the urethra differs between males and females. In females, the urethra is short, measuring about 3–4 cm in length, and opens anterior to the vaginal opening. In males, the urethra is longer and passes through the penis, serving dual purposes: expelling urine and ejaculating semen. The male urethra is...
 01:19
Urodynamic Studies: Uroflowmetry
 01:26
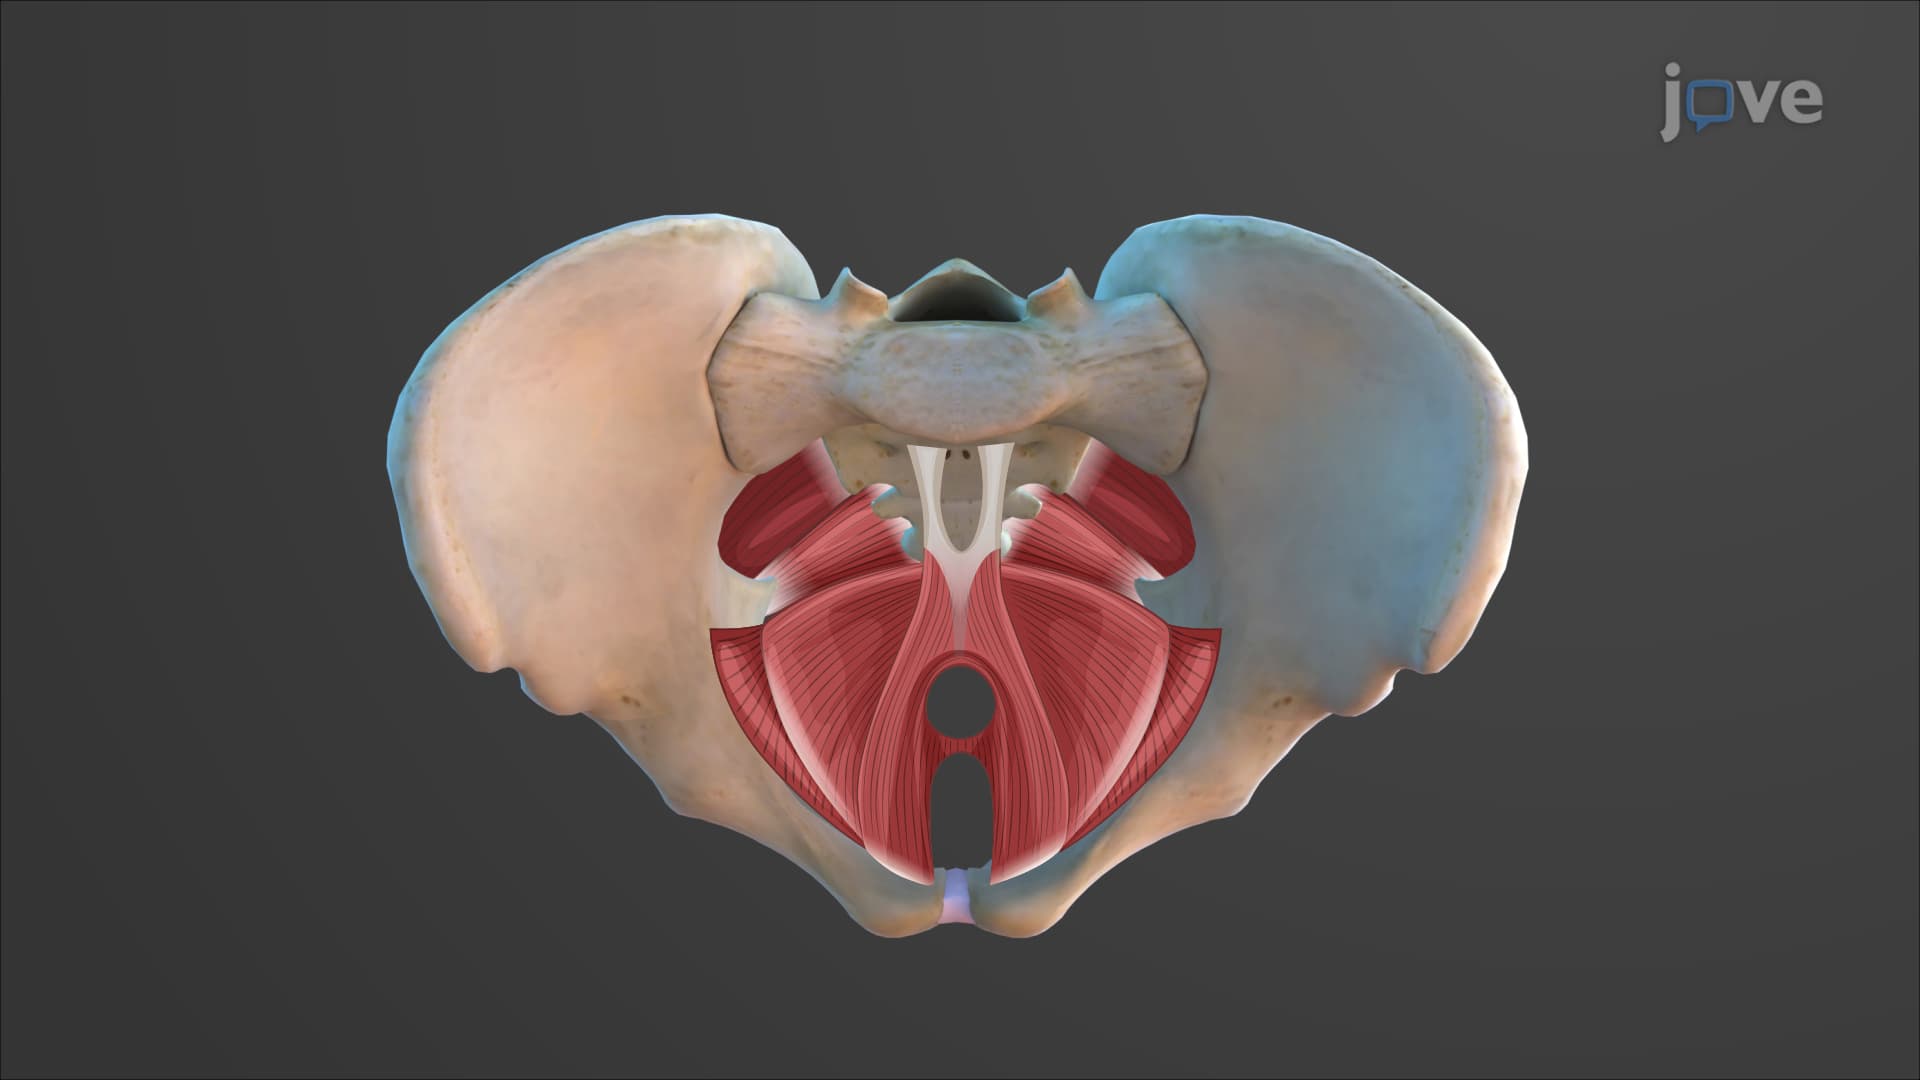
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...