Related Experiment Video
Updated: Jul 5, 2026


An Ex vivo Culture System to Study Thyroid Development
Published on: June 6, 2014
Effect of high versus low initial doses of L-thyroxine for congenital hypothyroidism on thyroid function and somatic
J H Jones1, B Gellén, W F Paterson
1Royal Hospital for Sick Children, Dalnair Street, Glasgow, UK.

Insights
Higher initial thyroxine (T4) doses in congenital hypothyroidism normalize thyroid function faster. This 50 mcg daily dose showed no evidence of sustained somatic overgrowth in infants up to 3 years.
Area of Science:
- Pediatric Endocrinology
- Neonatal Care
- Thyroid Disorders
Background:
- The optimal thyroxine (T4) dosage for congenital hypothyroidism (CH) in infants remains debated.
- Higher T4 doses may improve cognition but risk behavioral issues.
- Somatic growth is examined as a marker for T4 overtreatment.
Purpose of the Study:
- To evaluate the effect of initial thyroxine (T4) dosage on somatic growth in infants with congenital hypothyroidism (CH).
- To determine if higher T4 doses lead to overtreatment, indicated by accelerated growth.
Main Methods:
- 314 infants with CH were divided into three groups based on initial daily T4 dose (25, 30-40, or 50 mcg).
- Thyroid function, weight, length, and head circumference were monitored up to 36 months.
- Linear growth standard deviation scores (SDS) were compared using regression analysis.
Main Results:
- The 50 mcg T4 group normalized thyroid-stimulating hormone (TSH) significantly faster than lower-dose groups.
- No significant differences in linear growth rate were observed between groups at 12 or 18 months.
- All infants showed relatively large occipito-frontal head circumference (OFC) SDS.
Conclusions:
- An initial T4 dose of 50 mcg daily normalizes thyroid function earlier in CH infants.
- This higher dose does not result in sustained somatic overgrowth between 3 months and 3 years.
- The findings suggest 50 mcg/day is a safe and effective initial dose for CH.
Background And Aims:
The optimal dose of thyroxine (T4) in congenital hypothyroidism (CH) during infancy is controversial. Higher doses lead to improvement in cognitive scores, but have been linked to later behavioural difficulties. We have examined the effects of initial T4 dosage on somatic growth--a putative surrogate marker of overtreatment.
Methods:
314 CH children (214 girls, 100 boys) were analysed according to initial daily dose of T4: Group 1 (25 mug, n = 152), Group 2 (30-40 mug, n = 63) and Group 3 (50 mug, n = 99). Thyroid function and weight, length and occipito-frontal head circumference (OFC) standard deviation score (SDS) were compared at 3, 6, 12, 18, 24 and 36 months of age. Linear growth SDS was compared between the three groups using a regression adjustment model at 12 and 18 months of age using birth weight and 3-month data as baselines. Thyroid function was also compared at diagnosis (T 0), and 7-21 days after the start of treatment (T1).
Results:
At T1 median thyroid stimulating hormone (TSH) for Groups 1, 2 and 3 was 58, 29 and 4.1 mU/l, respectively (p<0.001), Group 3 values remaining significantly lower at 3 and 6 months. Median free T4 (fT4) was within or just above the reference range in all groups at T1, but 7.4% of Group 1 had values <9 pmol/l compared with 5.1% and 0% for Groups 2 and 3, respectively. At 3 months weight, length and OFC SDS values were -0.39, -0.35, 0.09; -0.30, -0.47, 0.32; and -0.03, -0.13, 0.18 for Groups 1, 2 and 3, respectively, indicating relatively large OFC in all infants. A regression adjustment model showed no significant difference in growth rate from baseline and 12 or 18 months of age, between the three groups.
Conclusion:
An initial T4 dose of 50 mug daily, normalises thyroid function several months earlier than lower-dose regimes, with no evidence of sustained somatic overgrowth between 3 months and 3 years.
Related Concept Videos
 01:18
Functions of Thyroid Hormones
TH is indispensable for the normal development and maturation of the skeletal, muscular, and nervous systems during fetal and childhood growth. It facilitates bone mineral turnover and regulates protein synthesis in developing tissues, contributing significantly to overall growth and...
 01:20
Synthesis and Regulation of Thyroid Hormones
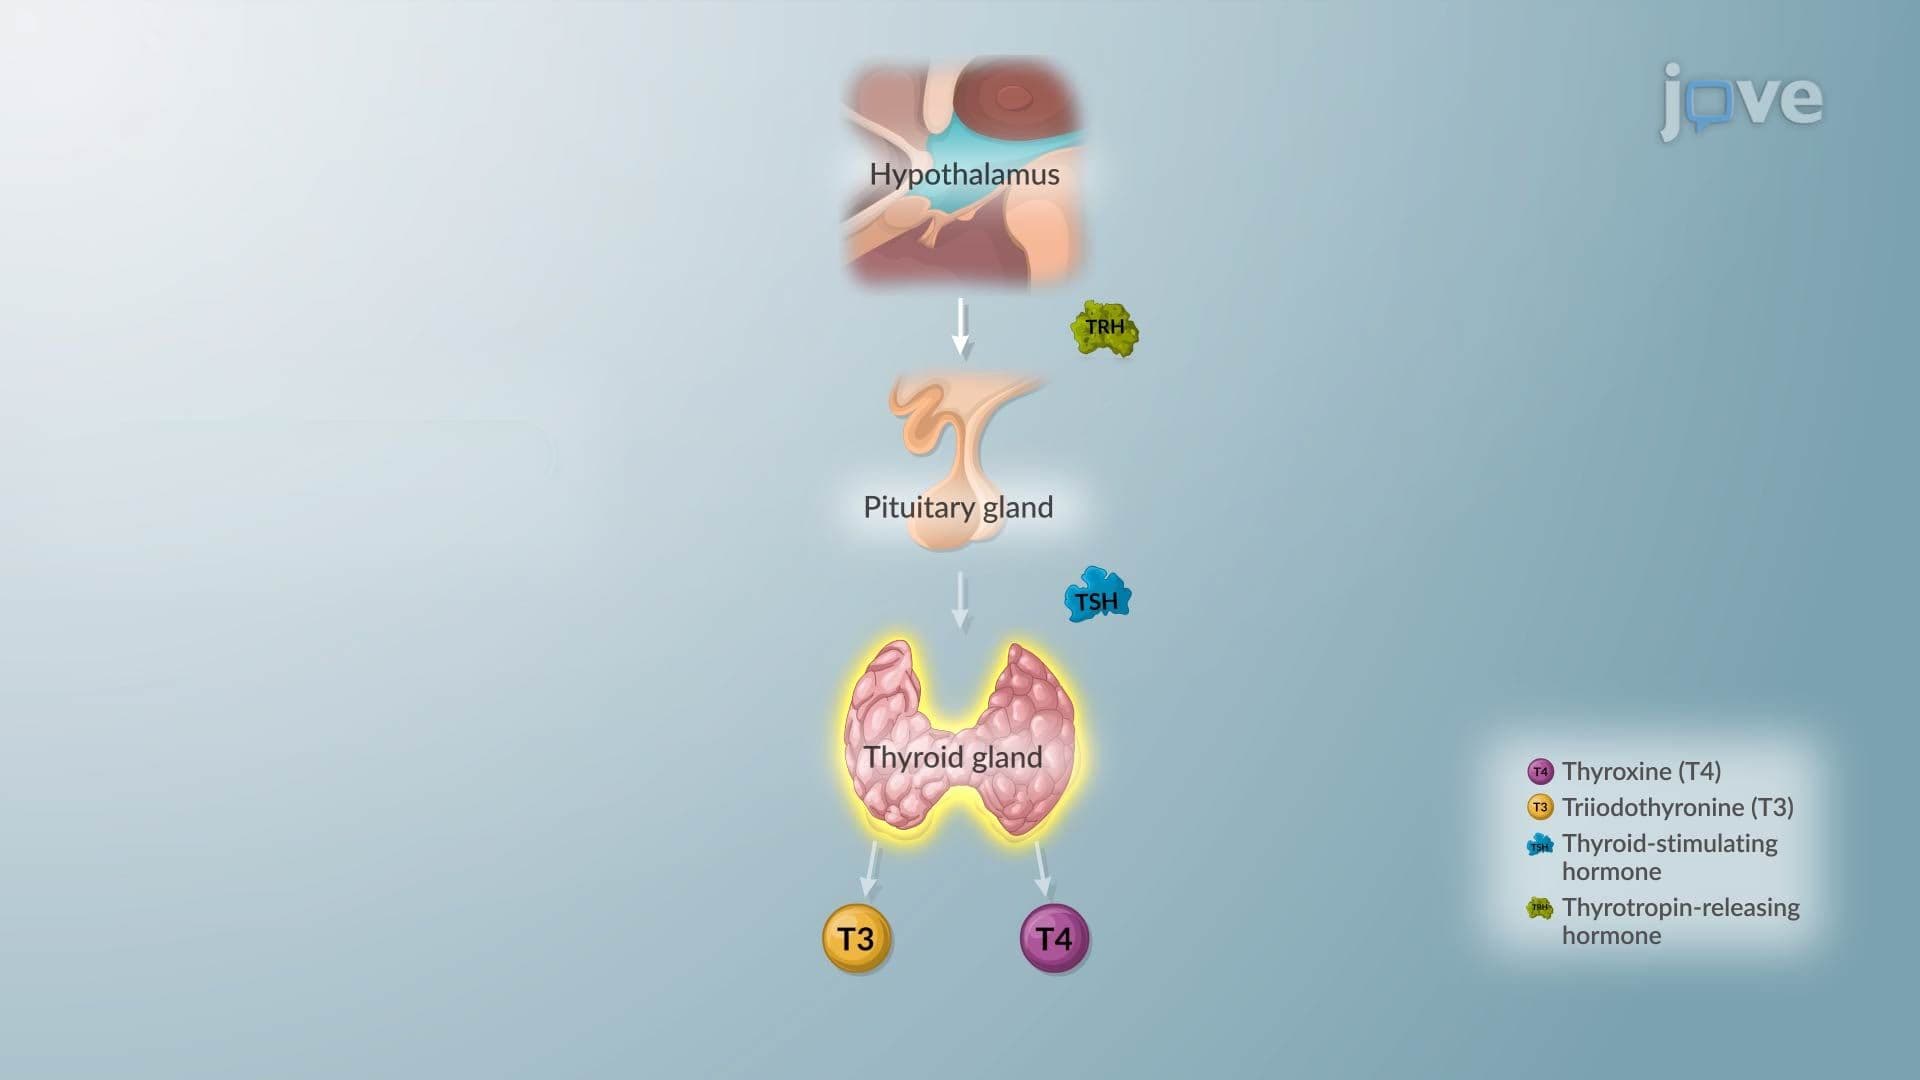
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The iodine is then...
 01:23
Hypothyroidism II: Pathophysiology
 01:27
Goiter
 01:25
Hyperthyroidism I: Introduction
 01:27
Hyperthyroidism II: Pathophysiology