Related Experiment Video
Updated: Jul 5, 2026
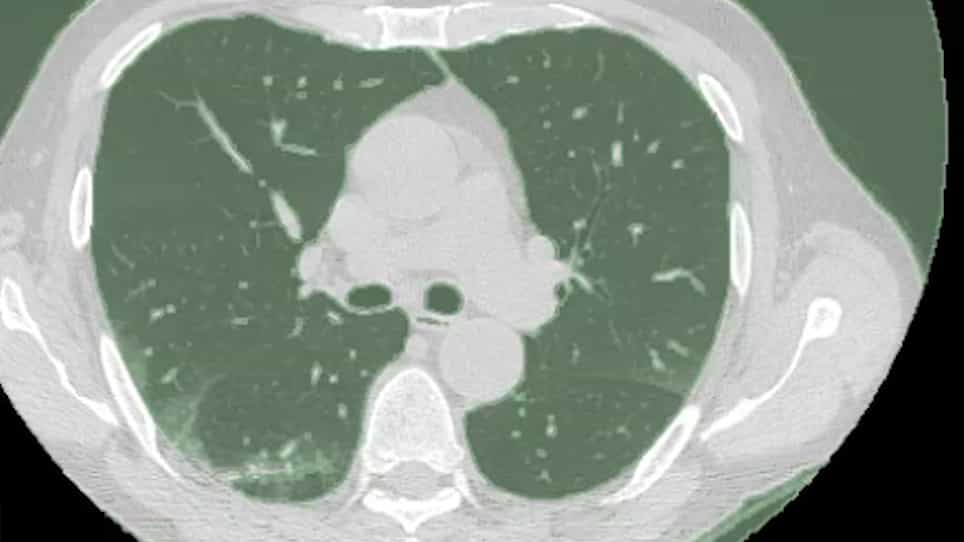

Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Severe acute respiratory syndrome: clinical and laboratory manifestations
Christopher W K Lam1, Michael H M Chan, Chun K Wong
1Department of Chemical Pathology, The Chinese University of Hong Kong, Prince of Wales Hospital, Shatin, Hong Kong. waikeilam@cuhk.edu.hk

Abstract:
Severe acute respiratory syndrome (SARS) is a recently emerged infectious disease with significant morbidity and mortality. An epidemic in 2003 affected 8,098 patients in 29 countries with 774 deaths. The aetiological agent is a new coronavirus spread by droplet transmission. Clinical and general laboratory manifestations included fever, chills, rigor, myalgia, malaise, diarrhoea, cough, dyspnoea, pneumonia, lymphopenia, neutrophilia, thrombocytopenia, and elevated serum lactate dehydrogenase (LD), alanine aminotransferase (ALT) and creatine kinase (CK) activities. Treatment has been empirical; initial potent antibiotic cover, followed by simultaneous ribavirin and corticosteroids, with or without pulse high-dose methylprednisolone, have been used. The postulated disease progression comprises (1) active viral infection, (2) hyperactive immune response, and (3) recovery or pulmonary destruction and death. We investigated serum LD isoenzymes and blood lymphocyte subsets of SARS patients, and found LD1 activity as the best biochemical prognostic indicator for death, while CD3+, CD4+, CD8+ and natural killer cell counts were promising predictors for intensive care unit (ICU) admission. Plasma cytokine and chemokine profiles showed markedly elevated Th1 cytokine interferon (IFN)-gamma, inflammatory cytokines interleukin (IL)-1beta, IL-6 and IL-12, neutrophil chemokine IL-8, monocyte chemoattractant protein-1 (MCP-1), and Th1 chemokine IFN-gamma-inducible protein-10 (IP-10) for at least two weeks after disease onset, but there was no significant elevation of inflammatory cytokine tumor necrosis factor (TNF)-alpha and anti-inflammatory cytokine IL-10. Corticosteroid reduced IL-8, MCP-1 and IP-10 concentrations from 5-8 days after treatment. Measurement of biochemical markers of bone metabolism demonstrated significant but transient increase in bone resorption from Day 28-44 after onset of fever, when pulse steroid was most frequently given. With tapering down of steroid therapy, there was a decrease in bone resorption marker together with an increase in bone formation markers round Day 50, suggesting that some of the bone loss might be reversed. Our research studies on the chemical pathology and clinical immunology of SARS should have implications for the pathophysiology and therapy of this potentially lethal infection.

Related Concept Videos
 01:29
Coronavirus
 01:23
Acute Respiratory Failure-IV
 01:29
Respiratory Syncytial Virus Disease
 01:13
Asthma III: Clinical Manifestations
 01:19
Chronic Obstructive Pulmonary Disease IV: Clinical Manifestations
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...