Related Experiment Video
Updated: Jul 5, 2026

Multiplexed Fluorometric ImmunoAssay Testing Methodology and Troubleshooting
Published on: December 12, 2011
Interferences in immunoassay
1Department of Chemical Pathology, Queensland Health Pathology Service, Princess Alexandra Hospital, Woolloongabba, Queensland, Australia. jill_tate@health.qld.gov.au

Substances that alter the measurable concentration of the analyte or alter antibody binding can potentially result in immunoassay interference. Interfering, endogenous substances that are natural, polyreactive antibodies or autoantibodies (heterophiles), or human anti-animal antibodies together with other unsuspected binding proteins that are unique to the individual, can interfere with the reaction between analyte and reagent antibodies in immunoassay. Lipaemia, cross-reactivity, and exogenous interferences due to pre-analytical variation, matrix and equipment reaction also affect immunoassay. Interfering substances may lead to falsely elevated or falsely low analyte concentration in one or more assay systems depending on the site of the interference in the reaction and possibly result in discordant results for other analytes. The prevalence of interference is generally low in assays containing blocking agents that neutralise or inhibit the interference but is often higher in new, untested immunoassays. A wide range of analytes measured by immunoassay including hormones, tumour markers, drugs, cardiac troponin and microbial serology may be affected. Interference in immunoassay may lead to the misinterpretation of a patient's results by the laboratory and the wrong course of treatment being given by the physician. Laboratories should put processes in place to detect, test and report suspected interferences. It is equally important that physicians communicate any clinical suspicion of discordance between the clinical and the laboratory data to the laboratory. The detection of interference may require the use of an alternate assay or additional measurements, before and after treatment with additional blocking reagent, or following dilution of the sample in non-immune serum. It is imperative that laboratories inform physicians of the follow-up procedure and report on the presence of any interference. The establishment of on-going laboratory-physician contact is essential to the continuing awareness of wrong patient results due to interference.
Substances that alter the measurable concentration of the analyte or alter antibody binding can potentially result in immunoassay interference. Interfering, endogenous substances that are natural, polyreactive antibodies or autoantibodies (heterophiles), or human anti-animal antibodies together with other unsuspected binding proteins that are unique to the individual, can interfere with the reaction between analyte and reagent antibodies in immunoassay. Lipaemia, cross-reactivity, and exogenous interferences due to pre-analytical variation, matrix and equipment reaction also affect immunoassay. Interfering substances may lead to falsely elevated or falsely low analyte concentration in one or more assay systems depending on the site of the interference in the reaction and possibly result in discordant results for other analytes. The prevalence of interference is generally low in assays containing blocking agents that neutralise or inhibit the interference but is often higher in new, untested immunoassays. A wide range of analytes measured by immunoassay including hormones, tumour markers, drugs, cardiac troponin and microbial serology may be affected. Interference in immunoassay may lead to the misinterpretation of a patient's results by the laboratory and the wrong course of treatment being given by the physician. Laboratories should put processes in place to detect, test and report suspected interferences. It is equally important that physicians communicate any clinical suspicion of discordance between the clinical and the laboratory data to the laboratory. The detection of interference may require the use of an alternate assay or additional measurements, before and after treatment with additional blocking reagent, or following dilution of the sample in non-immune serum. It is imperative that laboratories inform physicians of the follow-up procedure and report on the presence of any interference. The establishment of on-going laboratory-physician contact is essential to the continuing awareness of wrong patient results due to interference.

Related Concept Videos
 01:20
Inductively Coupled Plasma-Mass Spectrometry (ICP-MS): Interferences
 01:25
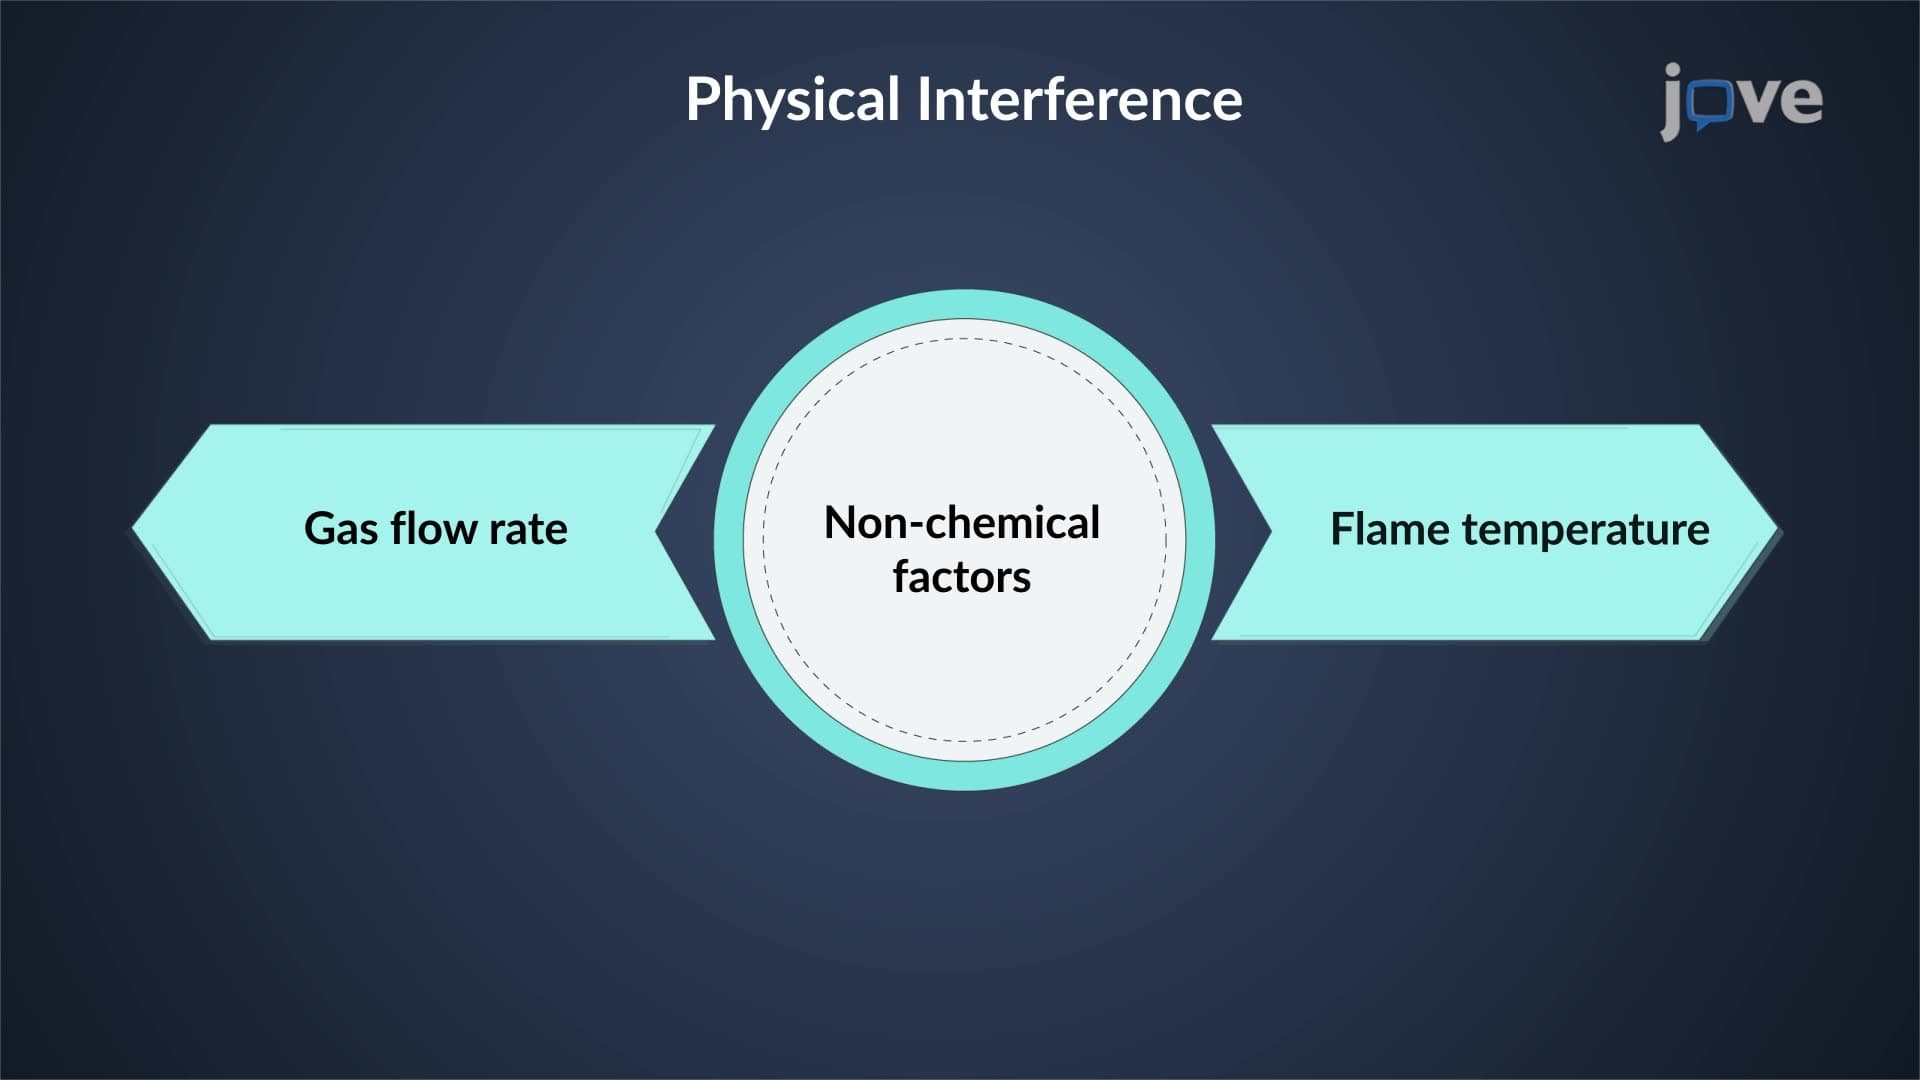
Atomic Absorption Spectroscopy: Interference
Spectral interference occurs when signals from other elements or molecules overlap with the analyte signal, falsely elevating or masking the analyte's absorbance. This interference can be corrected using Zeeman,...
 01:33
Enzyme-Linked Immunosorbent Assay
There are many different types of ELISAs, but they all involve an antibody molecule whose constant region binds an enzyme, leaving the variable region free to bind its specific antigen. Enzyme-substrate reaction allows the antigen to be visualized or quantified.
 01:20
Immunoprecipitation
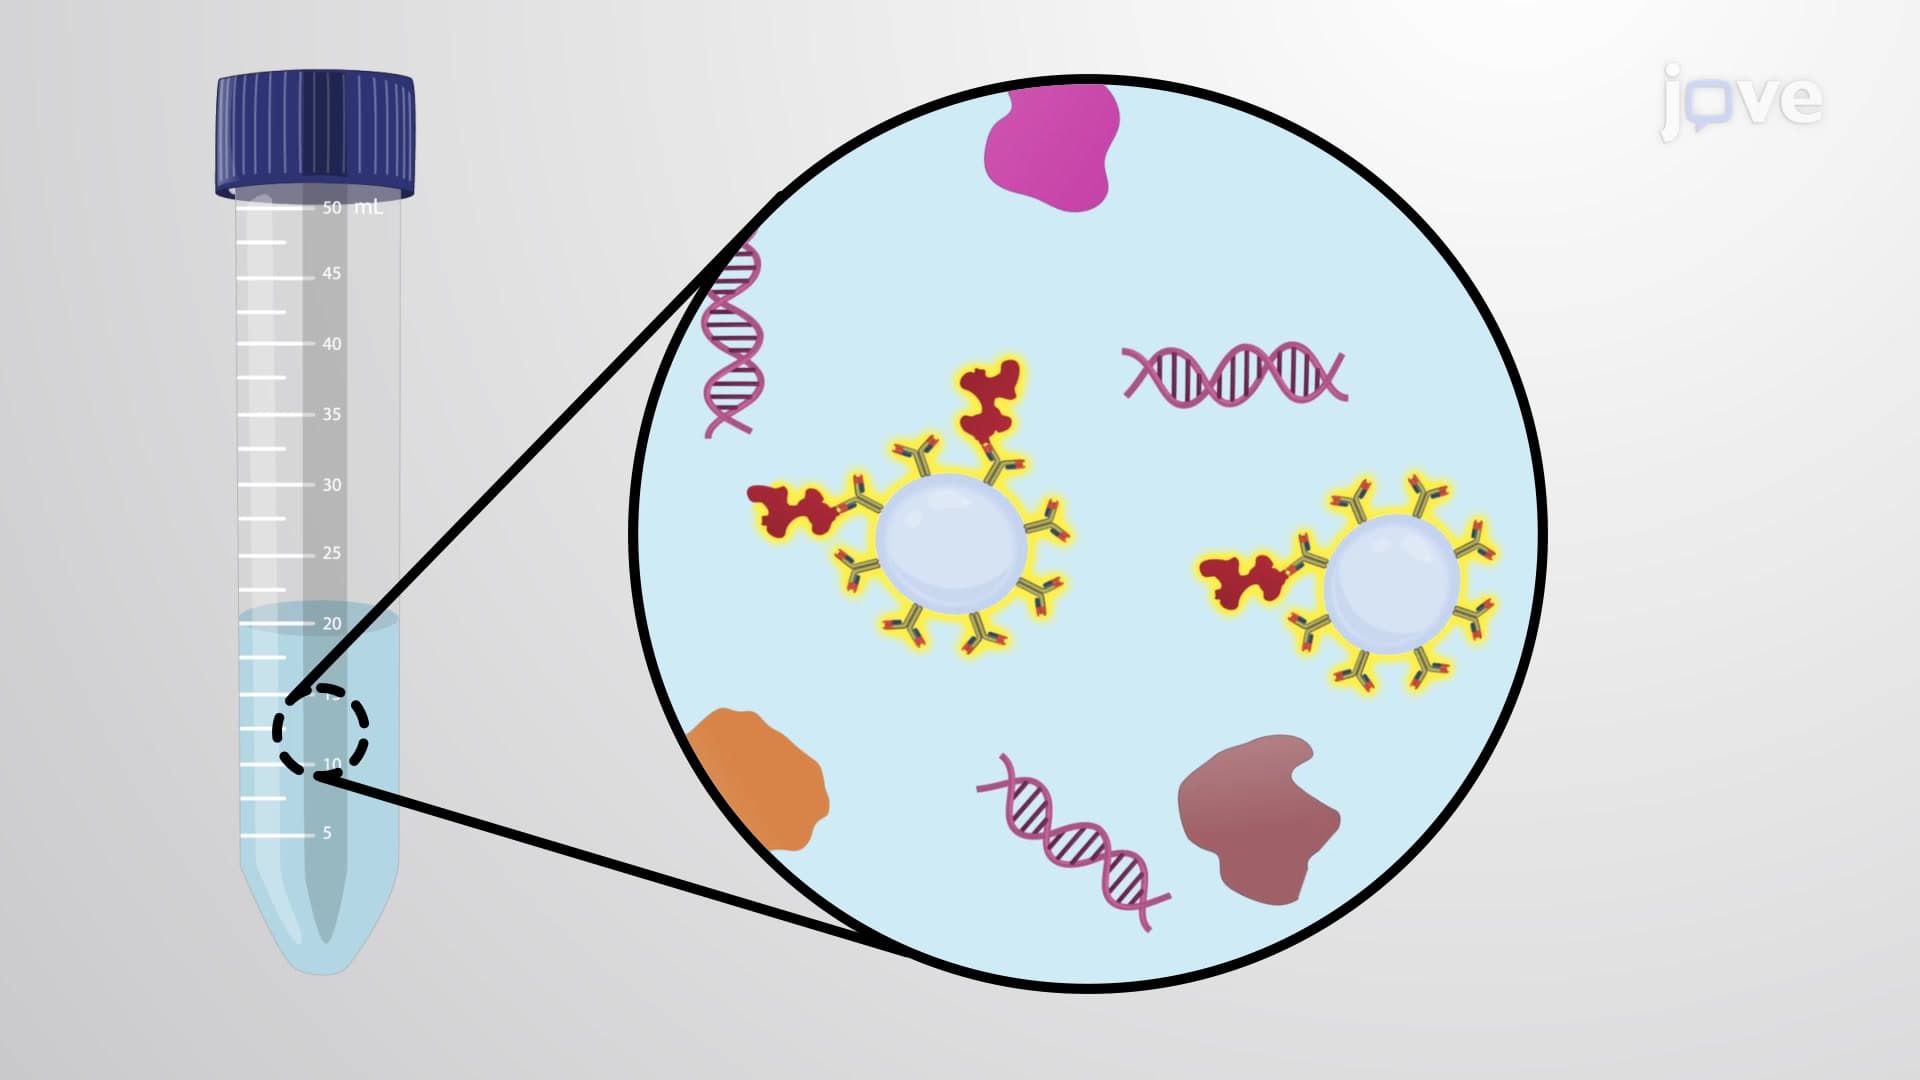
Chromatin Immunoprecipitation
Chromatin immunoprecipitation, also known as ChIP, is used to study protein-DNA or...
 01:30
Atomic Emission Spectroscopy: Interference