Related Experiment Video
Updated: Jul 5, 2026
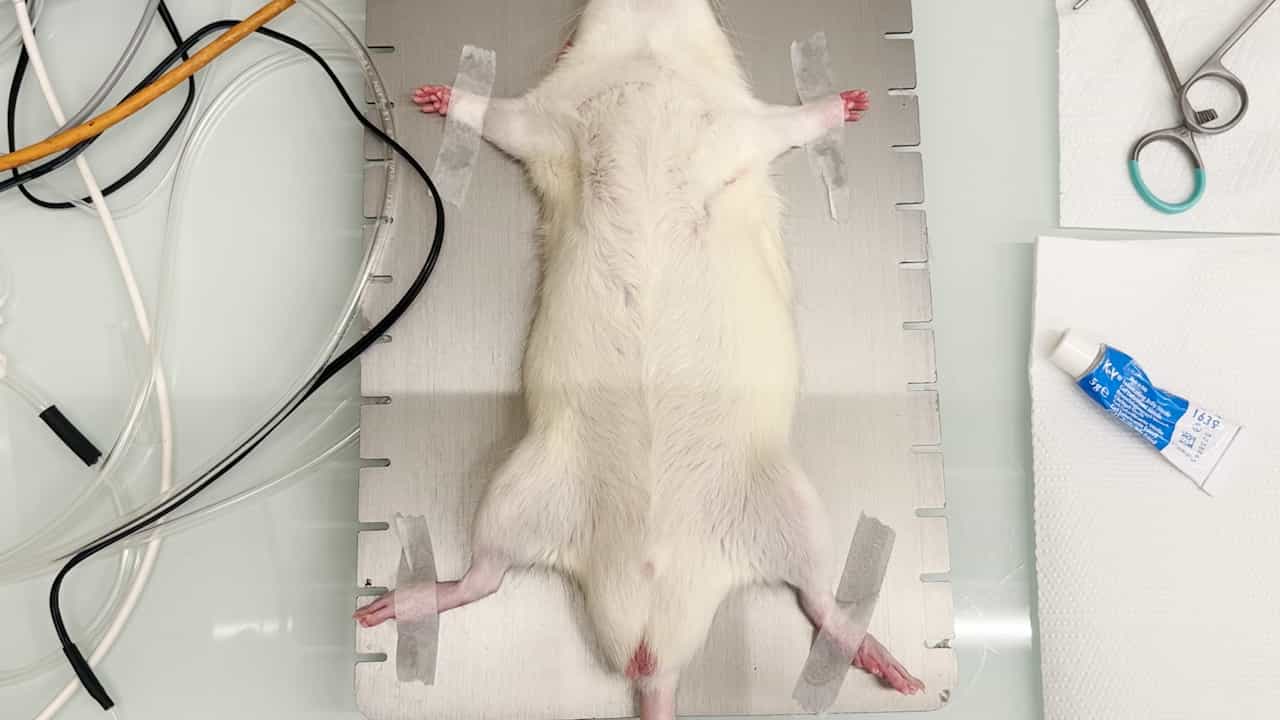

A Model of Acute Lung Injury Following Visceral Ischemia-Reperfusion by Supra-Coeliac Aortic Cross Clamping in Rats
Published on: August 15, 2025
Gut ischemia/reperfusion induced acute lung injury is an alveolar macrophage dependent event
Luciana Borsoi Moraes1, Abel Hiroshi F Murakami, Belchor Fontes
1Laboratory of Medical Investigation of the 3rd Division of Surgical Clinic, Hospital das Clinicas, University of Sao Paulo School of Medicine, Sao Paulo, Brazil.

Background:
Although the role of the lung alveolar macrophage (AM) as a mediator of acute lung injury (ALI) after lung ischemia/reperfusion (I/R) has been suggested by animal experiments, it has not been determined whether AMs mediate ALI after intestinal I/R. The objective of this study was to determine the effect of AM elimination on ALI after intestinal I/R in rats.
Methods:
Male Wistar rats (n = 90) were randomly divided into three groups: the clodronate-liposomes (CLOD-LIP) group received intratracheal treatment with CLOD-LIP; the liposomes (LIP) group received intratracheal treatment with LIP; and the nontreated (UNTREAT) group received no treatment. Twenty-four hours later each group was randomly divided into three subgroups: the intestinal I/R subgroup was subjected to 45-minute intestinal ischemia and 2-hour reperfusion; the laparotomy (LAP) subgroup was subjected to LAP and sham procedures; the control (CTR) subgroup received no treatment. At the end of reperfusion, ALI was quantitated in all the animals by the Evans blue dye (EBD) method.
Results:
ALI values are expressed as EBD lung leakage (microg EBD/g dry lung weight). EBD lung leakage values in the CLOD-LIP group were 32.59 +/- 12.74 for I/R, 27.74 +/- 7.99 for LAP, and 33.52 +/- 10.17 for CTR. In the LIP group, lung leakage values were 58.02 +/- 18.04 for I/R, 31.90 +/- 8.72 for LAP, and 27.17 +/- 11.48 for CTR. In the UNTREAT group, lung leakage values were 55.60 +/- 10.96 for I/R, 35.99 +/- 6.89 for LAP, and 30.83 +/- 8.41 for CTR. Within each group, LAP values did not differ from CTR values. However, in the LIP and UNTREAT groups, values for both the LAP and CTR subgroups were lower than values for the I/R subgroup (p < 0.001). The CLOD-LIP I/R subgroup value was less (p < 0.001) than the I/R subgroup values in the LIP and UNTREAT groups. These results indicated that I/R provokes ALI that can be prevented by CLOD-LIP treatment, and further suggested that AMs are essential for ALI occurrence induced by intestinal I/R in rats.
Insights
Eliminating lung alveolar macrophages (AMs) prevented acute lung injury (ALI) following intestinal ischemia/reperfusion (I/R) in rats. This indicates AMs are crucial mediators of ALI after intestinal I/R.
Area of Science:
- Physiology
- Immunology
- Pathology
Background:
- Alveolar macrophages (AMs) are implicated in lung acute lung injury (ALI) following lung ischemia/reperfusion (I/R).
- The role of AMs in ALI after intestinal I/R remains unclear.
- This study investigates AMs' role in ALI subsequent to intestinal I/R.
Purpose of the Study:
- To determine if AM elimination impacts ALI development after intestinal I/R in rats.
- To elucidate the specific contribution of AMs to intestinal I/R-induced ALI.
Main Methods:
- Male Wistar rats were treated with clodronate-liposomes (CLOD-LIP) to deplete AMs, liposomes (LIP), or no treatment (UNTREAT).
- Animals underwent intestinal ischemia/reperfusion (I/R), laparotomy (LAP), or served as controls (CTR).
- Acute lung injury (ALI) was quantified using the Evans blue dye (EBD) method to measure lung vascular permeability.
Main Results:
- Intestinal I/R significantly increased ALI in LIP and UNTREAT groups compared to sham and control groups.
- CLOD-LIP treatment significantly reduced ALI in the I/R group compared to LIP and UNTREAT groups.
- These findings demonstrate that I/R induces ALI, which is preventable by AM depletion.
Conclusions:
- Alveolar macrophages (AMs) play a critical role in the pathogenesis of ALI following intestinal ischemia/reperfusion (I/R).
- Depletion of AMs effectively mitigates intestinal I/R-induced ALI.
- Targeting AMs may represent a therapeutic strategy for preventing ALI in the context of intestinal I/R injury.
More Related Videos

Related Concept Videos
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:10
Atelectasis II: Pathophysiology
 01:26
Acute Inflammation I: Inflammatory Response