Related Experiment Video
Updated: Jul 5, 2026


Characterization of Sickling During Controlled Automated Deoxygenation with Oxygen Gradient Ektacytometry
Published on: November 5, 2019
Pulmonary complications of sickle cell disease in children
Jason B Caboot1, Julian L Allen
1Division of Pulmonary Medicine and Cystic Fibrosis Center, The Children's Hospital of Philadelphia, Philadelphia, Pennsylvania 19104-4399, USA.

Insights
Sickle cell disease (SCD) significantly impacts lung health in children, leading to conditions like asthma, acute chest syndrome, and pulmonary hypertension. Understanding these pulmonary complications is crucial for improving treatment strategies and patient outcomes.
Area of Science:
- Pulmonary Medicine
- Pediatric Hematology
- Genetics
Background:
- Sickle cell disease (SCD) is a prevalent genetic disorder affecting 1 in 600 African-Americans.
- The lungs are a primary target organ in SCD, contributing to significant childhood morbidity and mortality.
- Pulmonary complications are a major concern for children with SCD.
Purpose of the Study:
- To review recent literature on pulmonary complications in pediatric sickle cell disease.
- To highlight the associations between SCD and various respiratory conditions.
- To emphasize the need for further research into the interrelationships of these pulmonary issues.
Main Methods:
- Literature review of recent studies on sickle cell disease and pulmonary manifestations.
- Synthesis of evidence linking asthma, airway hyperreactivity, acute chest syndrome, and pulmonary hypertension with SCD.
- Analysis of findings related to sleep-disordered breathing in children with SCD.
Main Results:
- Strong associations found between asthma, airway hyperreactivity, and SCD.
- Acute chest syndrome (ACS) in SCD is linked to worse pulmonary function and vaso-occlusive crisis.
- Pulmonary hypertension and sleep-disordered breathing are increasingly recognized in children with SCD.
Conclusions:
- Key pulmonary complications in SCD include airway hyperreactivity, ACS, chronic sickle lung disease, pulmonary hypertension, and sleep-disordered breathing.
- Understanding the interplay between these conditions is vital for developing effective therapies.
- Further research is needed to elucidate the mechanisms and improve management of pulmonary issues in pediatric SCD.
Purpose Of Review:
Sickle cell disease is one of the most prevalent genetic diseases, affecting 1 in 600 African-Americans. The lung is one of the major organs affected in sickle cell disease and the pulmonary complications of sickle cell disease result in significant morbidity and mortality in children.
Recent Findings:
Recent literature has provided evidence supporting the strong association between asthma and airway hyperreactivity and sickle cell disease, as well as a link with acute chest syndrome and vaso-occlusive crisis. Additionally, children with sickle cell disease who have acute chest syndrome episodes have worse pulmonary function than those who have not experienced acute chest syndrome episodes. An increasing amount of literature highlights the link between pulmonary hypertension and sickle cell disease, and multiple mechanisms have been invoked to explain why patients with sickle cell disease are prone to the development of pulmonary hypertension. Previous and current studies have also highlighted the manifestations of sleep disordered breathing in children with sickle cell disease.
Summary:
The pulmonary complications of sickle cell disease include airway hyperreactivity, acute chest syndrome, chronic sickle lung disease, pulmonary hypertension, and sleep disordered breathing. Further understanding of the interrelationships between these disorders will lead to improved therapies.

Related Concept Videos
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD:
 01:17
Pulmonary Cycle: Exhalation
 01:30
Pneumonia III: Complications and Assessment
 01:19
Chronic Obstructive Pulmonary Disease IV: Clinical Manifestations
 01:29
Pulmonary Embolism I: Introduction
 01:19
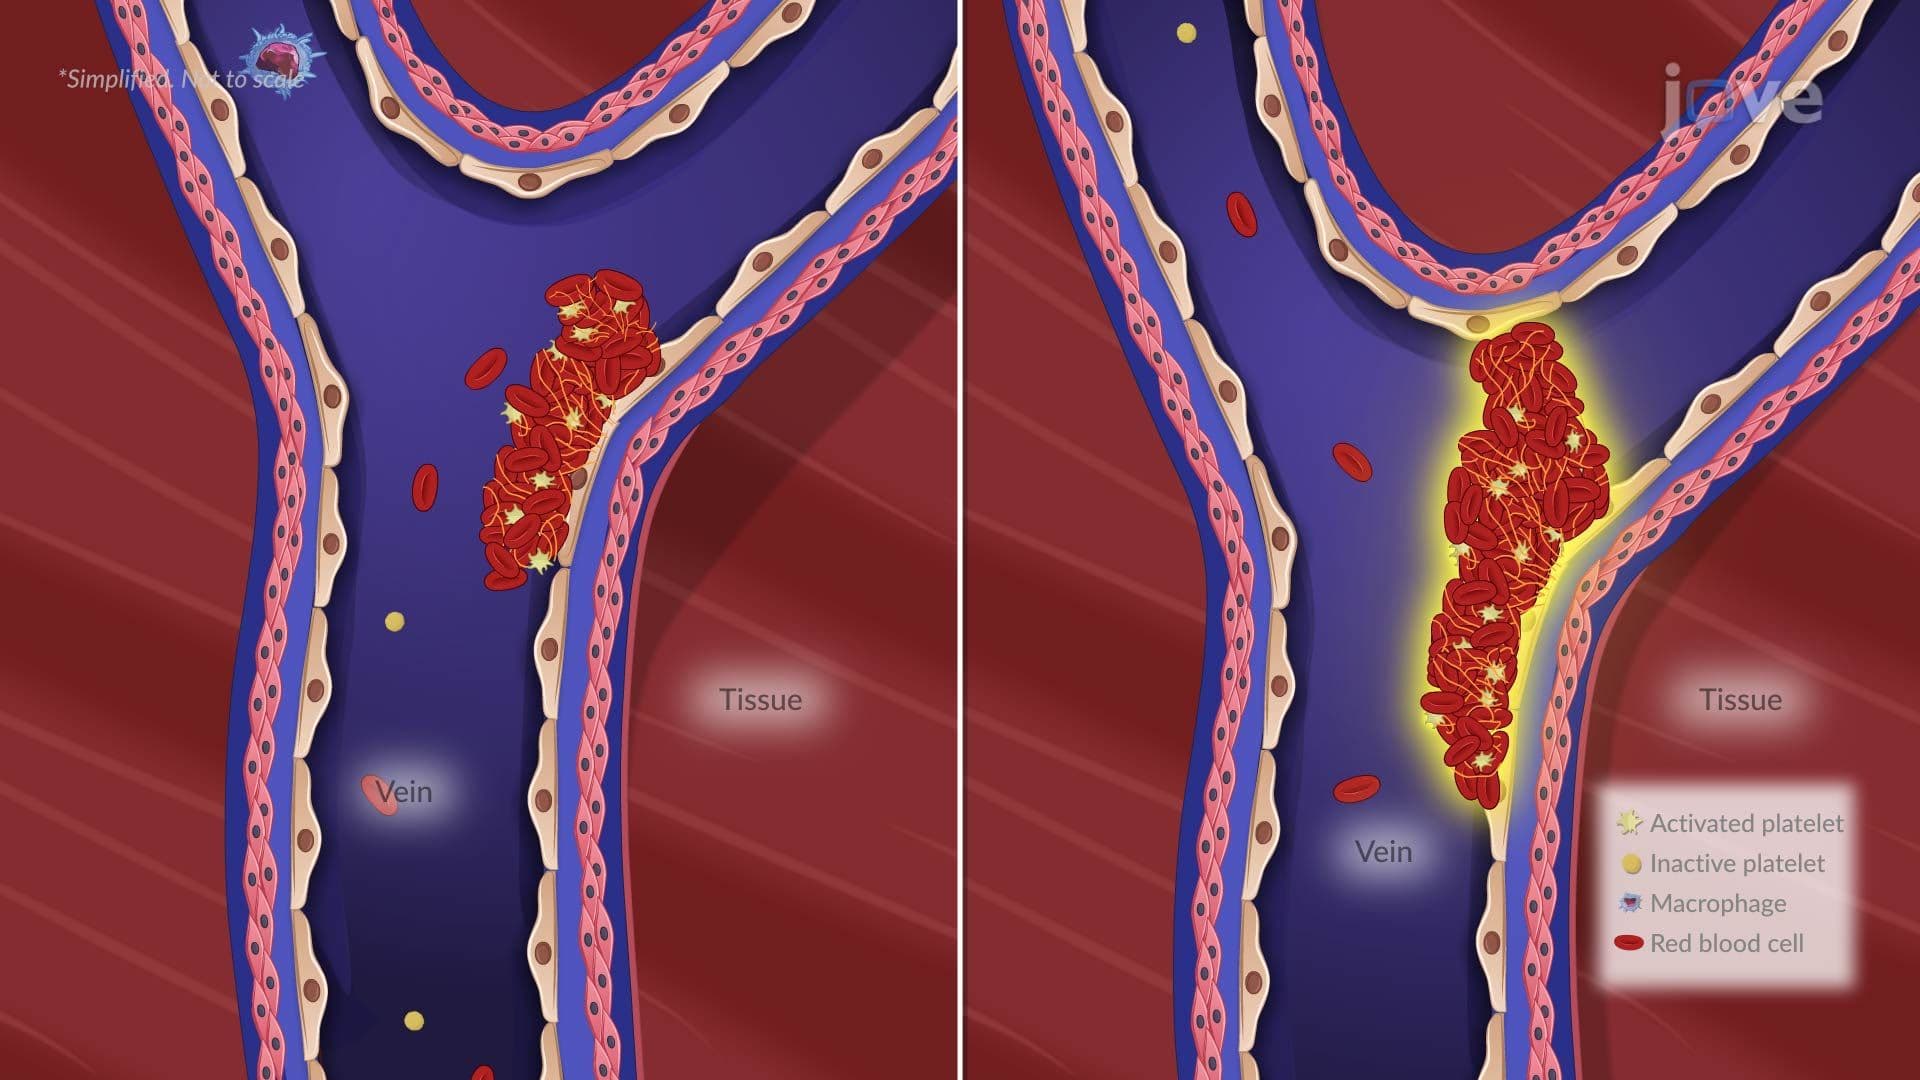
Pulmonary Embolism I: Introduction