Prevention and treatment of gastrointestinal dysfunction following severe burns: a summary of recent 30-year clinical experience
Related Experiment Video
Updated: Jul 4, 2026
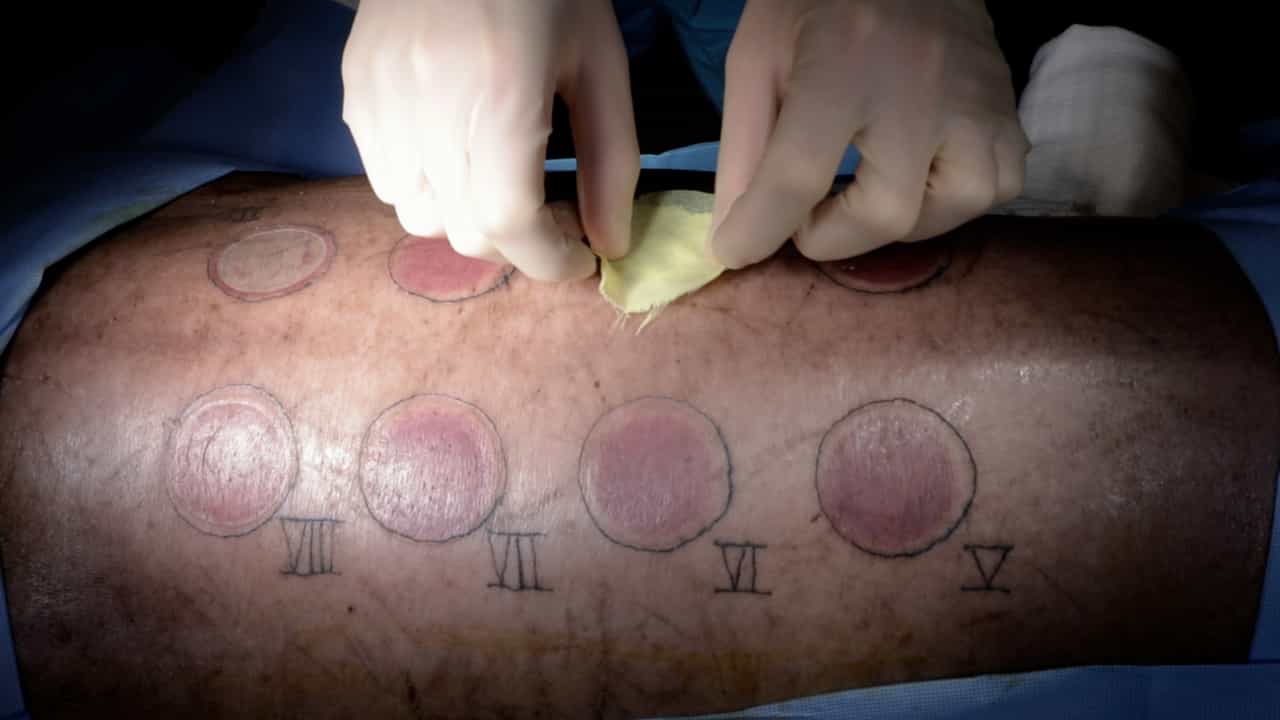
A Swine Burn Model for Investigating the Healing Process in Multiple Depth Burn Wounds
Published on: February 23, 2024
Shi-Chu Xiao1, Shi-Hui Zhu, Zhao-Fan Xia
1Department of Burn Surgery, Changhai Hospital, Second Military Medical University, 174 Changhai Road, Shanghai 200433, China.

Aim:
To sum up the recent 30-year experience in the prevention and treatment of gastrointestinal dysfunction in severe burn patients, and propose practicable guidelines for the prevention and treatment of gastrointestinal (GI) dysfunction.
Methods:
From 1980 to 2007, a total of 219 patients with large area and extraordinarily large area burns (LAB) were admitted, who were classified into three stages according the therapeutic protocols used at the time: Stage 1 from 1980 to 1989, stage 2 from 1990 to 1995, and stage 3 from 1996 to 2007. The occurrence and mortality of GI dysfunction in patients of the three stages were calculated and the main causes were analyzed.
Results:
The occurrence of stress ulcer in patients with LAB was 8.6% in stage 1, which was significantly lower than that in stage 1 (P < 0.05). No massive hemorrhage from severe stress ulcer and enterogenic infections occurred in stages 2 and 3. The occurrence of abdominal distension and stress ulcer and the mortality in stage 3 patients with extraordinarily LAB was 7.1%, 21.4% and 28.5%, respectively, which were significantly lower than those in stage 1 patients (P < 0.05 or P < 0.01), and the occurrence of stress ulcer was also significantly lower than that in stage 2 patients (P < 0.05).
Conclusion:
Comprehensive fluid resuscitation, early excision of necrotic tissue, staged food ingestion, and administration of specific nutrients are essential strategies for preventing gastrointestinal complications and lowering mortality in severely burned patients.

Related Concept Videos
 01:22
Burn Injuries
The damage results in the death of skin cells, which can lead to a massive loss of fluid. Dehydration, electrolyte imbalance, and renal and circulatory failure follow, which can be fatal. Burn patients are treated with intravenous fluids to offset...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:24
Drugs for Peptic Ulcer Disease: Sucralfate as Mucosal Protective Agents
In this scenario, mucosal protective agents like sucralfate play an essential role. Sucralfate, a complex of sulfated sucrose and aluminum hydroxide, demonstrates its usefulness in acidic conditions,...
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...