Related Experiment Video
Updated: Jul 4, 2026

05:52

Handwriting Analysis Indicates Spontaneous Dyskinesias in Neuroleptic Naïve Adolescents at High Risk for Psychosis
Published on: November 21, 2013
Diabetic ketoacidosis induced by aripiprazole in a 12-year-old boy
Diabetes Care
|May 30, 2008

Abstract
No abstract available in PubMed .
Related Concept Videos
 01:25
Diabetic Ketoacidosis l: Introduction
DefinitionDiabetic ketoacidosis (DKA) is an acute, life-threatening complication of diabetes mellitus, characterized by a triad of hyperglycemia (blood glucose >250 mg/dL), ketonemia or ketonuria, and metabolic acidosis (arterial pH <7.30 and serum bicarbonate <18 mEq/L). It results from insulin deficiency combined with elevated levels of counterregulatory hormones—glucagon, catecholamines, cortisol, and growth hormone—leading to increased lipolysis, hepatic ketone production, and...
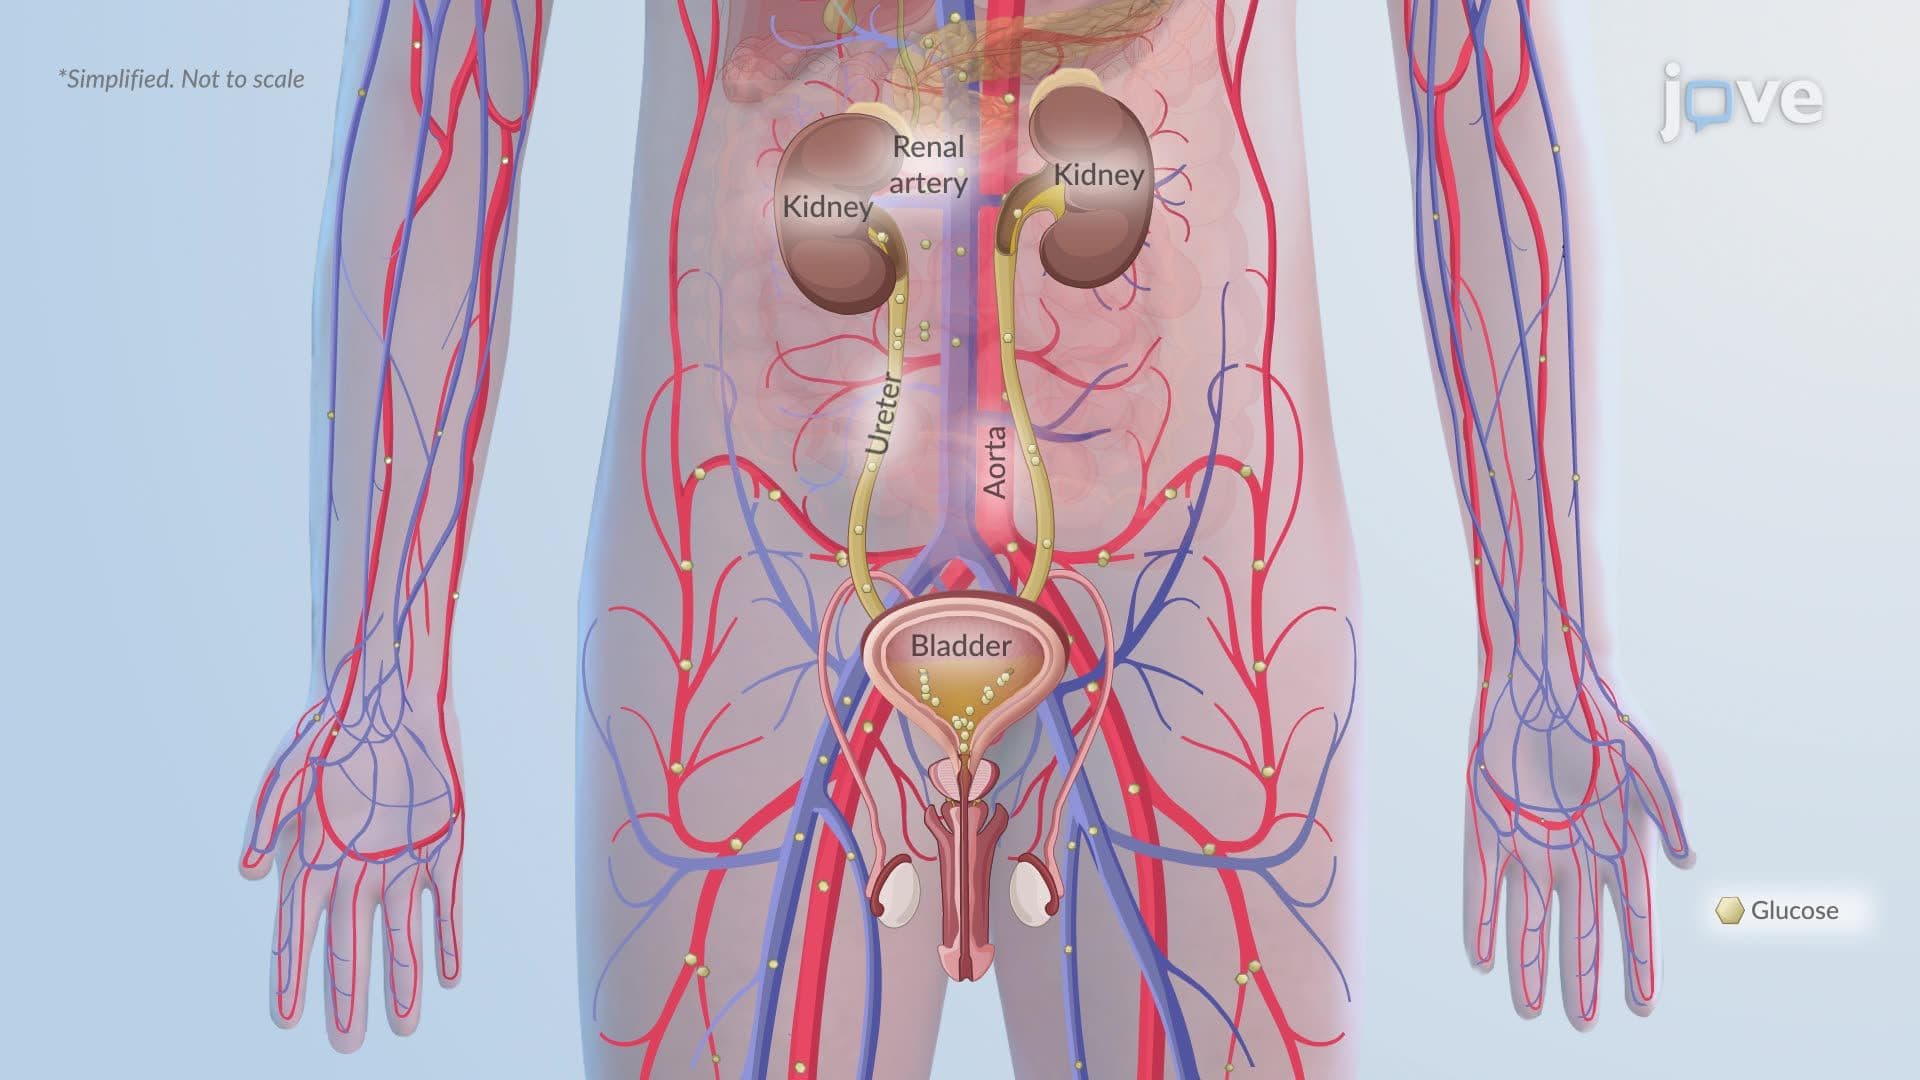 01:22
Diabetic Ketoacidosis ll: Pathophysiology
Diabetic ketoacidosis (DKA) is a metabolic emergency characterized by hyperglycemia, ketonemia, and metabolic acidosis. It results from severe insulin deficiency and an excess of counterregulatory hormones, leading to uncontrolled lipolysis, ketogenesis, and widespread electrolyte and fluid disturbances.Pathophysiology The central event in DKA is a profound loss of insulin action. Without insulin, glucose uptake in insulin-dependent tissues is impaired, while hepatic glucose production...
 01:16
Insulin: Dosing Regimen and Adverse Effects
Insulin-replacement therapy usually includes both long-acting insulin (basal) and short-acting insulin (to cater to postprandial needs). In a diverse group of type 1 diabetes patients, the average daily insulin dose is typically 0.5-0.7 units/kg body weight. However, obese patients and pubertal adolescents may need more due to insulin resistance.
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
In pediatric care, understanding the nuances of hepatic drug metabolism is crucial, as it significantly differs from that of adults. This divergence is primarily due to the developmental stage of drug-metabolizing enzymes, which affects how medications are processed in the body. In neonates, for instance, the activity of Phase I enzymes—critical for the initial breakdown of drugs—is markedly reduced, functioning at just 20–40% of the levels seen in adults. This reduction poses a challenge in...
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
Hepatic impairment, characterized by decreased liver function, does not uniformly mandate adjustments in drug dosage. Whether dosage modifications are necessary depends on various factors related to the drug's metabolism and elimination pathways. If a drug is primarily excreted via the kidneys and bypasses significant hepatic processing, if it undergoes minimal metabolic transformation in the liver, or if it is volatile and primarily expelled through the lungs, dose adjustments may not be...
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
Understanding the physiological differences in the pediatric population is crucial for effective pharmacotherapy. Neonates, infants, and children exhibit significant variations in gastric pH, gastric emptying time, intestinal transit time, and biliary function. These variations profoundly affect oral drug absorption, necessitating a nuanced approach to pediatric dosing.Neonates present with a unique physiological profile, having a gastric pH greater than 4 and faster and more irregular gastric...