Related Experiment Video
Updated: Jul 4, 2026


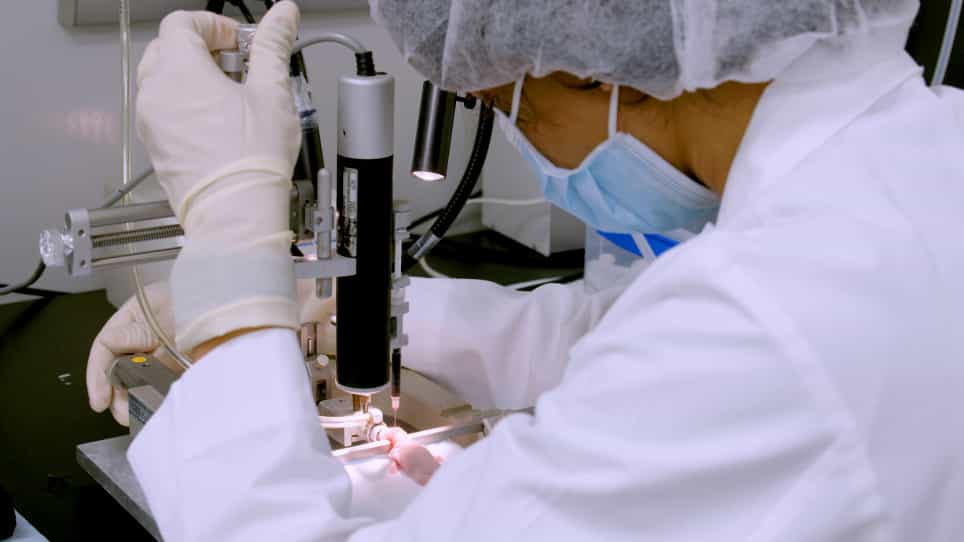
Tail Vein Transection Bleeding Model in Fully Anesthetized Hemophilia A Mice
Published on: September 30, 2021
Haemophilia in the first years of life
R Ljung1, H Chambost, A-M Stain
1Departments of Paediatric, Lund University, University Hospital, Malmö, Sweden. rolf.ljung@med.lu.se

Insights
Surgery for children with haemophilia (a bleeding disorder) is safe with proper diagnosis and factor prophylaxis. However, intracranial hemorrhage (ICH) remains a significant risk in newborns, highlighting the need for improved diagnostics and care protocols.
Area of Science:
- Pediatric Surgery
- Hematology
- Pediatric Critical Care
Background:
- Surgery in children with haemophilia (a bleeding disorder) poses risks of hemorrhage.
- In developed nations, inhibitor development is now a primary surgical complication, surpassing hemorrhage due to intensive treatment.
- Neonatal intracranial hemorrhage (ICH) occurs in 3.5-4.0% of hemophilia boys, significantly higher than the general population.
Purpose of the Study:
- To assess the risks and complications associated with surgery in infants and young children with haemophilia.
- To highlight the importance of accurate diagnosis and factor prophylaxis in managing surgical risks.
- To discuss the challenges and potential preventative strategies for neonatal intracranial hemorrhage (ICH) and central venous line complications.
Main Methods:
- Review of surgical outcomes in pediatric haemophilia patients.
- Analysis of complication rates, including hemorrhage, inhibitor development, ICH, and central venous line issues.
- Discussion of preventative measures and current research on managing these complications.
Main Results:
- Surgery is not associated with significant hemorrhage risk in diagnosed and prophylactically treated pediatric haemophilia patients.
- Inhibitor development is the main surgical complication in the developed world, necessitating careful consideration for essential surgeries only.
- Neonatal ICH is a significant concern, partially preventable through improved carrier diagnosis and counseling.
- Infections and thrombosis are major complications of central venous lines, with variations likely due to care protocols, education, and user compliance.
Conclusions:
- Safe surgical outcomes for pediatric haemophilia patients are achievable with accurate diagnosis and effective factor prophylaxis.
- Managing inhibitor development and reducing neonatal ICH are critical areas for improving patient care.
- Standardizing central venous line care protocols and user education is essential to mitigate associated complications.
Abstract:
Surgery in infants and young children with haemophilia, when preceded by accurate diagnosis and accompanied by safe and effective factor prophylaxis, is not associated with a significant risk of haemorrhage. Haemophilic newborns undergoing circumcision or major surgery prior to diagnosis and in the absence of appropriate haemostatic prophylaxis remain as a concern. Inhibitor development has replaced haemorrhage as the major surgical complication in the developed world, largely because of the intensity of treatment used to secure haemostasis. For that reason only, essential surgery should be performed. Intracranial haemorrhage (ICH) during the neonatal period affects 3.5-4.0% of all haemophilia boys in countries with a good standard of health care, which is considerably (40-80 times) higher than expected in the normal population. Because of the high frequency of sporadic cases, ICH in the neonatal period can only be partially prevented by improved carrier diagnosis and counselling. Infections and thrombosis are the major serious complications of central venous lines. Large differences are seen in the frequency of these complications, the most plausible explanations are probably related to the protocol used for device care, the quality of education and the compliance of the users, an issue addressed in an on-going study.

Related Concept Videos
 01:24
Disorders of Hemostasis
Thromboembolic Disorders
Two factors primarily cause thromboembolic conditions.
 01:19
Rh Blood Group
 01:20
Overview of Hematopoiesis
Developmental Phases of Hematopoiesis
Initially, HSCs are formed in the embryonic yolk sac, a critical site for early blood cell production. These stem cells subsequently migrate to other...
 01:20
Extrinsic and Intrinsic Pathways of Hemostasis
The Extrinsic Pathway
The extrinsic pathway of coagulation is typically initiated by tissue damage that exposes blood to tissue factor (TF), a protein released by the damaged tissue cells outside the blood vessels—this interaction with TF triggers biochemical reactions involving specific clotting factors. The key player here is Factor VII, which forms a...
 01:22
Development of Immunocompetence
The initial cells that migrate from the fetal thymus settle within the skin and epithelial tissues lining the mouth, digestive tract, and in females, the uterus and vagina. These cells, including skin-based dendritic cells, serve as antigen-presenting cells, playing a key role in T cell activation.
Subsequent T...
 01:21
Hematopoiesis