Related Experiment Video
Updated: Jul 4, 2026
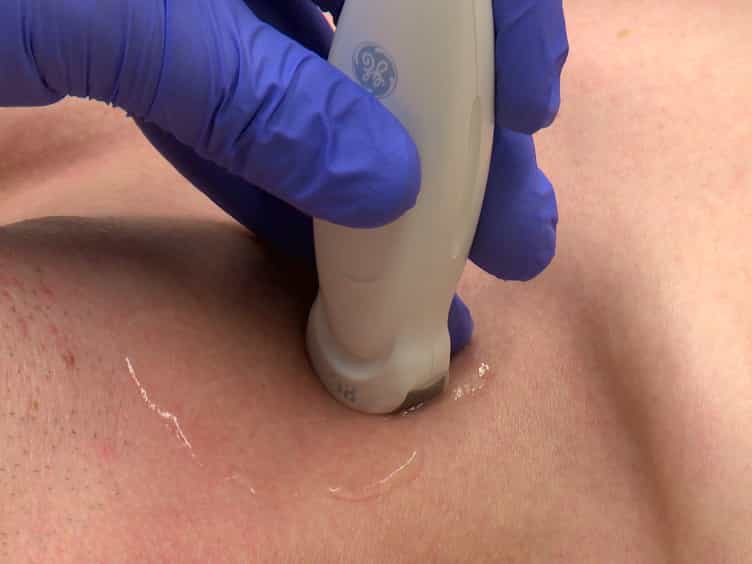

The Supraclavicular Fossa Ultrasound View for Central Venous Catheter Placement and Catheter Change Over Guidewire
Published on: December 23, 2014
Ultrasound-guided supraclavicular vs infraclavicular brachial plexus blocks in children
Belén De José María1, Ester Banús, Montse Navarro Egea
1Department of Paediatric Anaesthesiology, Hospital Sant Joan de Déu, University of Barcelona, Barcelona, Spain. bdejosemaria@hsjdbcn.org

Insights
Ultrasound-guided supraclavicular brachial plexus blocks are faster and as effective as infraclavicular blocks in children, with no increased risk of pneumothorax. This study demonstrates the safety and efficiency of the supraclavicular approach for pediatric regional anesthesia.
Area of Science:
- Pediatric Anesthesiology
- Regional Anesthesia
- Ultrasound-Guided Procedures
Background:
- Supraclavicular brachial plexus blocks are less common in children due to pneumothorax risk.
- Infraclavicular blocks are established in pediatric patients using nerve stimulation and ultrasound (US).
- US guidance improves safety for supraclavicular blocks in adults.
Purpose of the Study:
- To compare the success rate, complication incidence, and performance time of US-guided supraclavicular versus infraclavicular brachial plexus blocks in children.
- To evaluate the efficacy and safety of these two US-guided regional anesthesia techniques in pediatric upper limb surgery.
Main Methods:
- Eighty children (5-15 years) undergoing upper limb surgery were randomized into two groups: supraclavicular (S, n=40) and infraclavicular (I, n=40).
- All blocks were exclusively US-guided by experienced anesthesiologists.
- Ropivacaine 0.5% was administered to achieve adequate US-guided spread; success rates, complications, and block performance times were recorded.
Main Results:
- Success rates for surgical anesthesia were high in both groups (95% in S vs. 88% in I), with no statistically significant difference (P = 0.39).
- The supraclavicular approach was significantly faster to perform (9 min vs. 13 min, P < 0.05).
- No pneumothorax or Horner's syndrome occurred in either group; failures were attributed to arterial puncture or insufficient sensory block.
Conclusions:
- Ultrasound-guided supraclavicular and infraclavicular brachial plexus blocks are effective pediatric anesthesia techniques.
- The supraclavicular approach, using an in-plane technique in children aged 5 years and older, demonstrated no pneumothorax complications.
- The supraclavicular brachial plexus block was found to be a faster procedure compared to the infraclavicular approach in this pediatric study.
Background:
Supraclavicular brachial plexus blocks are not common in children because of risk of pneumothorax. However, infraclavicular brachial plexus blocks have been described in paediatric patients both with nerve stimulation and ultrasound (US)-guidance. US-guidance reduces the risk of complications in supraclavicular brachial plexus blocks in adults.
Objective:
To compare the success rate, complications and time of performance of US-guided supraclavicular vs infraclavicular brachial plexus blocks in children.
Material And Methods:
Eighty children, 5-15 years old, scheduled for upper limb surgery were divided into two randomized groups: group S (supraclavicular), n = 40, and group I (infraclavicular), n = 40. All blocks performed were exclusively US-guided, by a senior anaesthesiologist with at least 6 months of experience in US-guided blocks. For supraclavicular blocks the probe was placed in coronal-oblique-plane in the supraclavicular fossa and the puncture was in-plane (IP) from lateral to medial. For infraclavicular blocks the probe was placed parallel and below the clavicle and the puncture was out-of-plane. Ropivacaine 0.5% was administered up to a maximum of 0.5 ml x kg(-1) until appropriate US-guided-spread was achieved. Block duration and volumes of ropivacaine used (mean+/-1SD) in the supraclavicular approach were recorded. Success rate (mean +/- 1 SD, 95%confidence interval), complications rate and time to perform the block (two-tailed Student's test) were recorded both for supraclavicular and infraclavicular approaches.
Results:
In the US-guided supraclavicular brachial plexus blocks, the duration of the sensory block was 6.5 +/- 2 h and of the motor block was 4 +/- 1 h. The volume of ropivacaine used in this group was 6 +/- 2 ml. In group I, 88% of blocks achieved surgical anaesthesia without any supplemental analgesia compared with 95% in group S (P = 0.39; difference=7%; 95% CI: -10% to 24%). Failures in group I were because of arterial puncture and insufficient ulnar or radial sensory block. Failures in group S were because of insufficient ulnar sensory block. No pneumothorax or Horner's syndrome was recorded in either group. The mean time (SD) to perform the block was in group I: 13 min (range 5-16) and in group S: 9 min (range 7-12); the 95% CI for this difference was 2-6 min and was statistically significant (P < 0.05).
Conclusions:
(i) Ultrasound-guided supraclavicular and infraclavicular brachial plexus blocks are effective in children. (ii) There has been no pneumothorax in 40 US-guided supraclavicular brachial plexus blocks performed by anaesthesiologists already trained in US-guided regional anaesthesia using an IP technique in children > or =5 years old. (iii) In this study, the supraclavicular approach of the brachial plexus was faster to perform than the infraclavicular one.

Related Concept Videos
 01:22
Spinal Nerves: Plexus I
The Cervical Plexus
The cervical plexus, formed by the anterior rami of the first four...
 01:16
Local Anesthetics: Clinical Application as Intravenous Regional Anesthesia
One of the advantages of...
 01:19
Depolarizing Blockers: Pharmocokinetics
 01:17
Assessment of apical pulse
Assessing the apical pulse is a critical nursing procedure, particularly indicated for: