Related Experiment Video
Updated: Jul 4, 2026
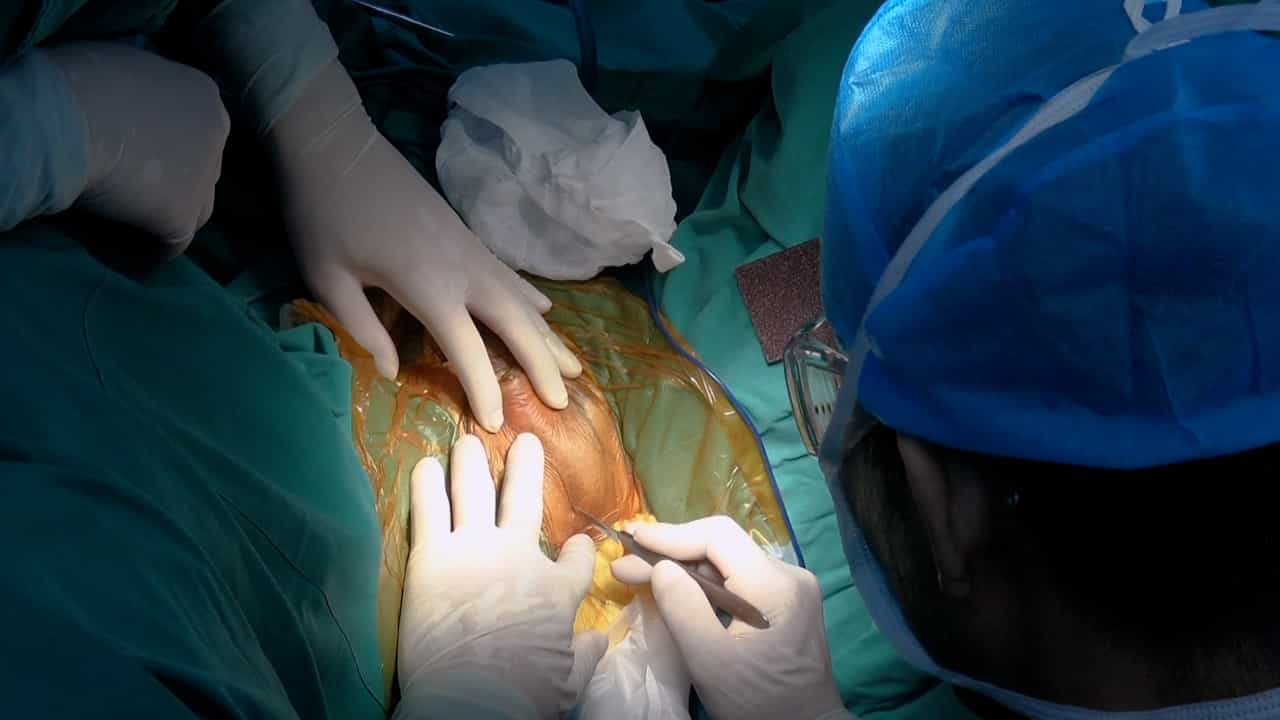

Transcorporal Artificial Urinary Sphincter Cuff Placement in a Case Requiring Revision for Urethral Atrophy
Published on: June 16, 2022
Artificial urinary sphincter in children--voiding or emptying? An evaluation of functional results in 44 patients
M Catti1, S Lortat-Jacob, M Morineau
1Service de Chirurgie Infantile, Professor Yann Revillon, Hôpital Necker-Enfants Malades, Paris, France. massimocatti@libero.it

Insights
The artificial urinary sphincter (AUS) offers good continence for pediatric patients but has frequent complications, leading to removal in 20%. Many patients require clean intermittent catheterization for bladder emptying post-implantation.
Area of Science:
- Urology
- Pediatric Surgery
- Reconstructive Urology
Background:
- Urinary incontinence in children and adolescents often necessitates advanced treatment options.
- The artificial urinary sphincter (AUS) is a device used to manage severe urinary incontinence.
Purpose of the Study:
- To evaluate the functional outcomes of artificial urinary sphincter implantation in pediatric and adolescent patients.
- Assessing complications, continence rates, and voiding abilities following AUS implantation.
Main Methods:
- A cohort of 44 pediatric and adolescent patients (median age 14) received a pericervical AMS 800 artificial urinary sphincter.
- Patients had a median follow-up of 5.5 years, with some having undergone prior or concurrent augmentation cystoplasty.
- Complications included dysuria, retention, bladder dysfunction, erosions, mechanical failures, and infections, leading to device removals, deactivations, revisions, and replacements.
Main Results:
- After AUS removal, 20% of patients remained incontinent.
- Among patients with the AUS in place, 73% achieved dryness, while 7% remained incontinent with a deactivated device.
- Spontaneous voiding to completion was achieved by 48.6% of patients; 25.7% required post-void catheterization, and 25.7% relied solely on clean intermittent catheterization (CIC).
- Implantation before puberty or with an augmented bladder significantly decreased the ability to void spontaneously.
Conclusions:
- The artificial urinary sphincter demonstrates efficacy in achieving urinary continence in pediatric and adolescent populations.
- Frequent complications necessitate device intervention in a significant percentage of cases, with 20% requiring removal.
- Long-term bladder emptying without clean intermittent catheterization is limited for many patients.
Purpose:
We evaluated functional results with an artificial urinary sphincter in children and adolescents in terms of complications, continence and voiding ability through followup.
Materials And Methods:
A total of 44 patients (39 males and 5 females, age 8.6 to 29.5 years, median 14) underwent implantation of a pericervical AMS 800trade mark artificial urinary sphincter, primarily for severe urinary incontinence of neuropathic origin, between 1986 and 2005. Of the patients 25 had undergone augmentation cystoplasty previously (8), simultaneously (7) or after implantation (10). Median followup was 5.5 years (range 1 to 18). Complications included dysuria and/or urinary retention (24 cases), worsening of bladder function (13), urethral erosion (2), scrotal erosion (5), mechanical dysfunction (7), infection of the artificial urinary sphincter (2) and accidental puncture of the tubes (2). These complications resulted in 9 removals, 5 deactivations, 6 revisions and 5 total replacements.
Results:
Of 44 patients 9 (20%) were incontinent after removal of the artificial urinary sphincter. Among the remaining patients 32 (73%) were dry and 3 (7%) were incontinent with a deactivated device. Of the 35 patients with an artificial urinary sphincter in place 17 (48.6%) voided to completion with spontaneous voiding, 9 (25.7%) performed post-void clean intermittent catheterization and 9 (25.7%) emptied exclusively with clean intermittent catheterization. The ability to maintain voiding to completion after implantation was significantly decreased when the artificial urinary sphincter was implanted before puberty (p = 0.0025) or in conjunction with an augmented bladder (p = 0.01).
Conclusions:
The artificial urinary sphincter provides a good rate of continence. However, complications are frequent, leading to removal in 20% of the cases. In time only a limited number of patients can empty the bladder without clean intermittent catheterization.

Related Concept Videos
 01:19
Urodynamic Studies: Uroflowmetry
 01:22
Imaging Studies VI: Voiding Cystourethrography and Cystography
 01:26
The Micturition Reflex
The process begins with bladder filling, where the bladder wall stretches as urine accumulates. This stretching activates the urine storage reflex, mediated by the sacral spinal segments and the pontine storage center. Efferent sympathetic impulses stimulate the detrusor muscle to relax and the internal urethral sphincter to contract, facilitating urine...
 01:19
Anatomy of the Genitourinary System II: Bladder and Urethra
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:28
Urinary Tract Calculi V: Nursing Management