Related Experiment Video
Updated: Jul 4, 2026
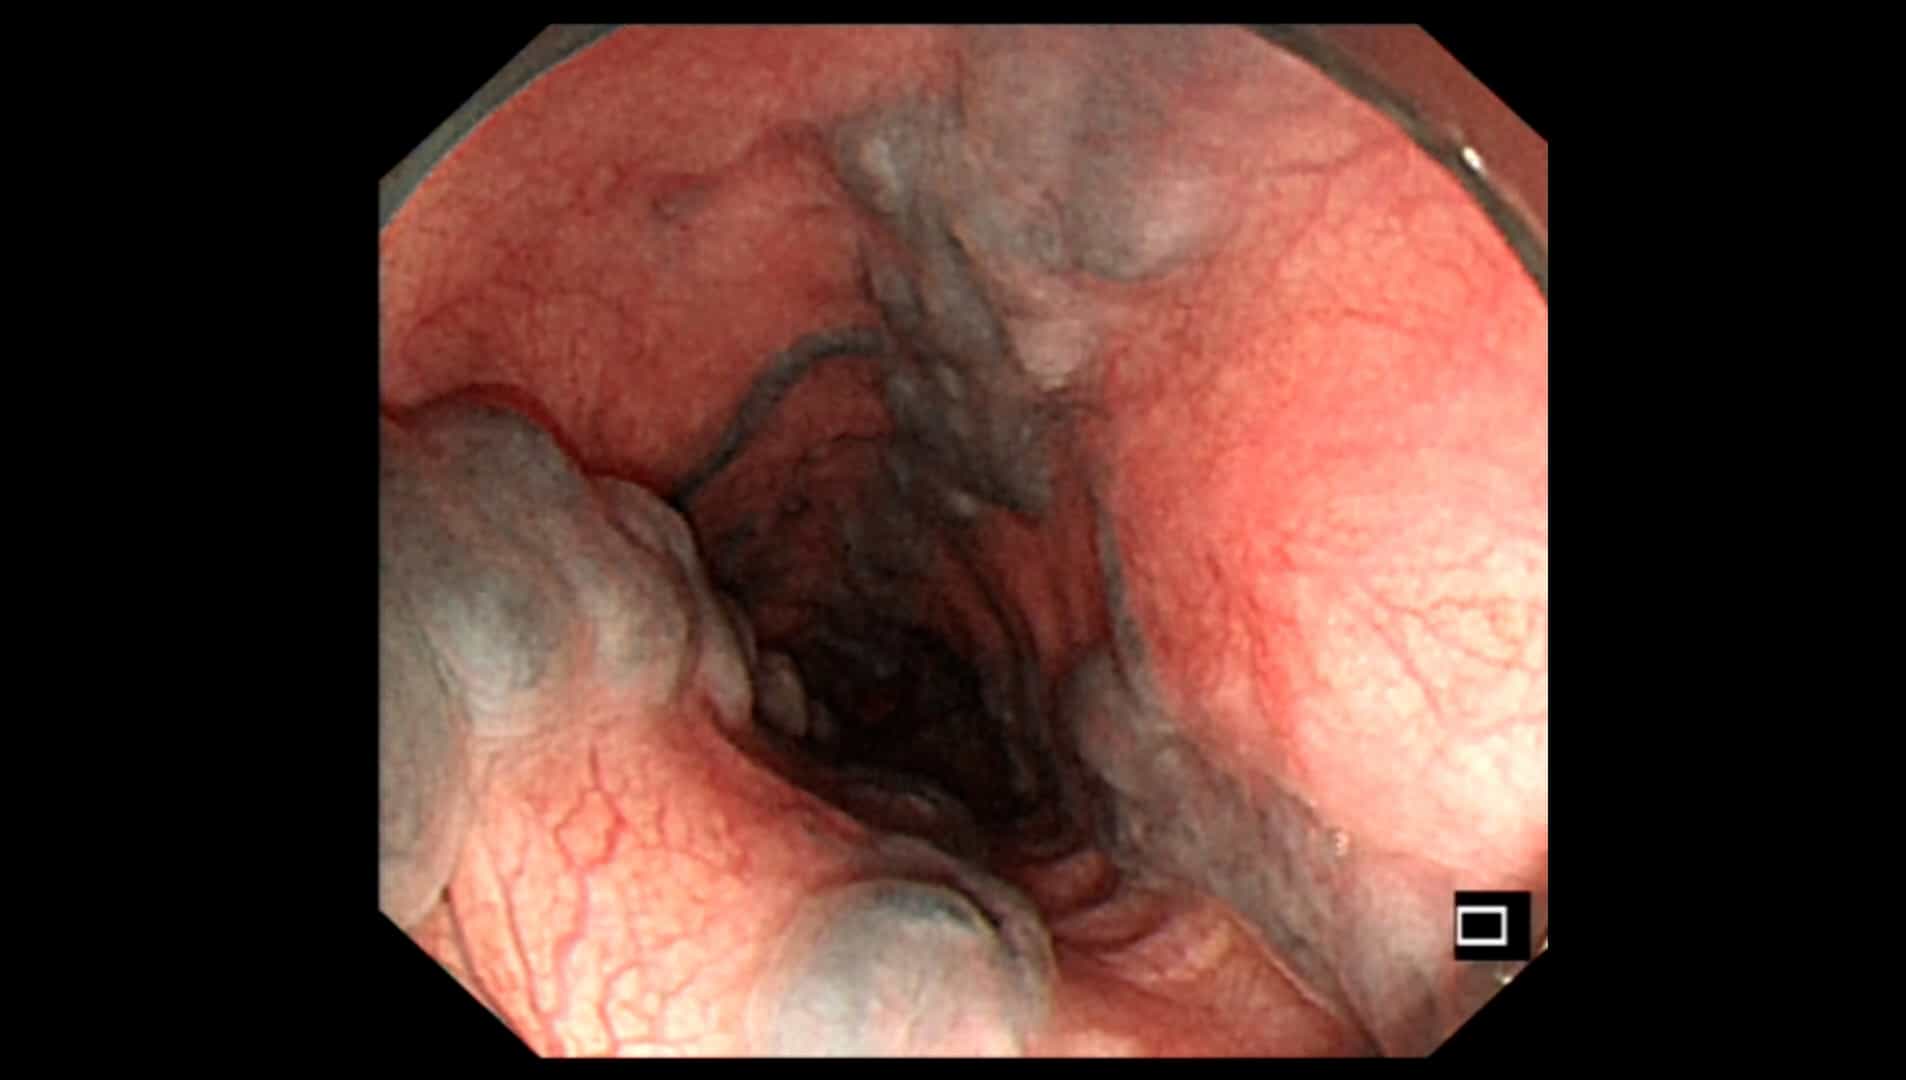
Underwater Endoscopic Injection Sclerotherapy for Gastroesophageal Varices
Published on: August 1, 2025
A simple noninvasive score predicts gastroesophageal varices in patients with chronic viral hepatitis
Ivan Gentile1, Chiara Viola, Maria Graf
1Department of Public Medicine and Social Security, Section of Infectious Diseases, University of Naples Federico II, Naples, Italy. ivan.gentile@alice.it

Insights
Patients with chronic viral hepatitis and a low-risk score (based on age, platelets, and liver enzymes) are unlikely to have large gastroesophageal varices and may avoid upper endoscopy screening.
Area of Science:
- Hepatology
- Gastroenterology
- Internal Medicine
Background:
- Guidelines recommend upper endoscopic screening for gastroesophageal varices in cirrhotic patients.
- Distinguishing cirrhosis from chronic hepatitis can be challenging.
Purpose of the Study:
- To identify low-risk patients with chronic liver disease who can safely forgo upper endoscopy.
- To reduce unnecessary endoscopic procedures irrespective of cirrhosis diagnosis.
Main Methods:
- Evaluated 13 nonendoscopic variables in 254 patients with hepatitis B or C.
- Utilized logistic regression to identify predictors of esophagogastric varices.
- Developed a risk score based on age, platelet count, and AST/ALT ratio.
Main Results:
- 30.3% of patients had varices; 12.2% had large varices.
- Independent predictors of varices included age >50, platelet count <150,000, albumin <3.6, and AST/ALT ratio >1.
- A score <2 (based on age, platelets, AST/ALT ratio) identified patients with only small varices (3.2%).
Conclusions:
- Patients with chronic viral hepatitis and a risk score <2 are unlikely to have large varices.
- Upper endoscopy can be safely avoided in approximately 50% of patients with this low-risk score.
- This approach can significantly reduce the need for endoscopic screening in this population.
Background:
Guidelines recommend upper endoscopic screening of cirrhotic patients for gastroesophageal varices. Cirrhosis is not always distinguishable from chronic hepatitis.
Goals:
To identify low-risk patients who can be spared upper endoscopy irrespective of a diagnosis of cirrhosis.
Study:
We evaluated 13 nonendoscopic variables as predictors of esophagogastric varices in 254 patients with hepatitis B or hepatitis C-related chronic liver disease who underwent upper endoscopy.
Results:
Any size varices occurred in 30.3% (77/254), and large varices in 12.2% of patients (31/254). Age >50 years [odds ratio (OR): 11.29; 95% confidence interval (CI): 2.33-54.67], platelet count <150,000/mmc (OR: 4.40; 95% CI: 1.85-10.45), albumin <3.6 g/dL (OR: 2.99; 95% CI: 1.31-6.79), and aspartate aminotransferase/alanine aminotransferase ratio >1 (OR: 2.83; 95% CI: 1.26-6.34) independently predicted varices by logistic regression. Using a score based on age >50 years, platelets <150,000/mmc, and aspartate aminotransferase/alanine aminotransferase ratio >1 (1 point/predictor), only 3.2% of patients with a score <2 had varices, all small.
Conclusions:
Patients with chronic viral hepatitis and a score <2 need not undergo upper endoscopy, as they are unlikely to have large varices. Because about 50% of our patients had this score, 50% of upper endoscopies may be safely avoided.

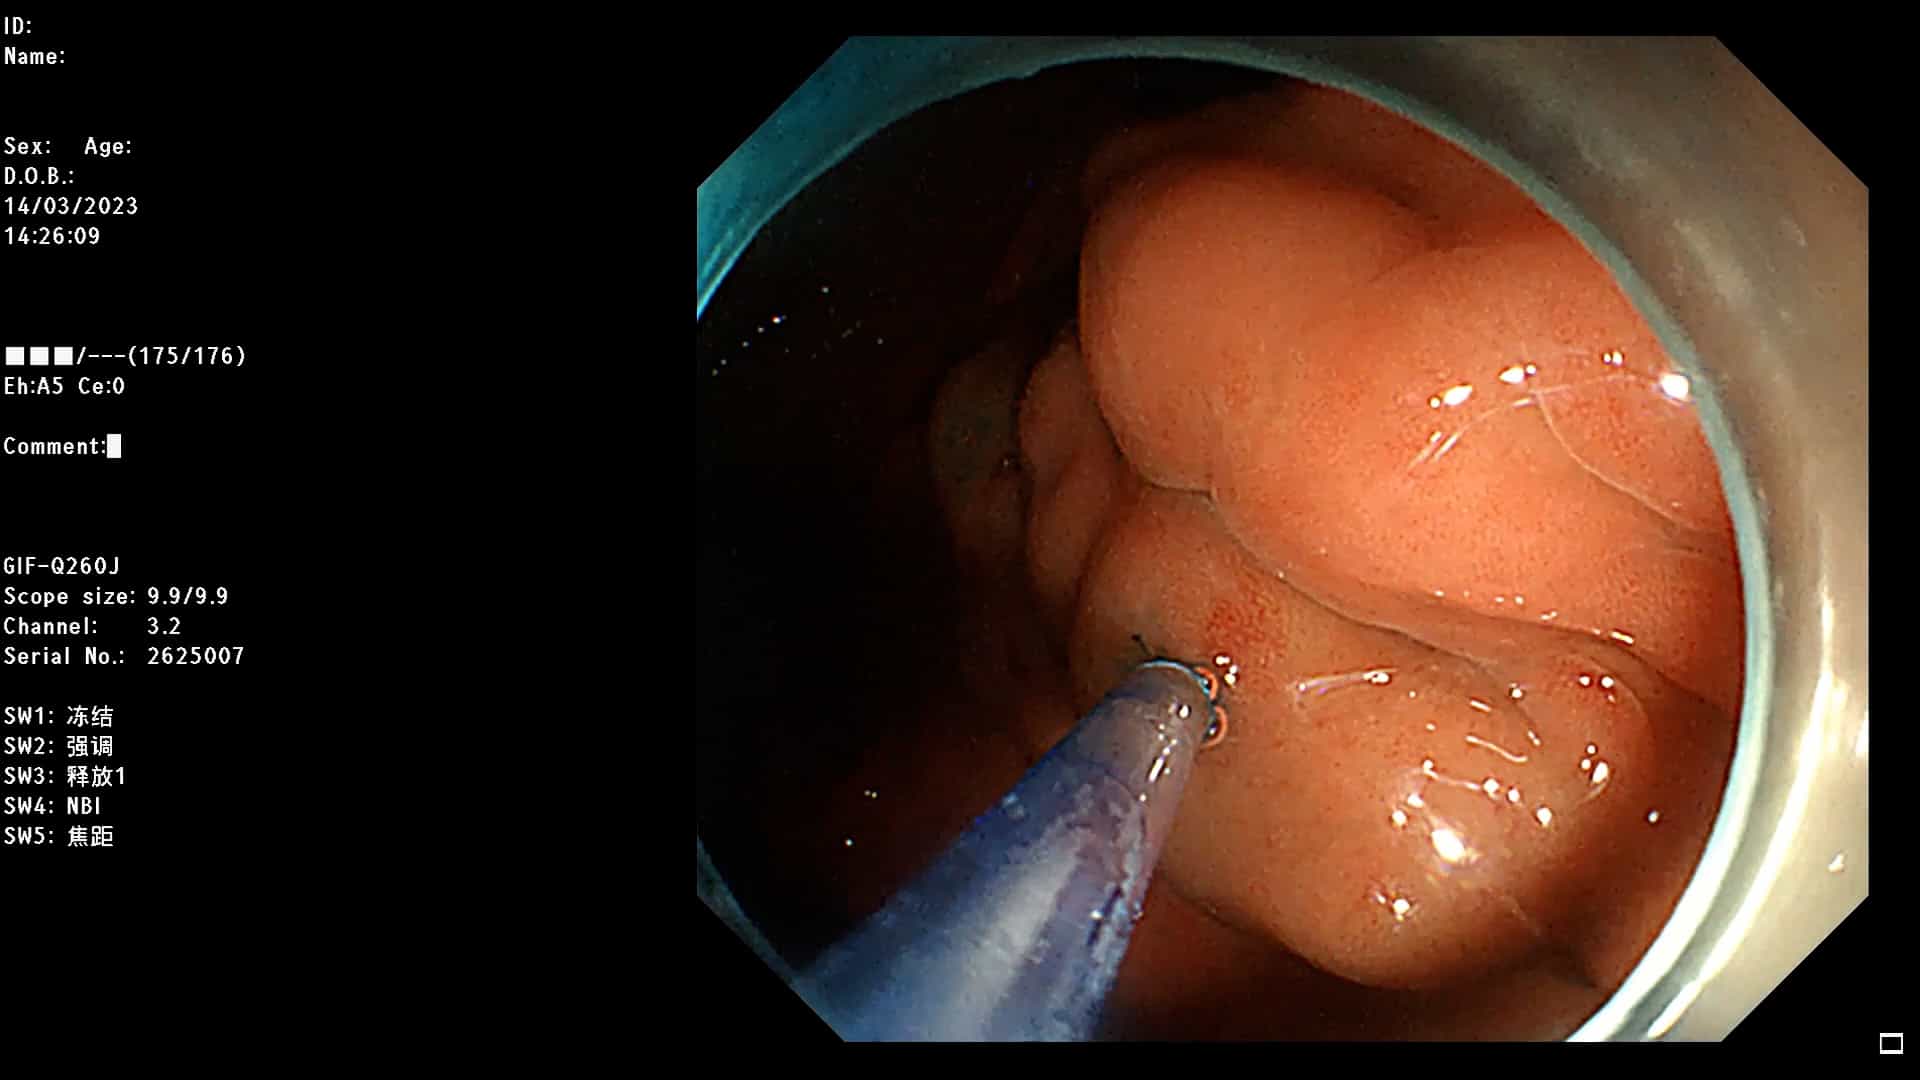
Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:24
Esophageal Varices-I: Introduction
 01:25
Ultrasound II: Endoscopic Ultrasound and FibroScan
Endoscopic Ultrasound (EUS):
 01:28
Viral Hepatitis I: Introduction
 01:24
Cirrhosis II: Pathophysiology
 01:26
Diseases of the Liver and Gallbladder
Cirrhosis is characterized by the scarring of hepatic lobules in the liver, which are replaced by fibrous tissue, affecting the liver's normal functioning. NAFLD, on the other hand, is caused by an excessive build-up of fat in the liver, not related to...