Related Experiment Video
Updated: Jul 4, 2026


Retroperitoneal Laparoscopic Debridement and Drainage for Pancreatic Abscess
Published on: March 15, 2024
Abdominal compartment syndrome in patients with severe acute pancreatitis in early stage
Hong Chen1, Fei Li, Jia-Bang Sun
1Department of General Surgery, Xuan Wu Hospital of Capital Medical University, Beijing 100053, China. chenhong@medmail.com.cn

Aim:
To study retrospectively the influence of intra-abdominal hypertension (IAH) and abdominal compartment syndrome (ACS) in patients with early acute pancreatitis (AP) (during the first week after admission) on physiological functions, and the association of the presence of IAH/ACS and outcome.
Methods:
Patients (n = 74) with AP recruited in this study were divided into two groups according to intra-abdominal pressure (IAP) determined by indirect measurement using the transvesical route via Foley bladder catheter during the first week after admission. Patients (n = 44) with IAP >or= 12 mmHg were assigned in IAH group, and the remaining patients (n = 30) with IAP < 12 mmHg in normal IAP group. For analysis of the influence of IAH/ACS on organ function and outcome, the physiological parameters and the occurrence of organ dysfunction during intensive care unit (ICU) stay were recorded, as were the incidences of pancreatic infection and in-hospital mortality.
Results:
IAH within the first week after admission was found in 44 patients (59.46%). Although the APACHE II scores on admission and the Ranson scores within 48 h after hospitalization were elevated in IAH patients in early stage, they did not show the statistically significant differences from patients with normal IAP within a week after admission (16.18 +/- 3.90 vs 15.70 +/- 4.25, P = 0.616; 3.70 +/- 0.93 vs 3.47 +/- 0.94, P = 0.285, respectively). ACS in early AP was recorded in 20 patients (27.03%). During any 24-h period of the first week after admission, the recorded mean IAP correlated significantly with the Marshall score calculated at the same time interval in IAH group (r = 0.635, P < 0.001). Although ACS patients had obvious amelioration in physiological variables within 24 h after decompression, the incidences of pancreatitic infection, septic shock, multiple organ dysfunction syndrome (MODS) and death in the patients with ACS were significantly higher than that in other patients without ACS (pancreatitic infection: 60.0% vs 7.4%, P < 0.001; septic shock: 70.0% vs 11.1%, P < 0.001; MODS: 90.0% vs 31.5%, P < 0.001; mortality: 75.0% vs 3.7%, P < 0.001).
Conclusion:
IAH/ACS is a frequent finding in patients admitted to the ICU because of AP. Patients with IAP at approximately 10-12 mmHg and early signs of changes in physiologic variables should be seriously considered for urgent decompression to improve survival.
More Related Videos
 06:05
Enema of Traditional Chinese Medicine for Patients with Severe Acute Pancreatitis
Published on: January 27, 2023
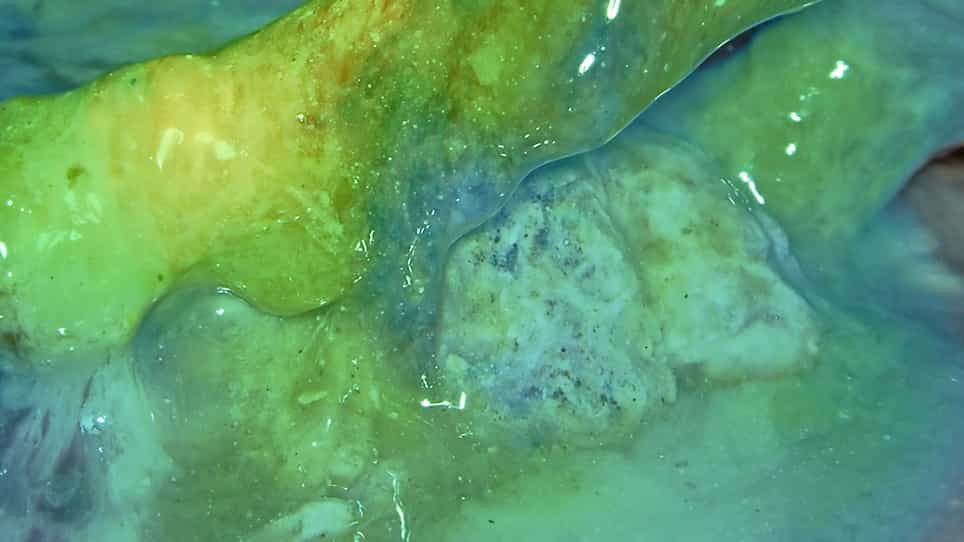 04:01
Indocyanine Green-Guided Intraoperative Imaging to Facilitate Video-Assisted Retroperitoneal Debridement for Treating Acute Necrotizing Pancreatitis
Published on: September 8, 2022
Related Concept Videos
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:25
Acute Pancreatitis I: Introduction
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:21
Acute Pancreatitis II: Pathophysiology
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
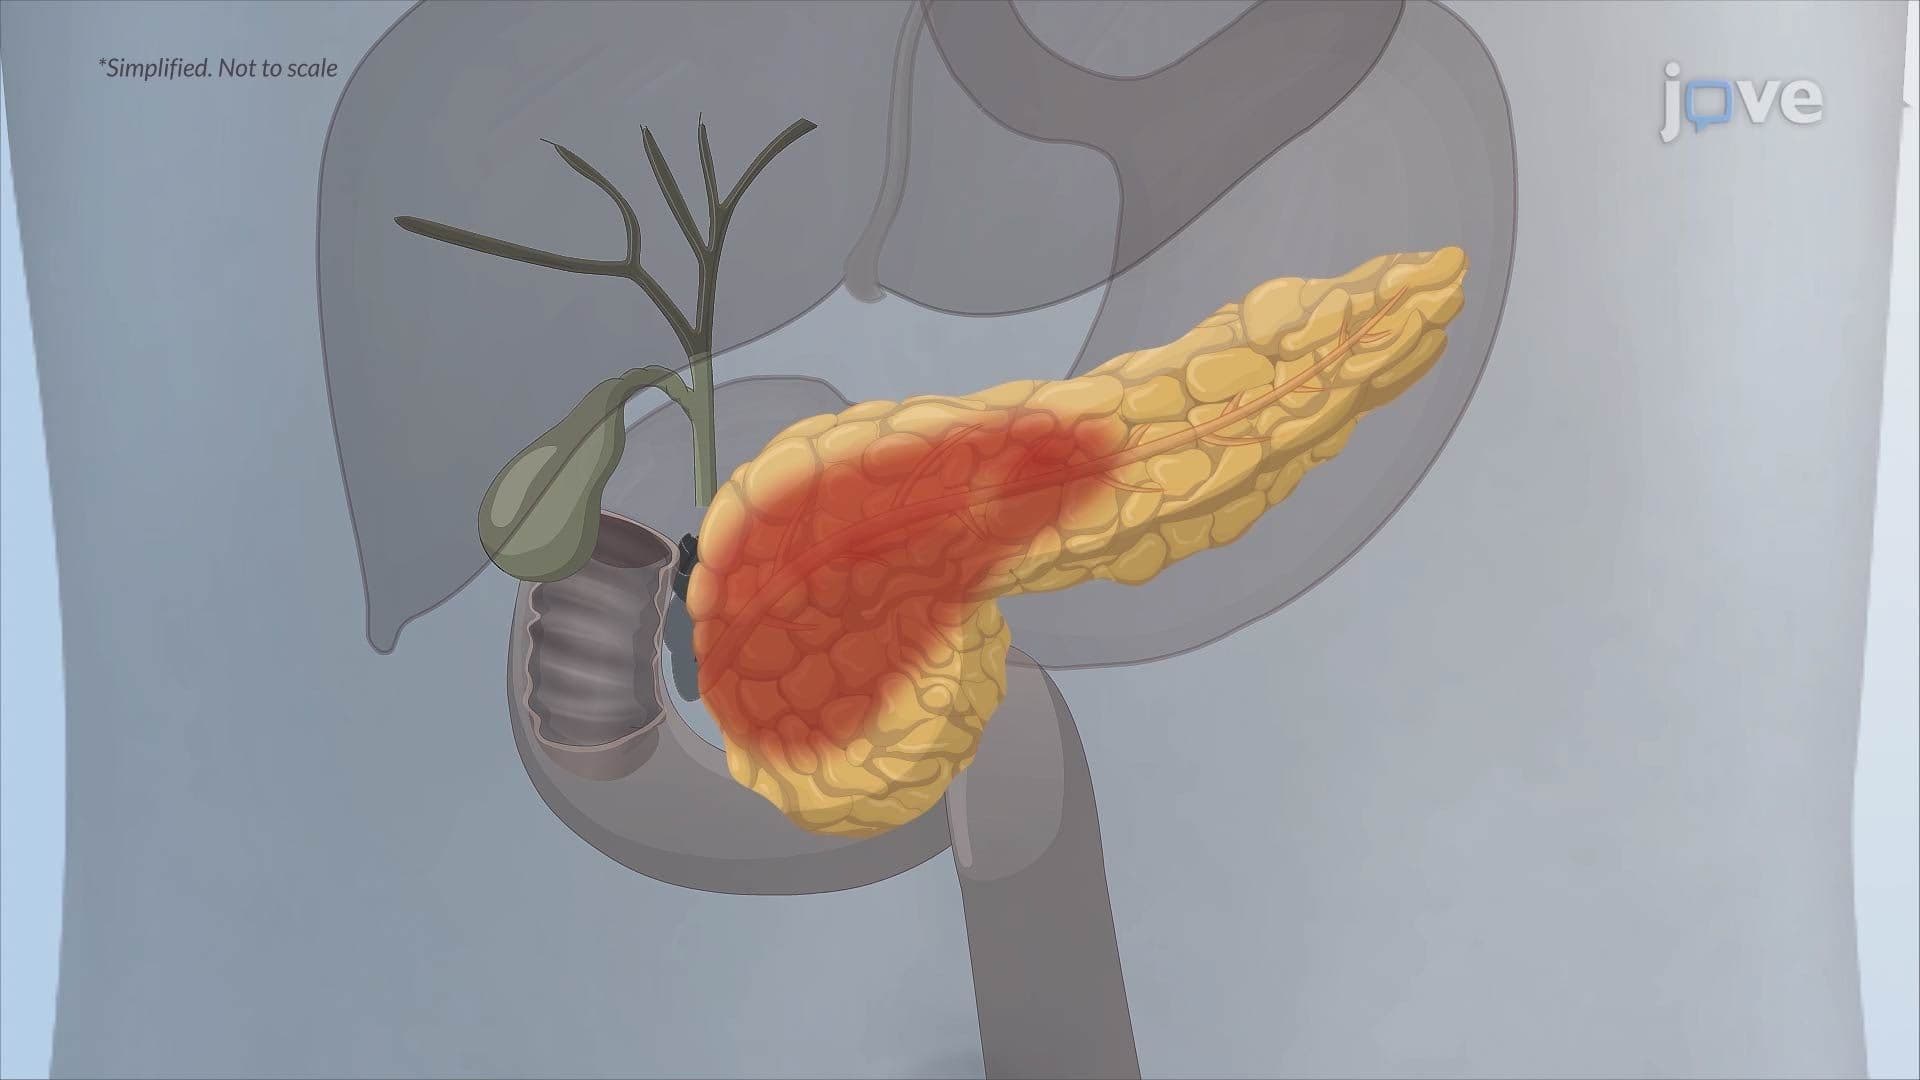 01:25
Chronic Pancreatitis I: Introduction