Related Experiment Video
Updated: Jul 4, 2026
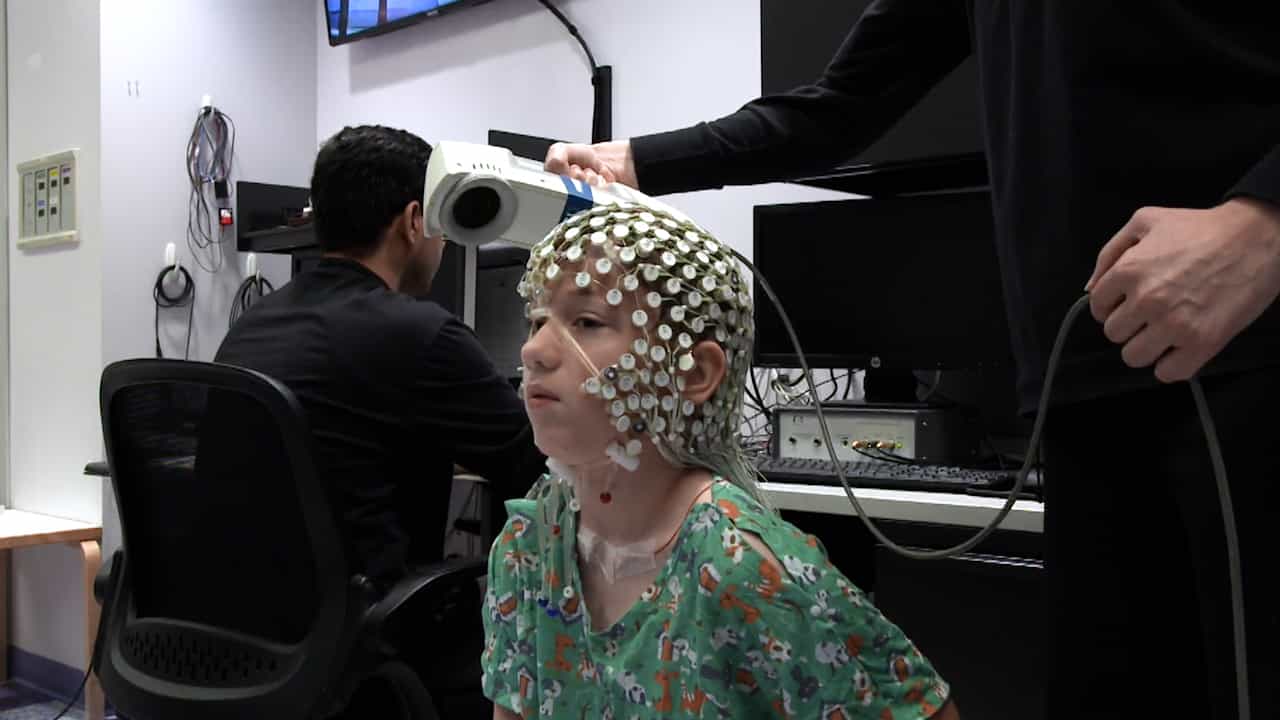
Electromagnetic Source Imaging in Presurgical Evaluation of Children with Drug-Resistant Epilepsy
Published on: September 20, 2024
When to start drug treatment for childhood epilepsy: the clinical-epidemiological evidence
Willem F M Arts1, Ada T Geerts
1Department of Paediatric Neurology, Erasmus Medical Center, Sophia Children's Hospital, P.O. Box 2060, 3000 CB Rotterdam, The Netherlands. w.f.m.arts@erasmusmc.nl

Introduction:
Many data on the course and prognosis after provoked and unprovoked single and multiple seizures in childhood have been collected in the past decennia by prospective, large-scale, long-term observational cohort studies. These data may serve to guide treatment decisions and help to design controlled trials investigating treatment strategies in childhood epilepsy.
Methods:
The results of the Dutch study of epilepsy in childhood will be compared with those of other studies. We will also discuss the potential consequences of these results for the "why" and "when" of the decision to start treatment.
Results:
Recurrence after a solitary unprovoked seizure in childhood is about 50%. Those with a recurrence have a similar outcome of their epilepsy compared to children presenting with multiple seizures, regardless whether they were treated after the first seizure or not. This argues in favour of postponing anti-epileptic drug (AED) treatment until at least a second seizure has occurred. After an unprovoked status epilepticus (SE), later outcome is not worse than after presentation with a short seizure. Therefore, long-term AED treatment after a single unprovoked SE may not be necessary either. The same holds true for children presenting with a short (less than one week) burst of unprovoked seizures. One quarter of them do not have recurrences and the final prognosis of children with recurrences does again not differ from the prognosis of the entire cohort. Findings in new-onset epilepsy further indicate that AED treatment can be safely omitted or at least postponed in about 15%, especially those with only a small number of seizures before presentation, those with benign partial epilepsy and those with sporadic generalised tonic-clonic seizures. On the reverse side, three considerations might lead to the decision to start early and aggressive treatment: the dangers of the seizures, the chance of intractability and the possibility of intellectual decline caused by recurrent seizures or epileptic activity. In idiopathic generalised absence epilepsy, the risks of accidents and learning problems indeed prompt early AED treatment. A self-propagating mechanism of seizures promoting the occurrence of more seizures, in the end causing intractable epilepsy (Gowers), occurs only rarely. Real intractability is seen in only 5-15% of the children with new-onset epilepsy. The chance of intractability is increased by variables like symptomatic aetiology, localisation-related epilepsy, and an early unfavourable course. Landau-Kleffner or continuous spikes and waves during sleep (CSWS) syndrome cause cognitive decline and syndromes like West, Lennox-Gastaut or Dravet's induce both psychomotor regression and intractability. In such cases, early aggressive treatment is indicated, including early consideration of the ketogenic diet, immunotherapy, vagus nerve stimulation and, if possible, referral for epilepsy surgery.
Conclusions:
Omitting or postponing treatment after a solitary seizure, an unprovoked SE, a single burst of seizures or multiple infrequent seizures usually does not worsen the prognosis. A poor prognosis and the consequent indication for early and aggressive treatment are dependent mainly upon the presence of variables like symptomatic aetiology, certain epilepsy types and syndromes, and the early evolution of the epilepsy in that particular child. Intellectual decline caused by seizures or epilepsy is rare and may be confined to certain specific and readily recognizable syndromes.


Related Concept Videos
 01:24
Epilepsy and Seizures: Overview
Various factors can trigger epilepsy, including genetic factors, brain damage, metabolic causes, and unknown etiology. Diagnosis of epilepsy involves electroencephalography (EEG), which...
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:22
Epilepsy ll: Types
 01:20
Antiepileptic Drugs: Potassium Channel Activators
Ezogabine has gained approval as an adjunctive treatment...
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:11
Clinical Trials: Overview