Related Experiment Video
Updated: Jul 3, 2026
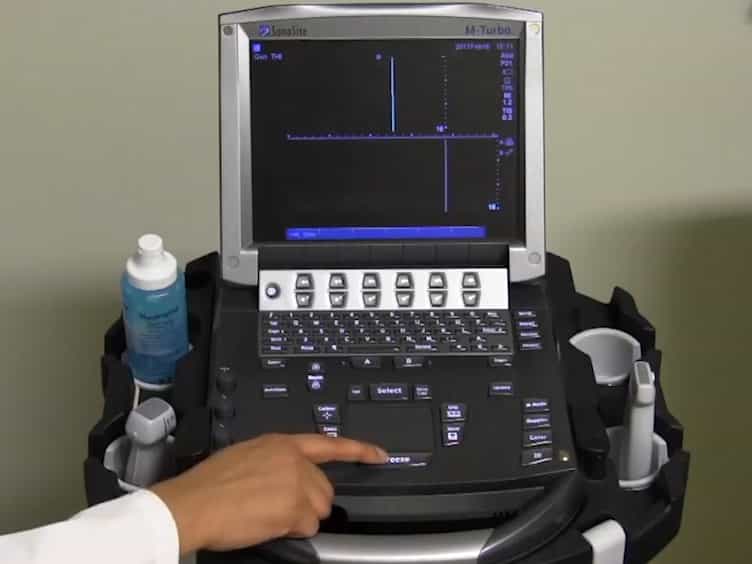

Bedside Ultrasound for Guiding Fluid Removal in Patients with Pulmonary Edema: The Reverse-FALLS Protocol
Published on: July 28, 2018
Outcomes of volume-overloaded cardiovascular patients treated with ultrafiltration
Brian E Jaski1, Andrew Romeo, Bryan Ortiz
1San Diego Cardiac Center, Sharp Memorial Hospital, San Diego, California 92123, USA.

Background:
Ultrafiltration (UF) can rapidly and predictably remove extracellular and intravascular fluid volume. To date, assessment of UF in patients with cardiovascular disease has been confined to short- and medium-term studies in patients with a principal diagnosis of acute heart failure.
Methods:
In-hospital and long-term outcomes were reviewed from consecutive patients with cardiovascular disorders and recognized pulmonary and systemic volume overload treated with a simplified UF system with the capability for peripheral venovenous access. Trained abstractors reviewed both paper and electronic medical records. Patients with a principal diagnosis of heart failure versus other primary hospital discharge diagnoses were identified according to International Classification of Diseases, 9th Revision standards by independent coders.
Results:
For a period of 43 months, 100 patients (76 male/24 female, 65 +/- 14.0 years of age, systolic dysfunction 64%) were treated with UF during 130 hospitalizations. Baseline systolic blood pressure was 119 +/- 23 mm Hg. Before UF, 53% were receiving intravenous vasoactive therapy. By using UF, 7.1 +/- 3.9 L of ultrafiltrate were removed during 2.0 +/- 1.2 treatments per hospitalization. Baseline creatinine was 1.8 +/- 0.8 and 1.9 +/- 1.2 (not significant) at discharge. Of the 15 in-hospital deaths, 14 occurred during the initial hospitalization. Left ventricular dysfunction was related to 13 (87%) of the 15 deaths; no deaths were related to UF use. In hospitalizations with a principal diagnosis of heart failure (n = 79), in-hospital mortality was 7.6% compared with an ADHERE risk tree estimated mortality of 7.5%. Multivariate logistic regression identified a trend for decreased systolic blood pressure to predict patient initial hospitalization mortality (P = .06). Kaplan-Meier survivals for all patients were 71% at 1 year and 67% at 2 years. Cox regression found decreased systolic blood pressure as a predictor of long-term mortality (P = .025). Total volume of ultrafiltrate removed, ejection fraction, history of coronary artery disease, creatinine clearance, gender, age, and principal diagnosis of heart failure were not significantly associated with long-term mortality.
Conclusion:
This series extends the spectrum of patients previously reported to be treated with UF. Despite marked volume overload, UF-treated patients with a principal diagnosis of heart failure had inpatient outcomes similar to the ADHERE registry. UF should be considered for a broad range of patients who present with volume overload.
Related Concept Videos
 01:22
Heart Failure VI: Adjunct Therapies
 01:22
Heart Failure Drugs: Diuretics
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:30
Continuous Renal Replacement Therapy
 01:30
Heart Failure V: Medical Management
 01:25
Extracorporeal Removal of Drugs: Hemoperfusion and Hemofiltration