Related Experiment Video
Updated: Jul 3, 2026


Benefits of Cardiac Resynchronization Therapy in an Asynchronous Heart Failure Model Induced by Left Bundle Branch Ablation and Rapid Pacing
Published on: December 11, 2017
Resynchronization: what if the left ventricular lead cannot reach the lateral or posterolateral wall?
Christophe D'Ivernois1, Jérôme Lesage, Patrick Blanc
1Service de Cardiologie, Hôpital Universitaire Dupuytren, Limoges, France. christophe.divernois@chu-limoges.fr

Insights
Cardiac resynchronization therapy (CRT) shows high response rates even when the left ventricular (LV) lead is implanted in the anterior wall. Anterior LV lead placement is a viable alternative if the recommended posterolateral site is inaccessible.
Area of Science:
- Cardiology
- Medical Devices
- Heart Failure Management
Background:
- The optimal left ventricular (LV) lead placement for cardiac resynchronization therapy (CRT) is typically the lateral or posterolateral wall.
- Implantation at the recommended site is not always achievable.
Purpose of the Study:
- To compare clinical response to CRT based on LV lead implantation site.
- To evaluate outcomes when LV leads are placed at the lateral/posterolateral wall versus anterior/anterolateral wall.
Main Methods:
- Prospective follow-up of 77 patients implanted with CRT devices for 6 months.
- Patients categorized into Group A (lateral/posterolateral LV lead) and Group B (anterior/anterolateral LV lead).
- Responders defined by survival, improved NYHA class, and absence of heart failure hospitalization.
Main Results:
- Group A (n=54) had a 69% responder rate, with 7 deaths.
- Group B (n=23) achieved a 96% responder rate, with no deaths.
- Responder rate was not inferior in Group B compared to Group A.
Conclusions:
- Implanting the LV lead at the anterior or anterolateral wall yields a comparable responder rate to the recommended posterolateral site.
- Anterior LV lead placement is a reasonable alternative when posterolateral implantation fails.
- Further research is needed to validate these findings.
Background:
The recommended left ventricular (LV) lead position for cardiac resynchronization therapy (CRT) is at the lateral or posterolateral wall. However, LV leads cannot always be implanted at this site. The objective of our study was to compare the clinical response to CRT when the LV lead could be implanted or not at the lateral or posterolateral wall.
Methods:
In consecutive patients implanted with a CRT device, we documented the final position achieved by the tip of the LV lead in the left anterior oblique projection. Patients were prospectively followed for 6 months after implantation. They were defined as responders if they were alive, had gained 1 New York Heart Association (NYHA) functional class, and had not been hospitalized for heart failure.
Results:
The study population consisted of 77 patients (56 men, 71 +/- 10 years, 62 NYHA class III, 15 NYHA class IV). The LV lead was implanted at the lateral or posterolateral wall in 54 patients (group A) and at the anterior or anterolateral wall in 23 patients (group B). At 6 months, seven patients (9%) died (all in group A). There were 37 responders (69%) in group A as compared to 22 (96%) in group B.
Conclusions:
The responder rate was not inferior when the LV lead was implanted at the anterior or anterolateral wall. Thus, in case of failed implantation at the lateral or posterolateral wall, positioning the LV lead in a more anterior location appears to be a reasonable alternative. Further studies are required to confirm these findings.
More Related Videos
 06:57
Ablation of Ischemic Ventricular Tachycardia Using a Multipolar Catheter and 3-dimensional Mapping System for High-density Electro-anatomical Reconstruction
Published on: January 31, 2019
 10:17
Real-Time Cardiac Mapping with a Noninvasive Imageless Electrocardiographic Imaging System
Published on: April 11, 2025
Related Concept Videos
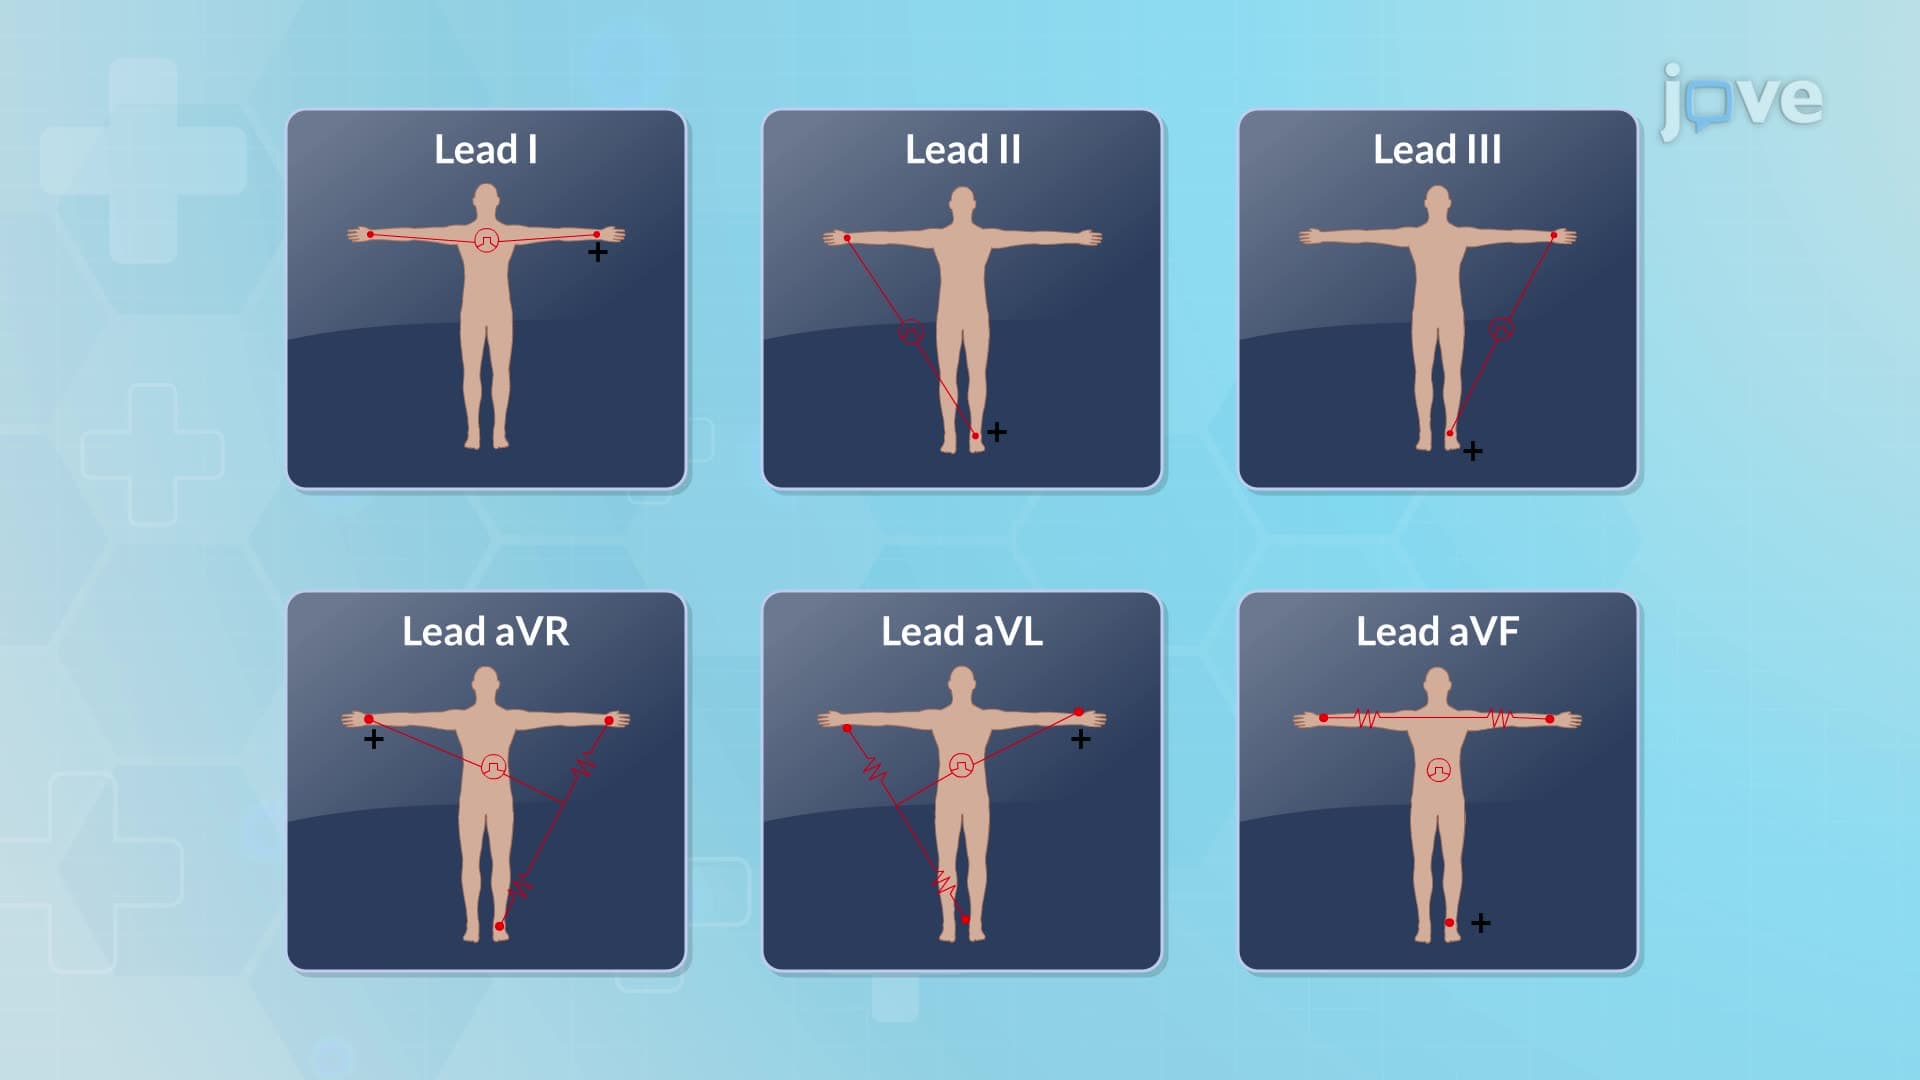 01:28
Electrocardiogram Fundamentals
An electrocardiogram (ECG) is a diagnostic tool for identifying cardiac conditions such as arrhythmias, conduction abnormalities, and myocardial ischemia.
Definition
An electrocardiogram (ECG) visualizes the heart's electrical activity by tracing the electrical movement associated with each heartbeat on a graph or monitor. As the heart beats, an electrical wave passes through it, correlating with the cardiac cycle events.
Parts of an ECG
An ECG utilizes electrodes on the skin to...
 01:24
Cardiac Catheterization III: Left Heart Catheterization