Related Experiment Video
Updated: Jul 2, 2026
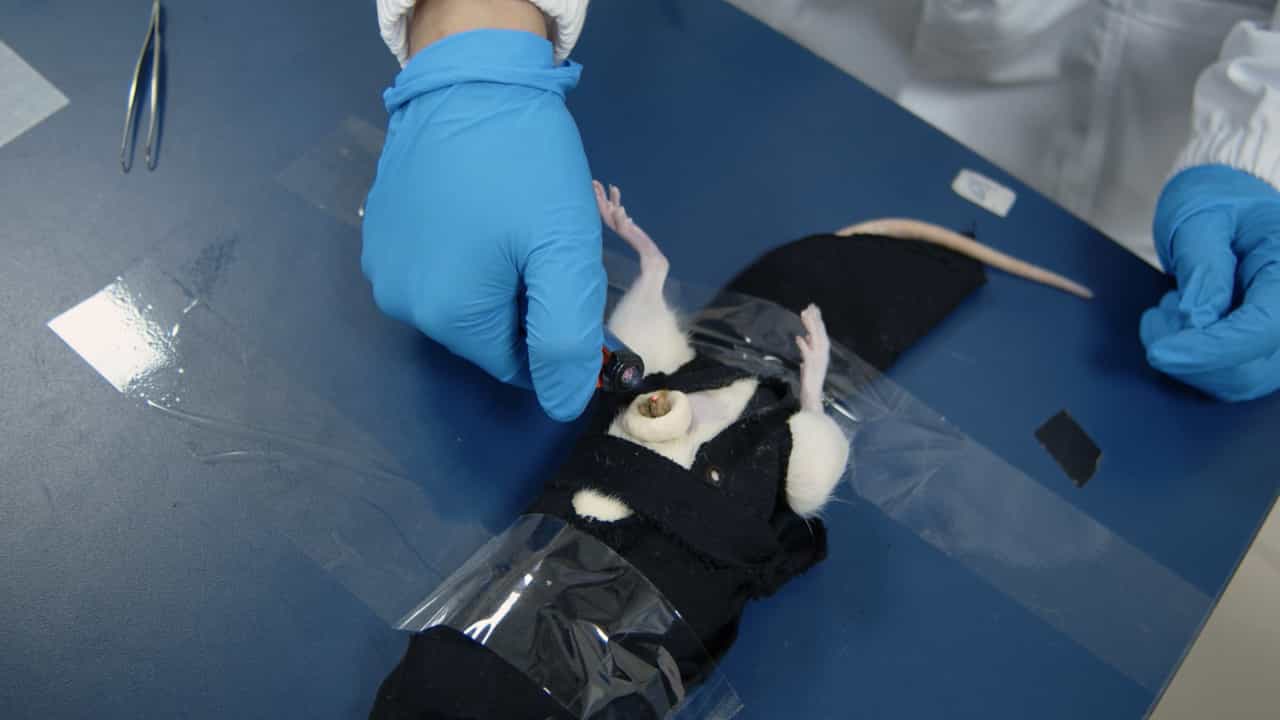

Herbs-Partitioned Moxibustion on the Navel in a Rat Model of Primary Dysmenorrhea with Cold Coagulation and Blood Stasis
Published on: October 4, 2024
Dysmenorrhea: contemporary perspectives
Brittany Bettendorf1, Sophie Shay, Frank Tu
1Medical College of Wisconsin, Milwaukee, Wisconsin, USA.

Abstract:
Dysmenorrhea affects up to 80% of reproductive age women, in many cases causing sufficient pain to dramatically affect social and occupational roles. The prevalence varies across ethnic groups, which in part may reflect varying cultural attitudes toward women and menstruation. Key identified risk factors for dysmenorrhea include age of menarche, body mass, dietary habits, associated uterine bleeding disorders, comorbid pelvic pathology, and psychosocial problems. While much of the focus on the pathogenesis of dysmenorrhea has focused on aberrant inflammatory mediators in the uterine environment, recent studies using experimental quantitative sensory testing suggest central processing of pain is enhanced in many of these women as well, similar to both irritable bowel syndrome and painful bladder syndrome, which are closely related visceral pain disorders. The mainstays of treatment include nonsteroidal antiinflammatories and combined oral contraceptives; although only the former has extensive level I evidence to support its efficacy. Surgical treatments (presacral neurectomy or uterosacral nerve ablation) appear to be beneficial in a subset of women, but are associated with small, but serious, risks of visceral or vascular injury. Complementary and alternative treatments such as vitamin B1 and magnesium supplementation have not been studied as extensively but show some promise as well. In particular, treatments targeting central aberrations in pain processing, as used in chronic pain management, may prove beneficial as a more multidimensional approach to this common malady is accepted in our field.

Related Concept Videos
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:18
Menses Phase
When fertilization does not occur, the corpus luteum deteriorates, causing a significant drop in the levels of estrogen and progesterone in the body. This hormonal decrease triggers the release of prostaglandins, which cause the uterine...
 01:24
Disorders of the Female Reproductive System
 01:30
Irritable Bowel Syndrome III: Medical and Nursing Management
 01:25
Analgesia and Pain Management
 01:17
Drugs for Treatment of Diarrhea-Predominant IBS
Two specific drugs used in the treatment are alosetron (Lotronex) and eluxadoline (Viberzi). Alosetron, a 5-HT3 antagonist, works by slowing the movement of stools in the gut, reducing bowel...