Related Experiment Video
Updated: Jul 2, 2026
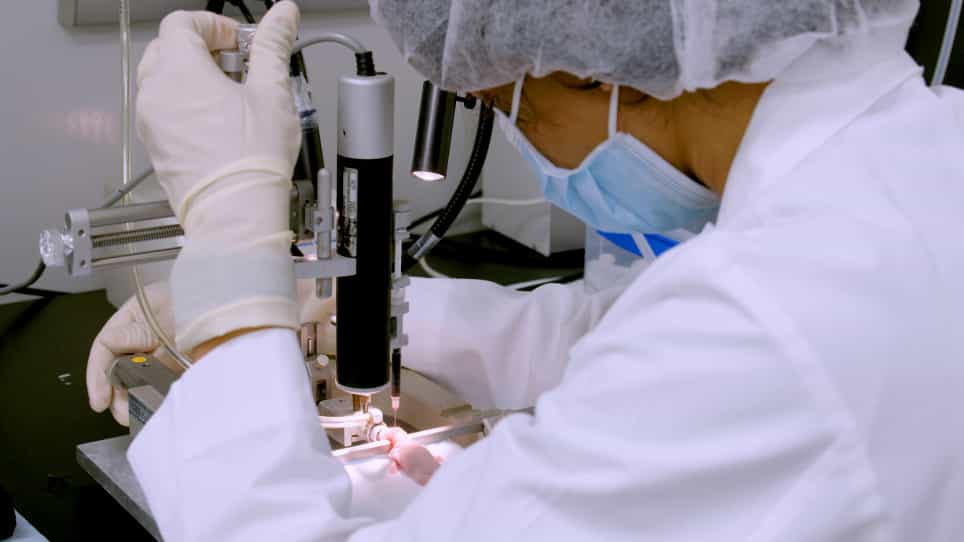

Modeling Neonatal Intraventricular Hemorrhage Through Intraventricular Injection of Hemoglobin
Published on: August 25, 2022
Hemoglobin-based oxygen carrying compound-201 as salvage therapy for severe neuro- and polytrauma (Injury Severity
Michael Dudkiewicz1, Tracey A Harpaul, Kenneth G Proctor
1Dewitt-Daughtry Family Department of Surgery, Division of Trauma, University of Miami Miller School of Medicine, Miami, FL, USA.

Objective:
A prehospital trial in trauma patients has been proposed to evaluate Hemopure (hemoglobin glutamer-250 [bovine], hemoglobin-based oxygen carrying compound [HBOC]-201, Biopure). We tested the hypothesis that HBOC-201 would improve cerebrovascular resuscitation in a unique polytrauma model.
Design:
Prospective, randomized, blinded animal study.
Subjects:
Thirty-two anesthetized swine (42 +/- 1 kg).
Interventions:
Blunt trauma to the head, right chest, and bilateral femurs (Injury Severity Score = 27-41) with captive bolt guns was followed by hypoventilation. Resuscitation was divided into phases to simulate conventional treatment in the prehospital, emergency room, and early intensive care unit. For 30-60 mins postinjury, 500 mL of either normal saline (control, n = 14) or HBOC-201 (n = 14) was administered. All received similar care thereafter. For 60-120 mins, normal saline maintained systolic arterial pressure >100 mm Hg and heart rate <100 beats/min plus mannitol (250 mg/kg) for intracranial hypertension. For 120-480 mins, phenylephrine, normal saline, and dextrose were administered to maintain cerebral perfusion pressure >70 mm Hg, filling pressure >12 mm Hg, and plasma glucose >60 mg%, respectively. Two formulations of HBOC-201 (average MW = 250 kDa) were tested: one with <3% 65 kDa tetramers (n = 7) and the other with <0.3% 65 kDa tetramers (n = 7).
Measurements And Main Results:
Injury severity is reflected by the death of 2 of 32 swine within 30 mins. In survivors (n = 30), systolic arterial pressure was 83 +/- 6 mm Hg, heart rate was 115 +/- 5 beats/min, and lactate was 5.8 +/- 0.4 mM. Intracranial pressure rose from 8 +/- 1 to 18 +/- 1 mm Hg and brain tissue PO2 fell from 17 +/- 1 to 2 +/- 1 mm Hg. Without immediate resuscitation, death occurred within 60 mins (n = 2). With normal saline resuscitation (n = 14), systemic hemodynamics, mixed venous oxygen, renal oxygen, portal oxygen, and muscle oxygen corrected but there were four deaths (two at 45 mins, one at 100 mins, and one at 200 mins). Cerebral perfusion pressure was not restored until mannitol and pressor therapy were initiated at 120 mins. In contrast, with HBOC-201 at 30 mins (n = 14), systolic arterial pressure and cerebral perfusion pressure corrected immediately (both p < 0.05) and there were no deaths (p = 0.0978). After 8 hrs, in both groups, cerebral perfusion pressure, systolic arterial pressure, and heart rate were stable; peripheral oxygen saturations were near normal; lactate was cleared; urine output was adequate. However, with HBOC-201, pressor and fluid requirements were reduced by half, which improved intracranial pressure and brain tissue PO2 (all p < 0.05 vs. control). Reducing tetramer content had no significant effect on the actions of HBOC-201.
Conclusions:
1) A single bolus of HBOC-201 at initial resuscitation rapidly restored cerebral perfusion pressure and stabilized hemodynamics with improved intracranial pressure and brain oxygen for the first 8 hrs; and 2) HBOC-201 could be an effective salvage therapy after severe neurotrauma or as a temporizing measure during prolonged transport of a polytrauma patient.

Related Concept Videos
 01:27
Oxygen Transport in the Blood
 01:24
Hemoglobin
When all four heme groups are bound to oxygen, the resulting molecule is called oxyhemoglobin. As a result, arterial blood...
 01:16
Treatment for Pulmonary Arterial Hypertension: Oxygen Therapy for Respiratory Failure
Oxygen therapy is vital in increasing and maintaining blood oxygen levels in PAH patients. As a result, it aids in reducing fatigue, improving...
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History: