Related Experiment Video
Updated: Jun 30, 2026
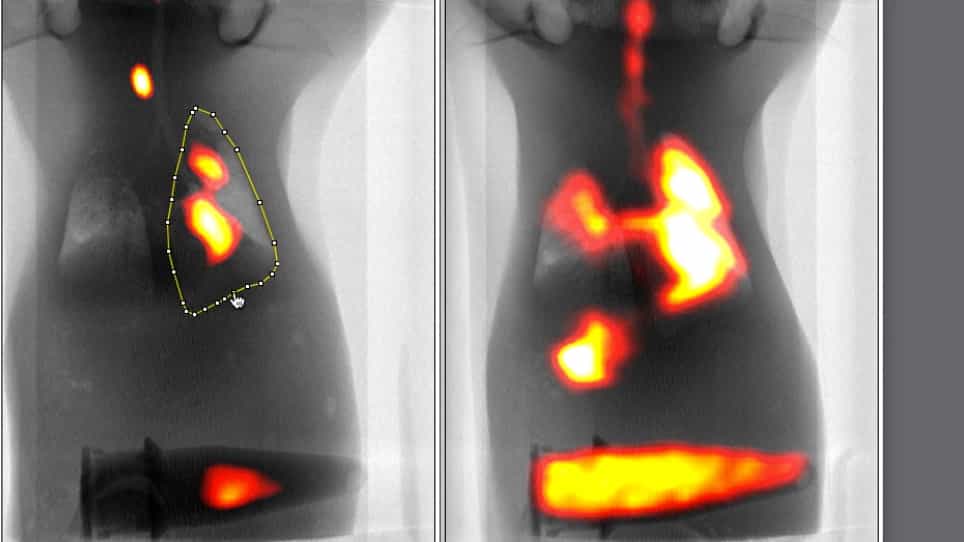

In vivo Evaluation of Mucociliary Clearance in Mice
Published on: December 18, 2020
High-resolution CT findings of Mycobacterium avium-intracellulare complex pulmonary disease: correlation with
Jong Woon Song1, Won-Jung Koh, Kyung Soo Lee
1Department of Radiology and Center for Imaging Science, Sungkyunkwan University School of Medicine, Samsung Medical Center, 50, Ilwon-Dong, Kangnam-Ku, Seoul 135-710, Korea.

Objective:
The purpose of our study was to analyze the high-resolution CT findings of the nodular bronchiectatic form of Mycobacterium avium-intracellulare complex (MAC) pulmonary disease and to correlate the extent of high-resolution CT findings with pulmonary function test (PFT) results.
Materials And Methods:
From January 2005 through December 2005, we identified 47 patients (mean age, 58 +/- 13 years; age range, 24-72 years; male-female ratio, 11:36) with the nodular bronchiectatic form of MAC pulmonary disease who underwent both high-resolution CT and PFTs. High-resolution CT findings were reviewed retrospectively in terms of the presence and extent of bronchiectasis, cellular or inflammatory bronchiolitis (centrilobular small nodules and tree-in-bud signs), cavity, nodule, and other findings. The extent of the abnormalities seen on high-resolution CT was scored by modifying the cystic fibrosis scoring system proposed by Helbich and coworkers. The scores were correlated with PFT results using Spearman's correlation coefficient.
Results:
On high-resolution CT, the three most frequently observed patterns of parenchymal abnormalities were, in decreasing order of frequency, cellular bronchiolitis (n = 47, 100%), bronchiectasis (n = 46, 98%), and consolidation (n = 27, 57%). The total CT score showed a significant correlation with the residual volume-total lung capacity (RV/TLC) ratio (r = 0.572, p < 0.001), forced expiratory volume in 1 second (FEV(1)) value (r = -0.426, p = 0.003), forced vital capacity (FVC) value (r = -0.360, p = 0.013), peak expiratory flow value (r = -0.352, p = 0.015), and peak expiratory flow between 25% and 75% of the forced vital capacity (FEF(25-75%)) (r = -0.289, p = 0.049).
Conclusion:
CT scoring of pulmonary abnormalities correlates with measures of functional impairment in patients with MAC pulmonary disease.
Related Concept Videos
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:25
Pulmonary Function Tests
Pulmonary Function Tests are crucial diagnostic tools for assessing respiratory function, particularly in patients with chronic respiratory disorders. They comprehensively evaluate lung volumes, ventilatory function, breathing mechanics, diffusion, and gas exchange. These tests help diagnose pulmonary diseases and play a significant role in monitoring disease progression, evaluating disability, and assessing response to therapy.
PFTs involve using a spirometer, a...
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...