Laparoscopic pyeloplasty for repair of pelvi-ureteric junction obstruction in children
Related Experiment Video
Updated: Jun 28, 2026
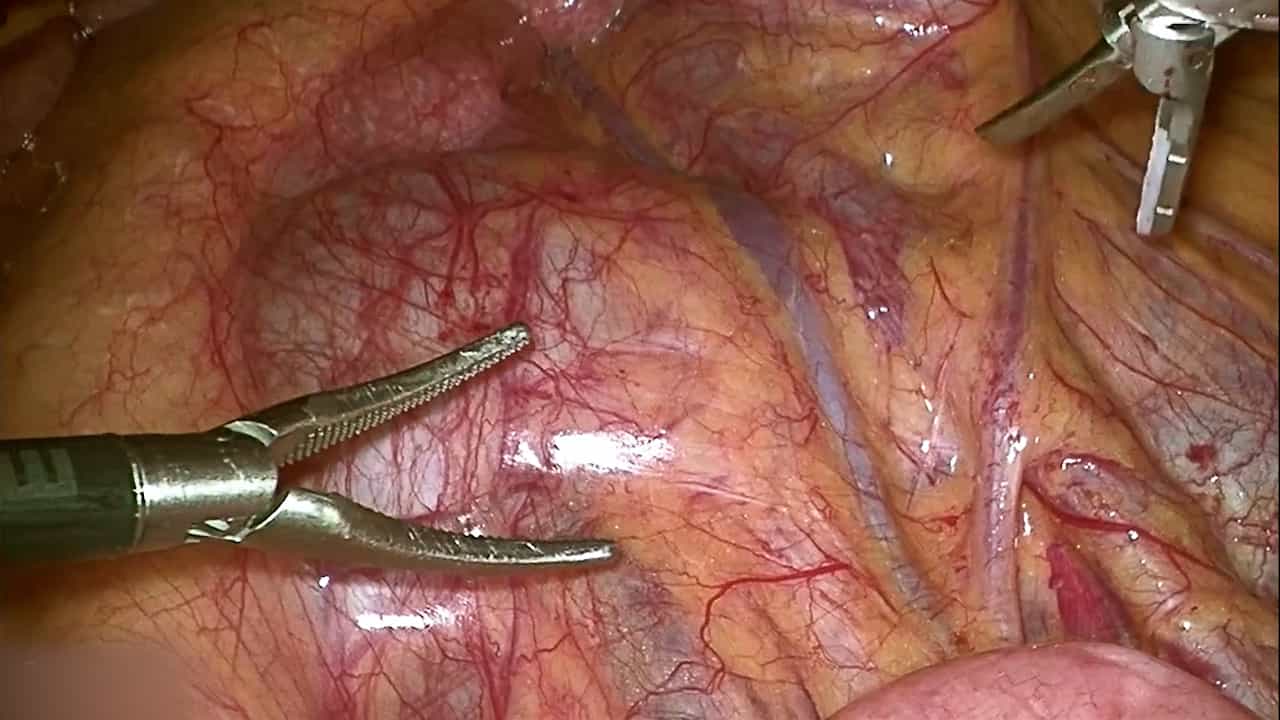
Transmesenteric Laparoscopic Pyeloplasty in Trendelenburg Position for Horseshoe Kidney with Hydronephrosis
Published on: July 8, 2025
1Department of Paediatric Surgery, University Hospital of Saint Etienne, Saint Etienne, France. manuel.lopez@chu-st-etienne.fr

Insights
Laparoscopic pyeloplasty (LP) is a safe and effective treatment for pediatric pelvi-ureteric junction (PUJ) obstruction, demonstrating excellent short-term outcomes. This minimally invasive approach is feasible even in infants, offering good results with minimal patient morbidity.
Area of Science:
- Pediatric Surgery
- Urology
- Minimally Invasive Surgery
Background:
- Pelvi-ureteric junction (PUJ) obstruction is a common congenital anomaly in children.
- Surgical correction is typically required to restore proper urine flow and preserve renal function.
- Laparoscopic pyeloplasty (LP) offers a minimally invasive alternative to open surgery.
Purpose of the Study:
- To evaluate the initial experience and outcomes of laparoscopic pyeloplasty (LP) in pediatric patients with PUJ obstruction.
- To assess the feasibility, safety, and efficacy of LP in this patient population.
- To describe the evolution of the technique and its results.
Main Methods:
- Retrospective review of 28 pediatric patients (infants and children) with unilateral PUJ obstruction who underwent LP.
- Standard laparoscopic technique involving PUJ resection and anastomosis with absorbable sutures.
- Use of laparoscopic or cystoscopic JJ stent insertion in most cases.
- Follow-up included clinical assessment, ultrasound, and isotope renography.
Main Results:
- LP was successfully completed in 93% (26/28) of patients.
- Mean operative time was 145 minutes, and mean hospital stay was 4 days.
- Postoperative complications included pyelonephritis (2 patients) and one case of PUJ leakage requiring intervention.
- All 26 patients who completed LP were asymptomatic, with improved hydronephrosis and drainage on imaging post-procedure.
- Aberrant crossing vessels were managed with sutures or ureteric transposition.
Conclusions:
- Laparoscopic pyeloplasty is an effective and safe procedure for pediatric PUJ obstruction with minimal morbidity.
- Excellent short-term results were observed, including improved renal function and reduced hydronephrosis.
- The technique is feasible in infants, and the transabdominal approach provides good surgical exposure.
- While LP is technically more demanding and has a longer operative time than open pyeloplasty, its benefits in terms of recovery and morbidity are significant.
Purpose:
To report our initial experience with laparoscopic pyeloplasty (LP) in children with pelvi-ureteric junction (PUJ) obstruction, and to describe the evolution and evaluate the results for these patients.
Materials And Methods:
Between May 2005 and April 2008, we retrospectively reviewed the records of 28 consecutive infants and children (20 males, eight females; mean age 63 months, range 2-180 months) with unilateral PUJ obstruction, some with deterioration of renal function on isotope renography. They all underwent LP (18 on the right, 10 on the left). The patient was placed in a (3/4) lateral position with three ports. The PUJ was resected and the anastomosis made using absorbable sutures. A JJ stent was inserted by laparoscopy in the majority of patients. Follow-up included clinical and ultrasound assessment, and isotope renography at 6 months.
Results:
LP was feasible in 26 of 28 patients (93%). The procedure could not be completed by laparoscopy in two patients, the main reason being difficulty in completing the anastomosis. Stent insertion was successful in 25 of the remaining 26 cases. In the one unsuccessful case, a perianastomotic drain was placed without complication in the postoperative period. An aberrant crossing vessel was found in four patients. In two we held up the aberrant crossing vessel and PUJ by 2-3 non-absorbable sutures without tension, and without the need for pyeloplasty. In the other two cases we performed an LP-enabled ureteric transposition. There were three postoperative complications: pyelonephritis in two patients and one patient required operative intervention for PUJ leakage, and underwent a nephrostomy with a further uneventful course. The mean operative time was 145 min (range 70-270 min), and mean hospital stay was 4 (1-8) days. In one patient the JJ time of removal by cystoscopy, and ureteroscopy was used to retrieve it. Mean follow-up was 18 months (range 4-64 months). The 26 patients who underwent LP were asymptomatic after removal of the double JJ stent, showing reduction of the degree of hydronephrosis in all patients, and had also improved PUJ drainage on isotope renography or sonography.
Conclusions:
LP is effective and safe in children with minimal morbidity and gives excellent short-term results. The feasibility is also excellent in patients younger than 1 year. The transabdominal approach revealed good exposition without disadvantage to the patient. However, the LP is more difficult and the operative time remains longer than open pyeloplasty.
Related Concept Videos
 01:22
Imaging Studies V: Intravenous Urography and Retrograde Pyelography
 01:25
Urinary Tract Calculi VI: Surgical Management