Related Experiment Video
Updated: Jun 27, 2026


Anesthesia and Intubation of Preadolescent Mouse Pups for Cardiothoracic Surgery
Published on: June 2, 2022
Pediatric procedural sedation with ketamine: time to discharge after intramuscular versus intravenous administration
Preeti Ramaswamy1, Franz E Babl, Conor Deasy
1Emergency Department, Royal Children's Hospital, Melbourne, Victoria, Australia.

Objectives:
Ketamine is an attractive agent for pediatric procedural sedation. There are limited data on time to discharge comparing intramuscular (IM) vs. intravenous (IV) ketamine. The authors set out to determine whether IM or IV ketamine leads to quicker discharge from the emergency department (ED) and how side effect profiles compare.
Methods:
All patients who had received ketamine IM or IV at a tertiary children's hospital ED during the 3-year study period (2004-2007) were identified. Prospective sedation registry data, retrospective medical records, and administrative data were reviewed for drug dosages, use of additional agents, time of drug administration to discharge, total ED time (triage to discharge), and adverse events. A subgroup analysis for patients requiring five or fewer sutures (short suture group) was performed.
Results:
A total of 229 patients were enrolled (60% male) with median age of 2.8 years (IQR =1.8-4.3 years) and median weight of 15.7 kg (range = 8.7-74 kg). Ketamine was most frequently employed for laceration repair (80%) and foreign body removal (9%). Overall, 48% received ketamine IM and 52% received it IV. In the short-suture subgroup, 52% received ketamine IM, while 48% received it IV. Multivariate linear regression analysis determined time from drug administration to patient discharge as 21 minutes shorter for IV compared with IM administration, adjusted for age and number of additional doses (R(2) = -0.35; 95% CI = -0.5 to -0.19; p < 0.001). Total time in the ED (triage to discharge) comparing IV versus IM administration, adjusting for age and gender and number of additional doses, was not significantly different (p = 0.16). In the short-suture subgroup, time to discharge from administration was also shorter in the IV ketamine group (R(2) = -0.454; 95%CI = -0.66 to -0.25; p < 0.001) but similar for total time in ED (p = 0.16). Overall, adverse events occurred in 35% (95% CI = 27% to 45%) of the IM group and 20% (95% CI = 13% to 28%) of the IV group (p = 0.01). Only one patient required brief bag-mask ventilation.
Conclusions:
In this institution, time from drug injection to discharge was shorter in the IV compared to IM ketamine group, both overall and for the short-suture group. However, time from triage to discharge was similar.
Related Concept Videos
 01:24
Parenteral Anesthetics: Overview
 00:59
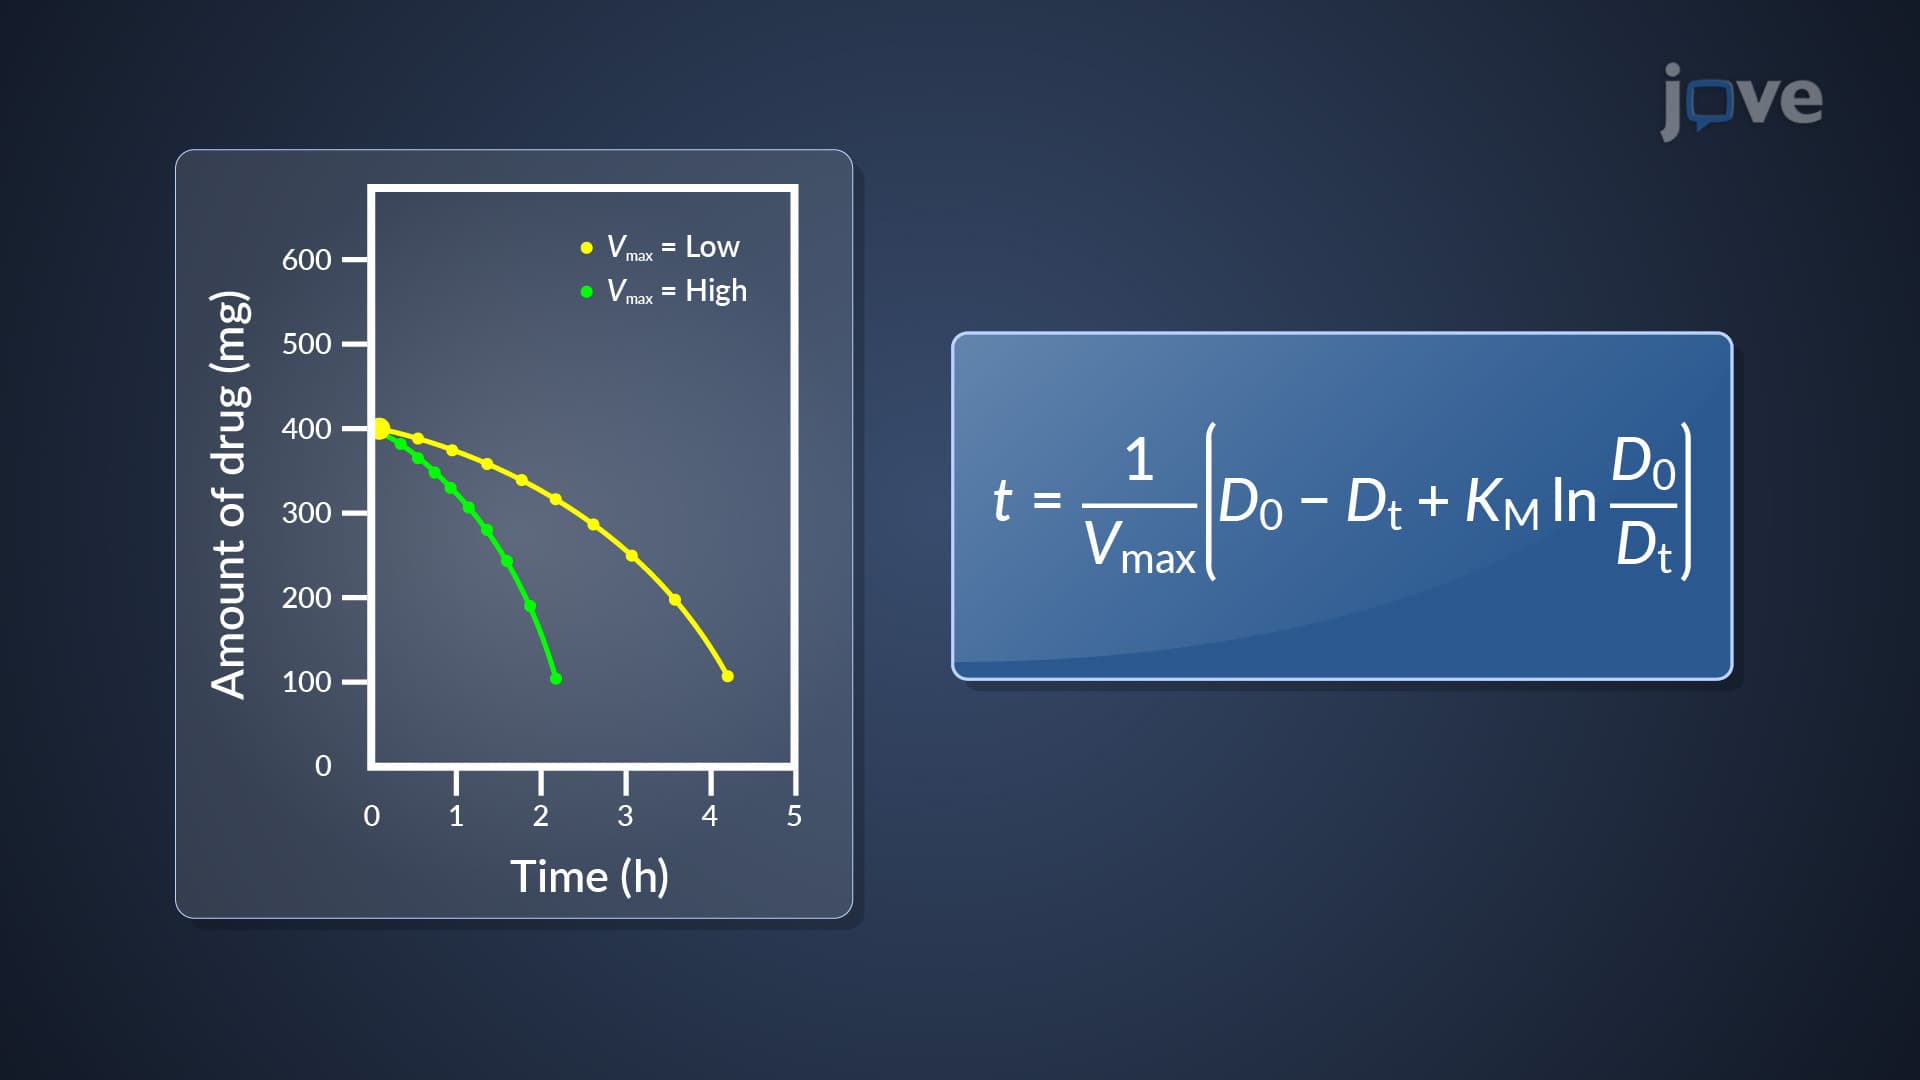
Nonlinear Pharmacokinetics: Drug Elimination for IV Bolus Injection
Following the administration of a single intravenous (IV) bolus injection, we can determine the concentration of the drug in the plasma at any given time. This calculation is achieved using a specific equation that integrates the values of Vmax and KM.
We can also...
 01:19
Depolarizing Blockers: Pharmocokinetics
 01:29
Drug Dosing: Infants and Children
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:18
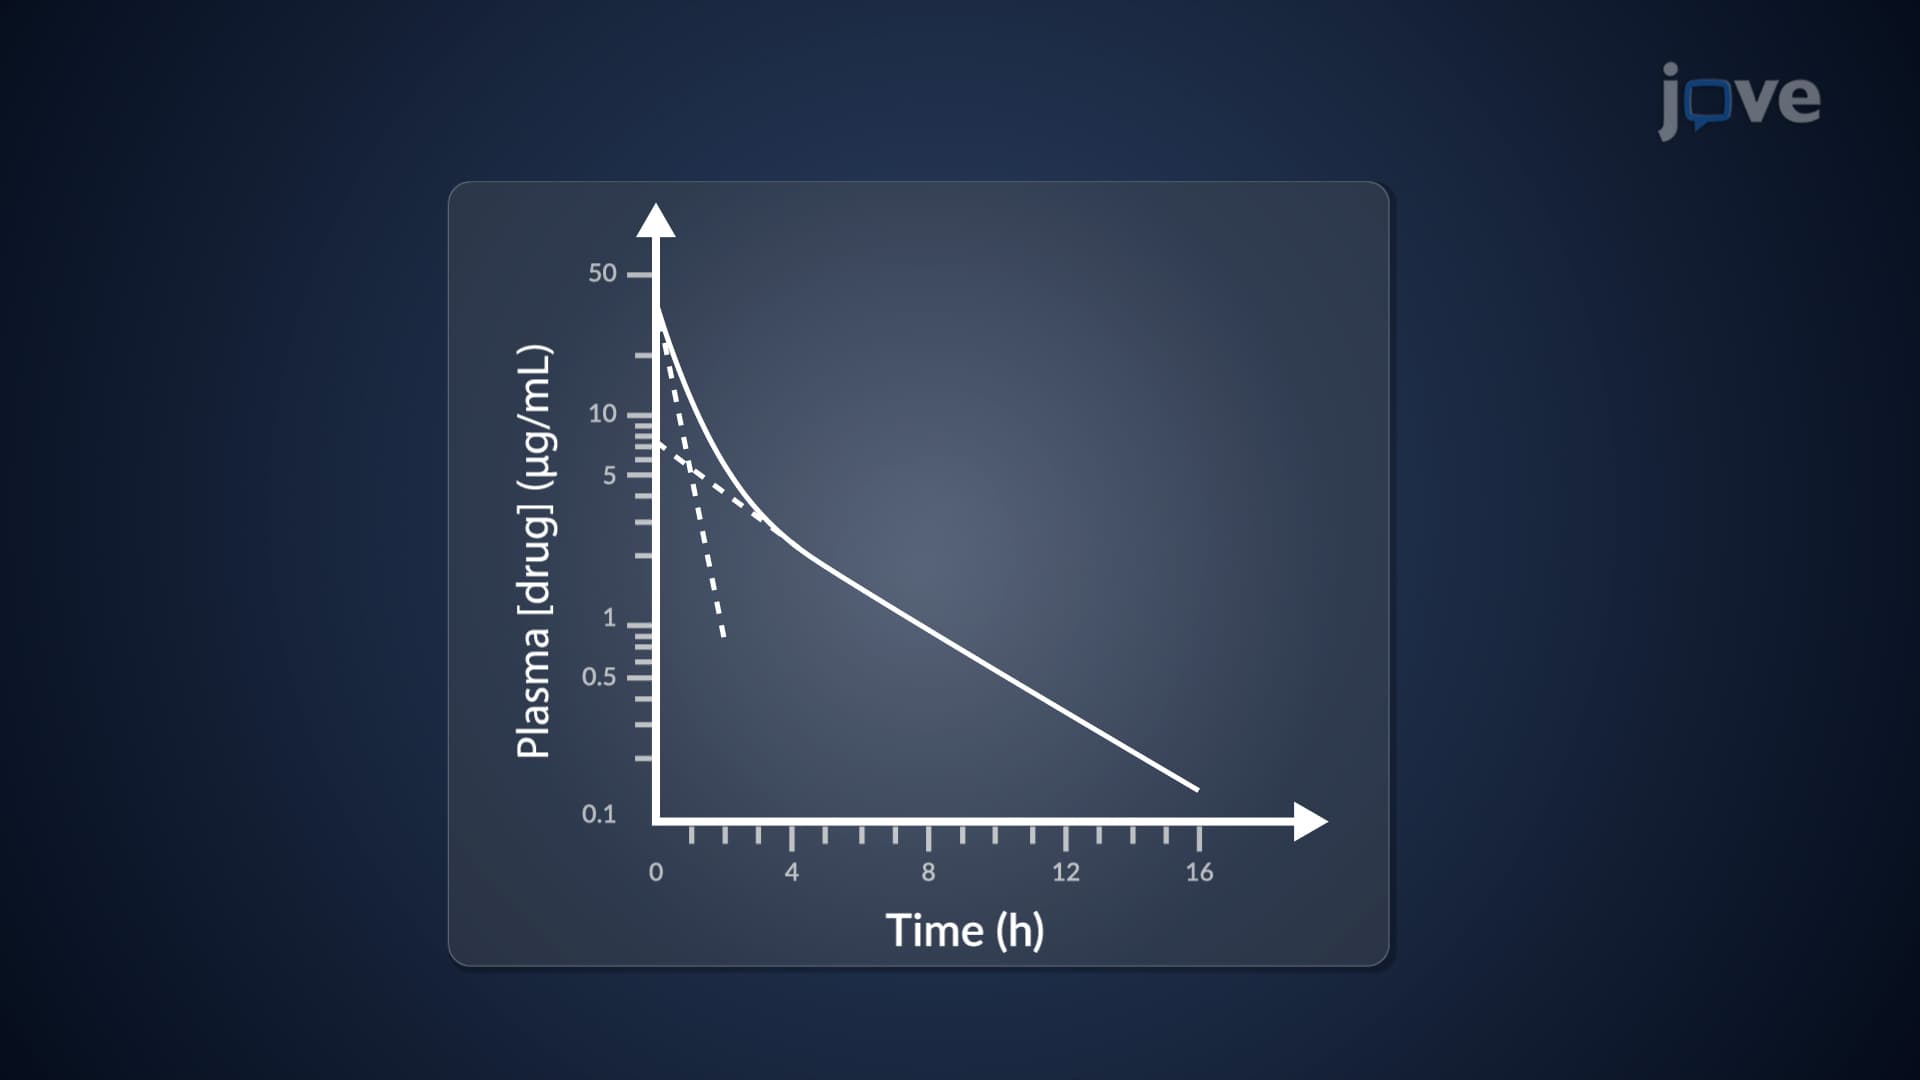
Two-Compartment Open Model: IV Bolus Administration
The disparity between drug input and the sum of drug transfer rates between...