Related Experiment Video
Updated: Jun 26, 2026
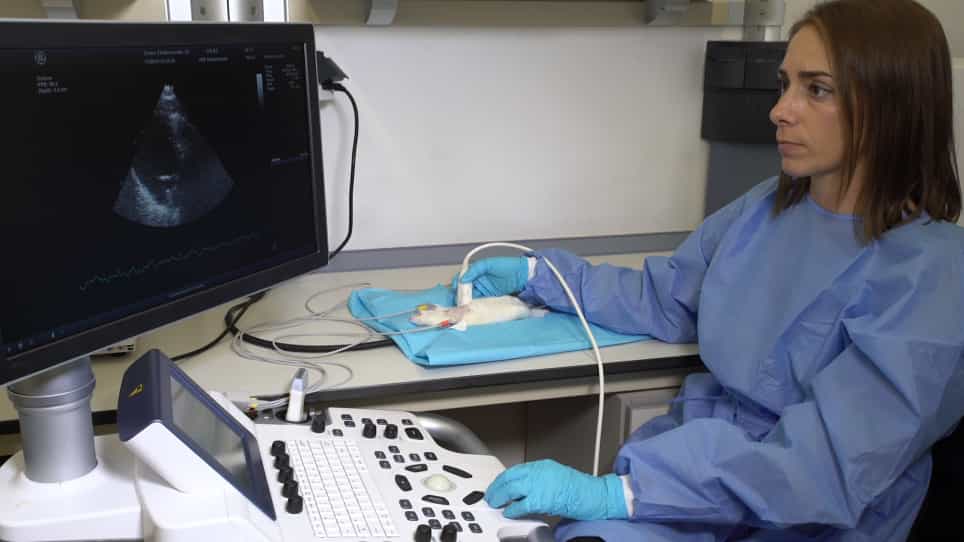
Echocardiographic Assessment of Cardiac Anatomy and Function in Adult Rats
Published on: December 13, 2019
A comparison of Tei index versus systolic to diastolic ratio to detect left ventricular dysfunction in pediatric
Dhaval R Patel1, Wei Cui, Katheryn Gambetta
1The Heart Institute for Children, Oak Lawn, IL, USA.

Insights
The left ventricular Tei index (TX) and systolic/diastolic duration ratio (S/D) both detect ventricular dysfunction, with TX showing slightly higher accuracy. Combining TX and S/D improves detection rates for left ventricular dysfunction.
Area of Science:
- Cardiology
- Echocardiography
- Pediatric cardiology
Background:
- Left ventricular (LV) dysfunction assessment is crucial in pediatric cardiology.
- The Tei index (TX) and systolic/diastolic duration ratio (S/D) are novel echocardiographic parameters for evaluating LV function.
- Accurate diagnostic tools are needed to identify systolic and diastolic dysfunction.
Purpose of the Study:
- To evaluate the diagnostic performance of the left ventricular (LV) Tei index (TX) and the systolic/diastolic duration ratio (S/D).
- To compare the accuracy, sensitivity, specificity, predictive values, and likelihood ratios of TX and S/D in detecting ventricular dysfunction in children.
- To assess the combined utility of TX and S/D for improved detection of LV dysfunction.
Main Methods:
- A cohort of 68 children (25 normal, 43 abnormal) underwent echocardiographic assessment of LV systolic and diastolic function.
- Systolic dysfunction criteria included ejection fraction < 50%, fractional shortening < 27%, and S wave < Z-1.5.
- Diastolic dysfunction criteria included prolonged isovolumic relaxation time, E/E' ratio > 13, and E' < Z-1.5.
- TX > 0.5 and S/D > 1.0 were defined as abnormal. Diagnostic performance was analyzed using 2x2 tables and ROC curves.
Main Results:
- The overall accuracy for TX was 85% and for S/D was 82%.
- TX demonstrated highest accuracy (92%) in detecting diastolic and combined LV dysfunction.
- TX generally outperformed S/D in sensitivity, specificity, and predictive values across most categories.
Conclusions:
- The left ventricular Tei index (TX) offers slightly superior diagnostic performance compared to the S/D ratio for detecting LV dysfunction in children.
- Neither TX nor S/D alone detected dysfunction in 15-18% of cases, highlighting potential limitations.
- Combining TX and S/D significantly enhances the detection of left ventricular dysfunction, minimizing missed diagnoses.
Background:
The aim of this study was to determine the accuracy, sensitivity, specificity, predictive values, and likelihood ratios of the left ventricular (LV) Tei index (TX) and the ratio of systolic duration to diastolic duration (S/D) to detect ventricular dysfunction.
Methods:
LV systolic and diastolic function were studied in a cohort of 68 children, 25 normal and 43 abnormal. Systolic dysfunction was defined as the presence of all of 3 criteria: ejection fraction < 50%, fractional shortening < 27%, and tissue Doppler systolic S wave < 1.5 standard deviations below normal (Z-1.5). Diastolic dysfunction was defined as the presence of all of 3 criteria: isovolumic relaxation time corrected for heart rate > 88 ms, ratio of transmitral Doppler flow early diastolic velocity (E) to mitral valve annular early diastolic tissue Doppler velocity (E') > 13, and E' < Z-1.5. The cohort was divided into 4 groups: normal systolic and diastolic function, systolic dysfunction, diastolic dysfunction, and combined systolic and diastolic dysfunction. TX > 0.5 and S/D > 1.0 were defined as abnormal. TX and S/D results were compared with normal function versus abnormal function categories using 2 x 2 classification tables and receiver operating characteristic curves.
Results:
The overall accuracy of TX was 85%, and that of S/D was 82%. TX was most accurate (92%) for detecting diastolic and combined dysfunction, whereas S/D had similar accuracy for all LV function groups. The overall accuracy, sensitivity, specificity, positive predictive value, negative predictive value, positive likelihood ratio, and negative likelihood ratio of TX were slightly greater than those for S/D for almost all categories.
Conclusion:
The overall accuracy, sensitivity, specificity, predictive values, and likelihood ratios of TX are slightly greater than those of S/D for most categories of dysfunction, although either may fail to detect dysfunction in 15% to 18% of cases. When both TX and S/D are used in combination, using the presence of either TX > 0.5 or S/D > 1.0 as indicative of dysfunction, few cases of LV dysfunction should elude detection.