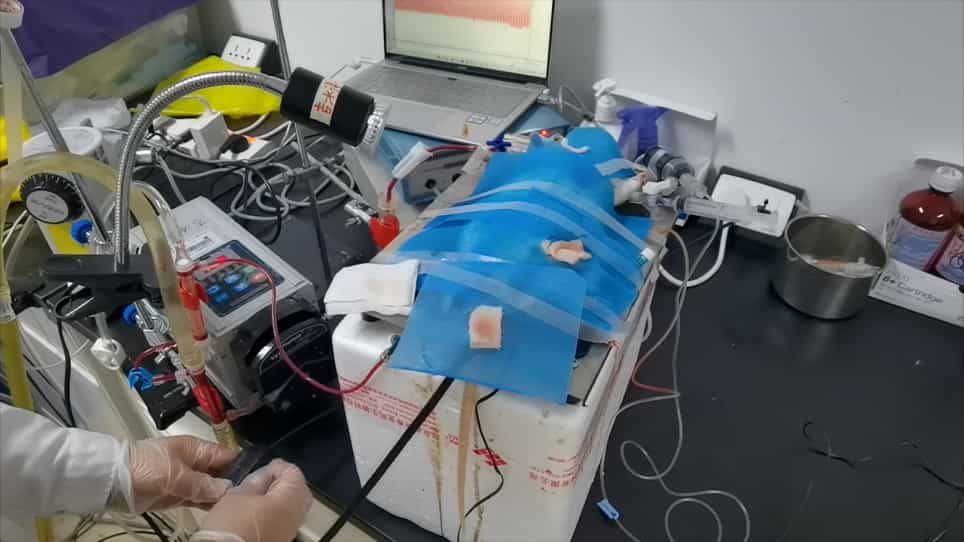
Related Experiment Video
Updated: Jun 26, 2026

A Recovery Cardiopulmonary Bypass Model Without Transfusion or Inotropic Agents in Rats
Published on: March 23, 2018
Consensus statement: Defining minimal criteria for reporting the systemic inflammatory response to cardiopulmonary
R Clive Landis1, Joseph E Arrowsmith, Robert A Baker
1Edmund Cohen Laboratory for Vascular Research, Chronic Disease Research Centre, University of the West Indies, Barbados, West Indies. clandis@uwichill.edu.bb

Insights
Systemic inflammatory response during cardiopulmonary bypass (CPB) is poorly understood due to inconsistent research. This consensus document recommends standardized reporting of CPB criteria, inflammatory markers, and organ injury endpoints to advance clinical practice.
Area of Science:
- Cardiovascular Surgery
- Immunology
- Critical Care Medicine
Background:
- The systemic inflammatory response (SIR) to cardiopulmonary bypass (CPB) involves multiple biological cascades, including complement, coagulation, and neutrophil activation.
- Despite understanding causal factors since the 1990s, clinical interventions to mitigate SIR have yielded disappointing results.
- Cardiac surgery lacks standardized reporting criteria for SIR, hindering research and the identification of therapeutic targets.
Purpose of the Study:
- To establish a consensus framework for standardizing research on the systemic inflammatory response to cardiopulmonary bypass.
- To guide future studies and clinical interventions aimed at understanding and managing SIR during cardiac surgery.
Main Methods:
- An evidence-based review of existing literature on SIR in CPB was conducted.
- A panel of experts convened at the Outcomes XII meeting in 2008 to draft consensus recommendations.
- The consensus focuses on defining minimal reporting criteria for CPB, inflammatory markers, and clinical endpoints.
Main Results:
- A significant gap exists in current research, with most studies failing to measure key causal factors of SIR.
- The consensus document proposes a framework for standardized reporting to improve research consistency and comparability.
- Recommendations include mandatory reporting of CPB criteria, a minimal set of inflammatory markers, and relevant clinical endpoints of organ injury.
Conclusions:
- Standardizing the reporting of research findings is crucial for advancing the understanding of SIR in CPB.
- Implementing the proposed framework will facilitate the identification of mechanisms, drug targets, and effective clinical strategies.
- This consensus aims to improve patient outcomes by providing a foundation for more robust and reproducible research in cardiac surgery.
Abstract:
The causal factors of the systemic inflammatory response to cardiopulmonary bypass (CPB) were correctly identified in the early 1990 s: "... activation of complement, coagulation, fibrinolytic, and kallikrein cascades, activation of neutrophils with degranulation and protease enzyme release, oxygen radical production, and the synthesis of various cytokines from mononuclear cells" [Butler 1993]. Why therefore have clinical advances to curb the systemic inflammatory response proven such a disappointment? Part of the problem is that cardiac surgery has never taken intellectual ownership of this issue, borrowing its diagnosis from critical care medicine and failing to define the minimal criteria that should be measured when reporting on the systemic inflammatory response. An evidence based review of the current literature by many of the coauthors on this paper found that the majority of studies on the systemic inflammatory response did not measure a single one of the causal factors listed above - thus hindering our ability to identify mechanisms of causation and identify drug targets [Landis 2008]. A panel of experts convened at the Outcomes XII meeting, Barbados 2008, drafted the present consensus document in order to provide a framework to guide future studies and interdictions of the systemic inflammatory response. Herein, we have recommended: 1) mandatory reporting of minimal CPB and perfusion criteria that may affect outcomes, 2) reporting of a minimal set of causal inflammatory markers linked to adverse sequelae, and 3) reporting of at least one clinical end-point of organ injury, from a list of endpoints and markers of organ injury that balance practicality with clinical meaningfulness. It is our collective belief that this document will serve as a foundation for furthering our understanding of the influence of CPB practice with the systemic inflammatory response by standardizing the reporting of research findings in the peer-reviewed literature.