Related Experiment Video
Updated: Jun 26, 2026
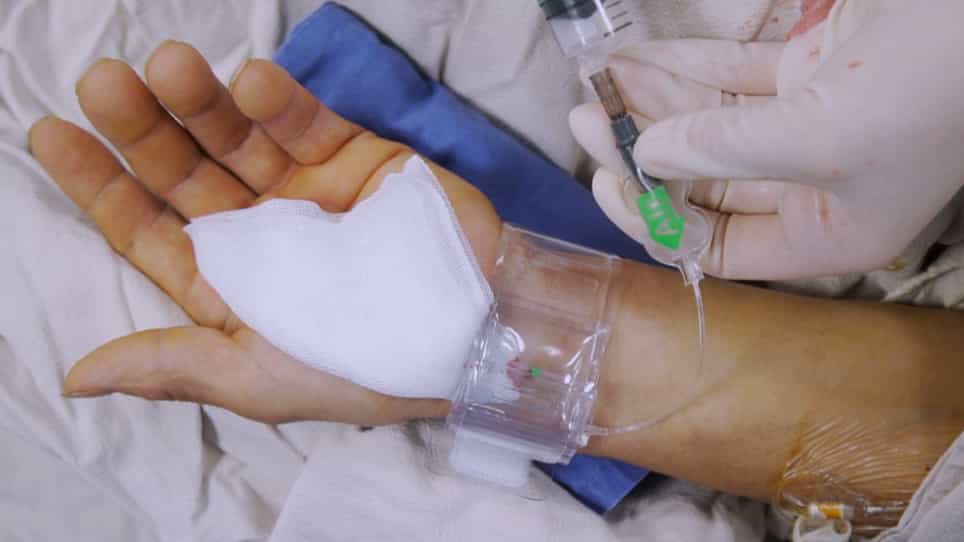
Transradial Access Chemoembolization for Hepatocellular Carcinoma Patients
Published on: September 20, 2020
Management of haemophilic pseudotumours with special emphasis on radiotherapy and arterial embolization
R Espandar1, P Heidari, E C Rodriguez-Merchan
1Department of Orthopedics Surgery, Imam University Hospital, Tehran University of Medical Sciences, Tehran, Iran. espandar@gmail.com

The haemophilic pseudotumour is an expanding destructive haematoma, which is associated with a considerable amount of morbidity in haemophilic patients. Its prevention is paramount. In fact, this goal can be achieved by primary prophylaxis to avoid muscle haematomas and by adequate and long-term haematological treatment of muscle haematomas in case they appear. At the moment, surgical excision of pseudotumour is the preferred treatment by many authors. However, there are instances that surgical extraction of the lesion is not feasible. In such situations, radiotherapy and arterial embolization should be considered either alone or as an adjunct to surgery. Conservative management using a combination of radiotherapy and replacement therapy should be considered for treating haemophilic bone pseudotumours, which are located in the skull or in the distal parts of the limbs, especially in conditions where some impediments to surgical excision exist. In fact, the radiation should be delivered to the lesion site in small fragments of 2 Gy or less to a total dosage of 6-23.5 Gy, which is the most recommended radiation dosage, at the moment. Therapeutic arterial embolization of haemophilic pseudotumours should be considered in lesions of large size, especially in pseudotumours of pelvic region, as it may effectively reduce its size and decrease the risk of bleeding complications during surgery. Nevertheless, in view of its temporary effect, embolization may better be performed, as a preparatory procedure, at best about 2 weeks prior to surgery. This time lapse will allow for mass shrinkage but is insufficient for vessel restoration.
The haemophilic pseudotumour is an expanding destructive haematoma, which is associated with a considerable amount of morbidity in haemophilic patients. Its prevention is paramount. In fact, this goal can be achieved by primary prophylaxis to avoid muscle haematomas and by adequate and long-term haematological treatment of muscle haematomas in case they appear. At the moment, surgical excision of pseudotumour is the preferred treatment by many authors. However, there are instances that surgical extraction of the lesion is not feasible. In such situations, radiotherapy and arterial embolization should be considered either alone or as an adjunct to surgery. Conservative management using a combination of radiotherapy and replacement therapy should be considered for treating haemophilic bone pseudotumours, which are located in the skull or in the distal parts of the limbs, especially in conditions where some impediments to surgical excision exist. In fact, the radiation should be delivered to the lesion site in small fragments of 2 Gy or less to a total dosage of 6-23.5 Gy, which is the most recommended radiation dosage, at the moment. Therapeutic arterial embolization of haemophilic pseudotumours should be considered in lesions of large size, especially in pseudotumours of pelvic region, as it may effectively reduce its size and decrease the risk of bleeding complications during surgery. Nevertheless, in view of its temporary effect, embolization may better be performed, as a preparatory procedure, at best about 2 weeks prior to surgery. This time lapse will allow for mass shrinkage but is insufficient for vessel restoration.

Related Concept Videos
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:29
Venous Thrombosis III: Interprofessional Care