Related Experiment Video
Updated: Jun 24, 2026

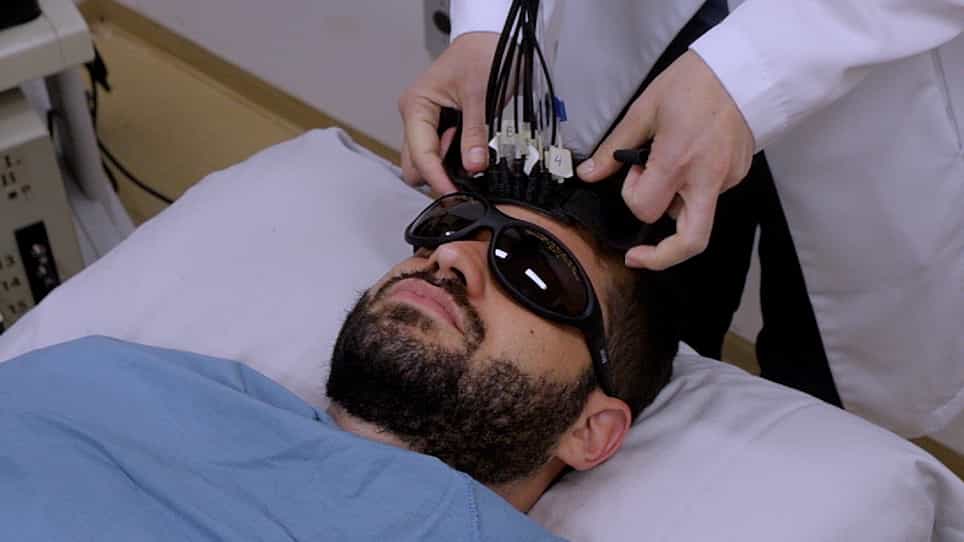
How to Administer Near-Infrared Spectroscopy in Critically ill Neonates, Infants, and Children
Published on: August 19, 2020
Near-infrared spectroscopy as a guide for an intermittent cerebral perfusion strategy during neonatal circulatory
Christopher E Mascio1, John A Myers, Harvey L Edmonds
1Division of Thoracic and Cardiovascular Surgery, Department of Bioinformatics and Biostatistics, University of Louisville, Louisville, Kentucky 40202, USA. cmascio@ucsamd.com

Abstract:
In view of the existing controversy concerning the best perfusion technique during deep hypothermic circulatory arrest (DHCA) for neonatal heart operations, we examined intraoperative rSO2 to help define an optimal interval for an intermittent antegrade cerebral perfusion (IACP) strategy. Records of patients undergoing stage 1 palliation (S1P) and repair of total anomalous pulmonary venous return (rTAPVR) from 1996 to 2004 were reviewed. A total of 16 patients were identified (11 S1P, 5 rTAPVR) with complete data and long periods of DHCA. A decline in rSO2 of either 20% or below a value of 50 was considered significant. The rSO2 for all patients was evaluated after 5, 10, 15, and 20 minutes of DHCA for significant cerebral desaturation. The average rSO2 at the start of DHCA ranged from 45 to 89 for S1P and 35-86 for rTAPVR. Significant cerebral desaturation was observed in 25%-31% of patients after 5 minutes; 42%-44% of patients after 10 minutes; 58%-69% after 15 minutes; and 75%-83% after 20 minutes. Each neonate has a unique baseline cerebral saturation. Also, the response to DHCA varies among subjects as the rate of decrease of rSO2 was not uniform. Universally applying the same interval after which to perfuse the brain permits significant cerebral desaturation in a large percentage of patients. Cerebral oximetry may provide a guide for developing an individualized cerebral perfusion strategy.